Related Experiment Video
Updated: Jul 12, 2026
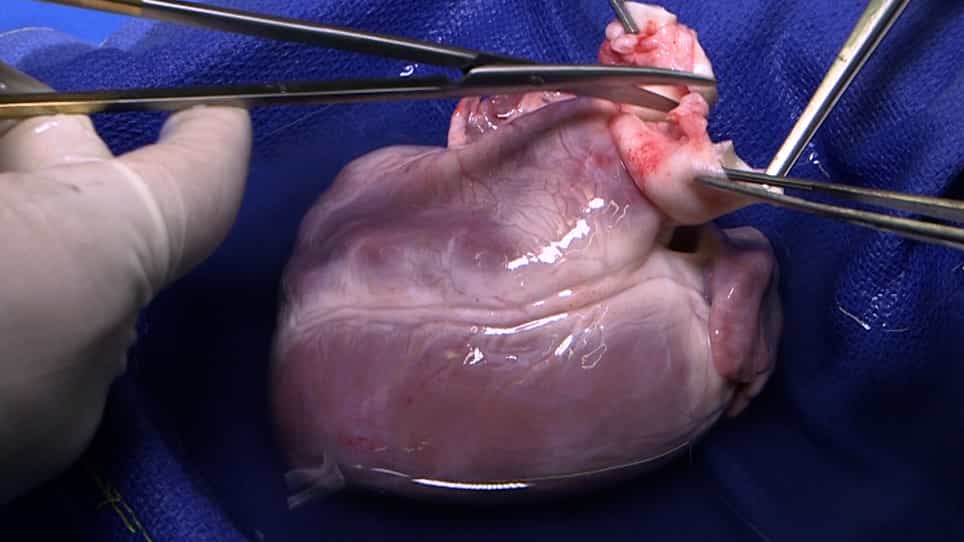
Functional Assessment of the Donor Heart During Ex Situ Perfusion: Insights from Pressure-Volume Loops and Surface Echocardiography
Published on: October 11, 2022
Testing for BNP and NT-proBNP in the diagnosis and prognosis of heart failure

Insights
This systematic review found that B-type natriuretic peptide (BNP) and N-terminal pro-BNP (NT-proBNP) are good for ruling out heart failure (HF) and predicting mortality. However, their value in screening and monitoring HF treatment requires further investigation.
Area of Science:
- Cardiology
- Biomarkers
- Systematic Review & Meta-Analysis
Background:
- Heart failure (HF) diagnosis and prognosis rely on various clinical and biochemical markers.
- B-type natriuretic peptide (BNP) and N-terminal pro-BNP (NT-proBNP) are cardiac biomarkers with potential roles in HF management.
Purpose of the Study:
- To systematically evaluate BNP and NT-proBNP for determinants, diagnostic performance in HF, and predictive ability for mortality and cardiac endpoints.
- To assess the value of BNP and NT-proBNP in monitoring HF treatment.
Main Methods:
- A systematic review and meta-analysis of primary studies published from 1989 to February 2005.
- Searched multiple databases including MEDLINE, EMBASE, CINAHL, Cochrane Central, and AMED.
- Included all study designs, focusing on English-only studies and maximizing generalizability of test methods.
Main Results:
- Identified 103 determinants; age, female gender, and creatinine levels were positively associated with BNP and NT-proBNP.
- Pooled sensitivity and specificity for BNP were 94% and 66%, and for NT-proBNP were 92% and 65%, showing good diagnostic properties as a rule-out test for HF.
- BNP and NT-proBNP demonstrated independent diagnostic information beyond traditional measures for HF.
Conclusions:
- BNP and NT-proBNP are consistent, independent predictors of mortality and cardiac endpoints in patients at risk for or diagnosed with coronary artery disease (CAD) and HF.
- Evidence suggests poor performance for screening HF, with AUC values indicating limited utility.
- Insufficient evidence exists to confirm the value of BNP and NT-proBNP for monitoring HF treatment response in stable chronic HF patients.
Objectives:
The purpose of this systematic review was to evaluate BNP and NT-proBNP to: (a) identify determinants, (b) establish their diagnostic performance in heart failure (HF) patients, (c) determine their predictive ability with respect to mortality and other cardiac endpoints, and (d) determine their value in monitoring HF treatment.
Data Sources:
MEDLINE, EMBASE, CINAHL, Cochrane Central, and AMED from 1989 to February 2005 were searched for primary studies.
Review Methods:
Standard systematic review methodology, including meta-analysis, was employed. All study designs were included. Eligibility criteria included English-only studies and restricted the number of test methods to maximize generalizability. Outcomes for prognosis were limited to mortality and specific cardiac events. Further specific criteria were developed for each research question.
Results:
Determinants: There were 103 determinants identified including age, gender, disease, treatment, as well as biochemical and physiological measures. Few studies reported independent associations and of those that did age, female gender and creatinine levels were positively associated with BNP and NT-proBNP.
Diagnosis:
Pooled sensitivity and specificity values were 94 and 66 percent for BNP and 92 and 65 percent for NT-proBNP; there was minimal difference among settings (emergency, specialized clinics, and primary care). B-type natriuretic peptides also added independent diagnostic information above traditional measures for HF.
Prognosis:
Both BNP and NT-proBNP were found to be independent predictors of mortality and other cardiac composite endpoints in patients with risk of coronary artery disease (CAD) (risk estimate range = 1.10 to 5.40), diagnosed CAD (risk estimate range = 1.50 to 3.00), and diagnosed HF patients (risk estimate range = 2.11 to 9.35). With respect to screening, the AUC values (range = 0.57 to 0.88) suggested poor performance. Monitoring Treatment: Studies showed therapy reduced BNP and NT-proBNP, however, relationship to outcome was limited and not consistent.
Conclusions:
Determinants: The importance of the identified determinants for clinical use is not clear.
Diagnosis:
In all settings both BNP and NT-proBNP show good diagnostic properties as a rule out test for HF.
Prognosis:
BNP and NT-proBNP are consistent independent predictors of mortality and other cardiac composite endpoints for populations with risk of CAD, diagnosed CAD, and diagnosed HF. There is insufficient evidence to determine the value of B-type natriuretic peptides for screening of HF. Monitoring Treatment: There is insufficient evidence to demonstrate that BNP and NT-proBNP levels show change in response to therapies to manage stable chronic HF patients.
Related Concept Videos
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:30
Heart Failure VII: Nursing Interventions
 01:29
Heart Failure II: Pathophysiology
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...