Related Experiment Video
Updated: Jul 11, 2026


Three-Dimensional Cell Culture Models to Investigate the Epithelial Barrier in Eosinophilic Esophagitis
Published on: May 10, 2024
Hypereosinophilic syndromes
Florence E Roufosse1, Michel Goldman, Elie Cogan
1Institute for Medical Immunology, Université Libre de Bruxelles, Gosselies, Belgium. froufoss@ulb.ac.be

Abstract:
Hypereosinophilic syndromes (HES) constitute a rare and heterogeneous group of disorders, defined as persistent and marked blood eosinophilia (> 1.5 x 10(9)/L for more than six consecutive months) associated with evidence of eosinophil-induced organ damage, where other causes of hypereosinophilia such as allergic, parasitic, and malignant disorders have been excluded. Prevalence is unknown. HES occur most frequently in young to middle-aged patients, but may concern any age group. Male predominance (4-9:1 ratio) has been reported in historic series but this is likely to reflect the quasi-exclusive male distribution of a sporadic hematopoietic stem cell mutation found in a recently characterized disease variant. Target-organ damage mediated by eosinophils is highly variable among patients, with involvement of skin, heart, lungs, and central and peripheral nervous systems in more than 50% of cases. Other frequently observed complications include hepato- and/or splenomegaly, eosinophilic gastroenteritis, and coagulation disorders. Recent advances in underlying pathogenesis have established that hypereosinophilia may be due either to primitive involvement of myeloid cells, essentially due to occurrence of an interstitial chromosomal deletion on 4q12 leading to creation of the FIP1L1-PDGFRA fusion gene (F/P+ variant), or to increased interleukin (IL)-5 production by a clonally expanded T cell population (lymphocytic variant), most frequently characterized by a CD3-CD4+ phenotype. Diagnosis of HES relies on observation of persistent and marked hypereosinophilia responsible for target-organ damage, and exclusion of underlying causes of hypereosinophilia, including allergic and parasitic disorders, solid and hematological malignancies, Churg-Strauss disease, and HTLV infection. Once these criteria are fulfilled, further testing for eventual pathogenic classification is warranted using appropriate cytogenetic and functional approaches. Therapeutic management should be adjusted to disease severity and eventual detection of pathogenic variants. For F/P+ patients, imatinib has undisputedly become first line therapy. For others, corticosteroids are generally administered initially, followed by agents such as hydroxycarbamide, interferon-alpha, and imatinib, for corticosteroid-resistant cases, as well as for corticosteroid-sparing purposes. Recent data suggest that mepolizumab, an anti-IL-5 antibody, is an effective corticosteroid-sparing agent for F/P-negative patients. Prognosis has improved significantly since definition of HES, and currently depends on development of irreversible heart failure, as well as eventual malignant transformation of myeloid or lymphoid cells.


Related Concept Videos
 01:30
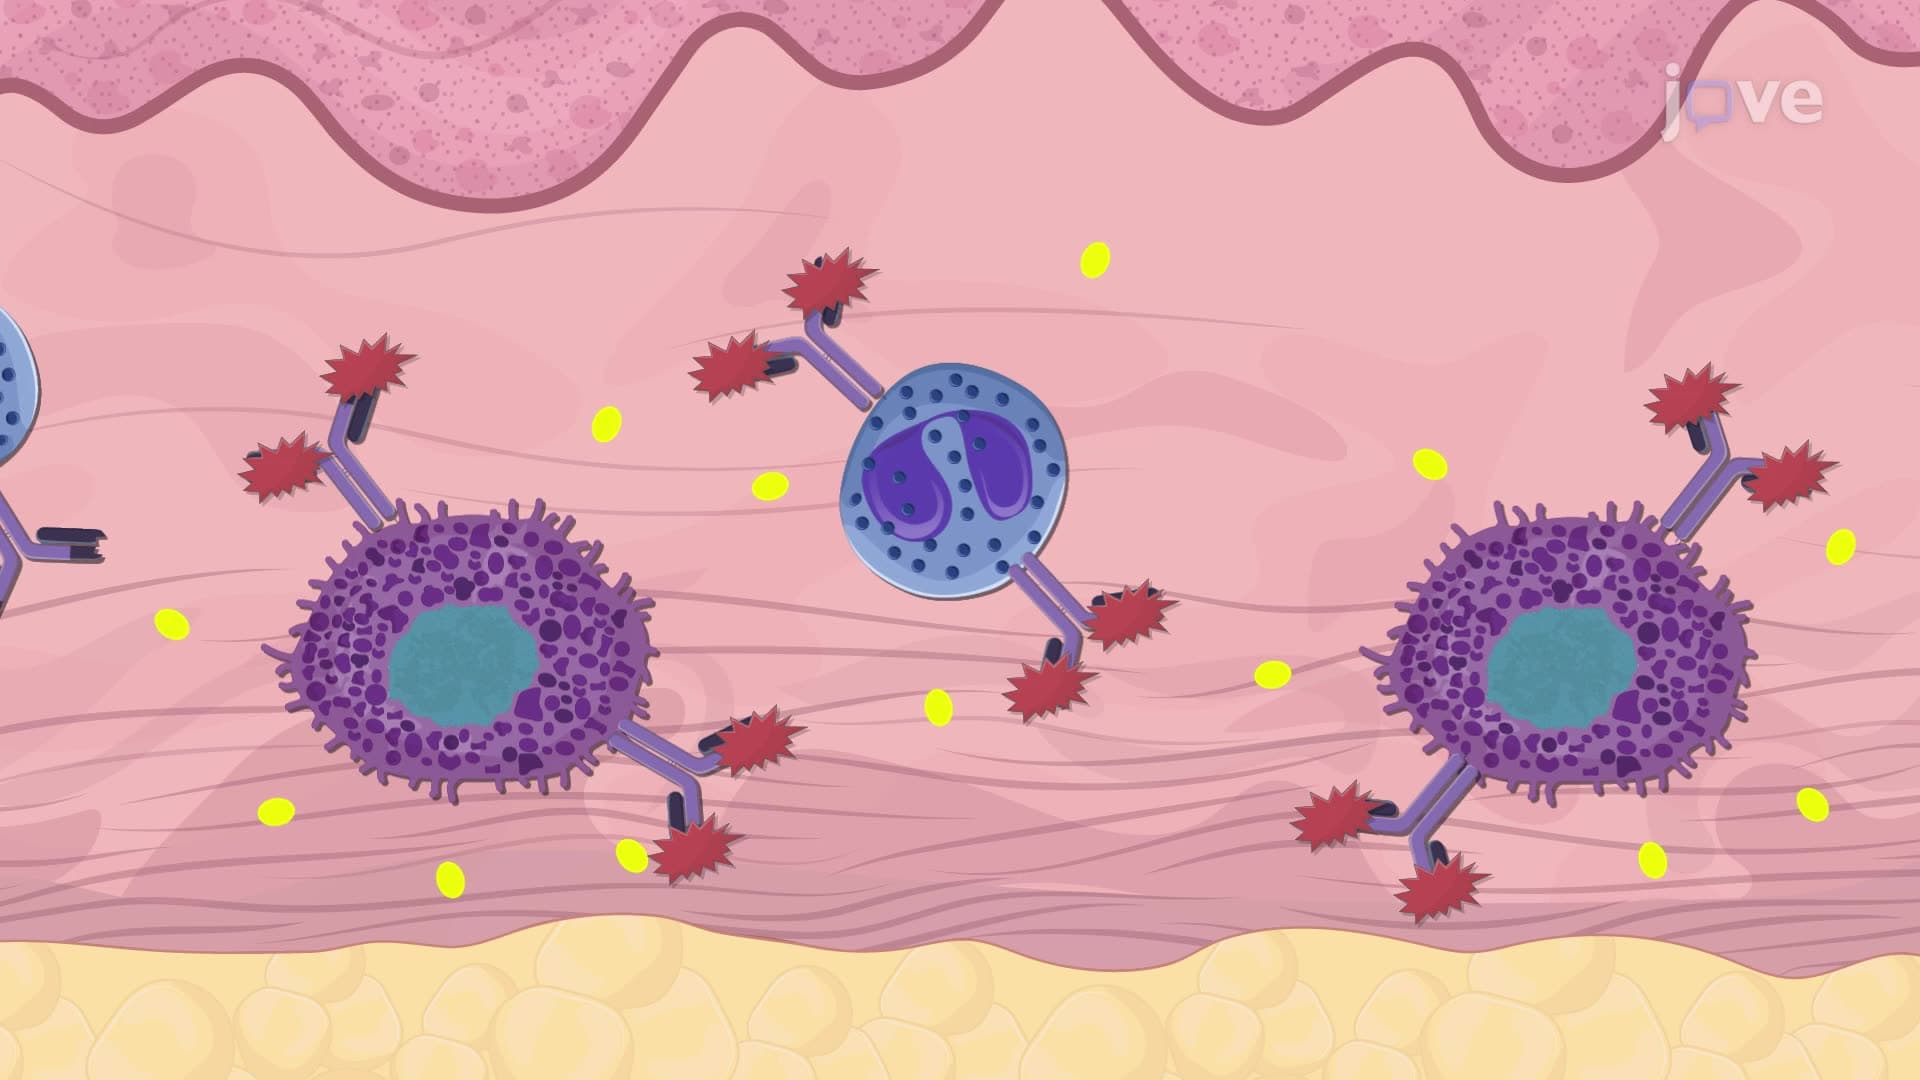
Hypersensitivities
Types of Hypersensitivities
Hypersensitivity reactions are categorized into four types: Type 1, Type 2, Type 3, and Type 4. Each type has a distinct mechanism...
 01:24
Nephrotic Syndrome I : Introduction
 01:22
Lysosomal Hydrolases
 01:30
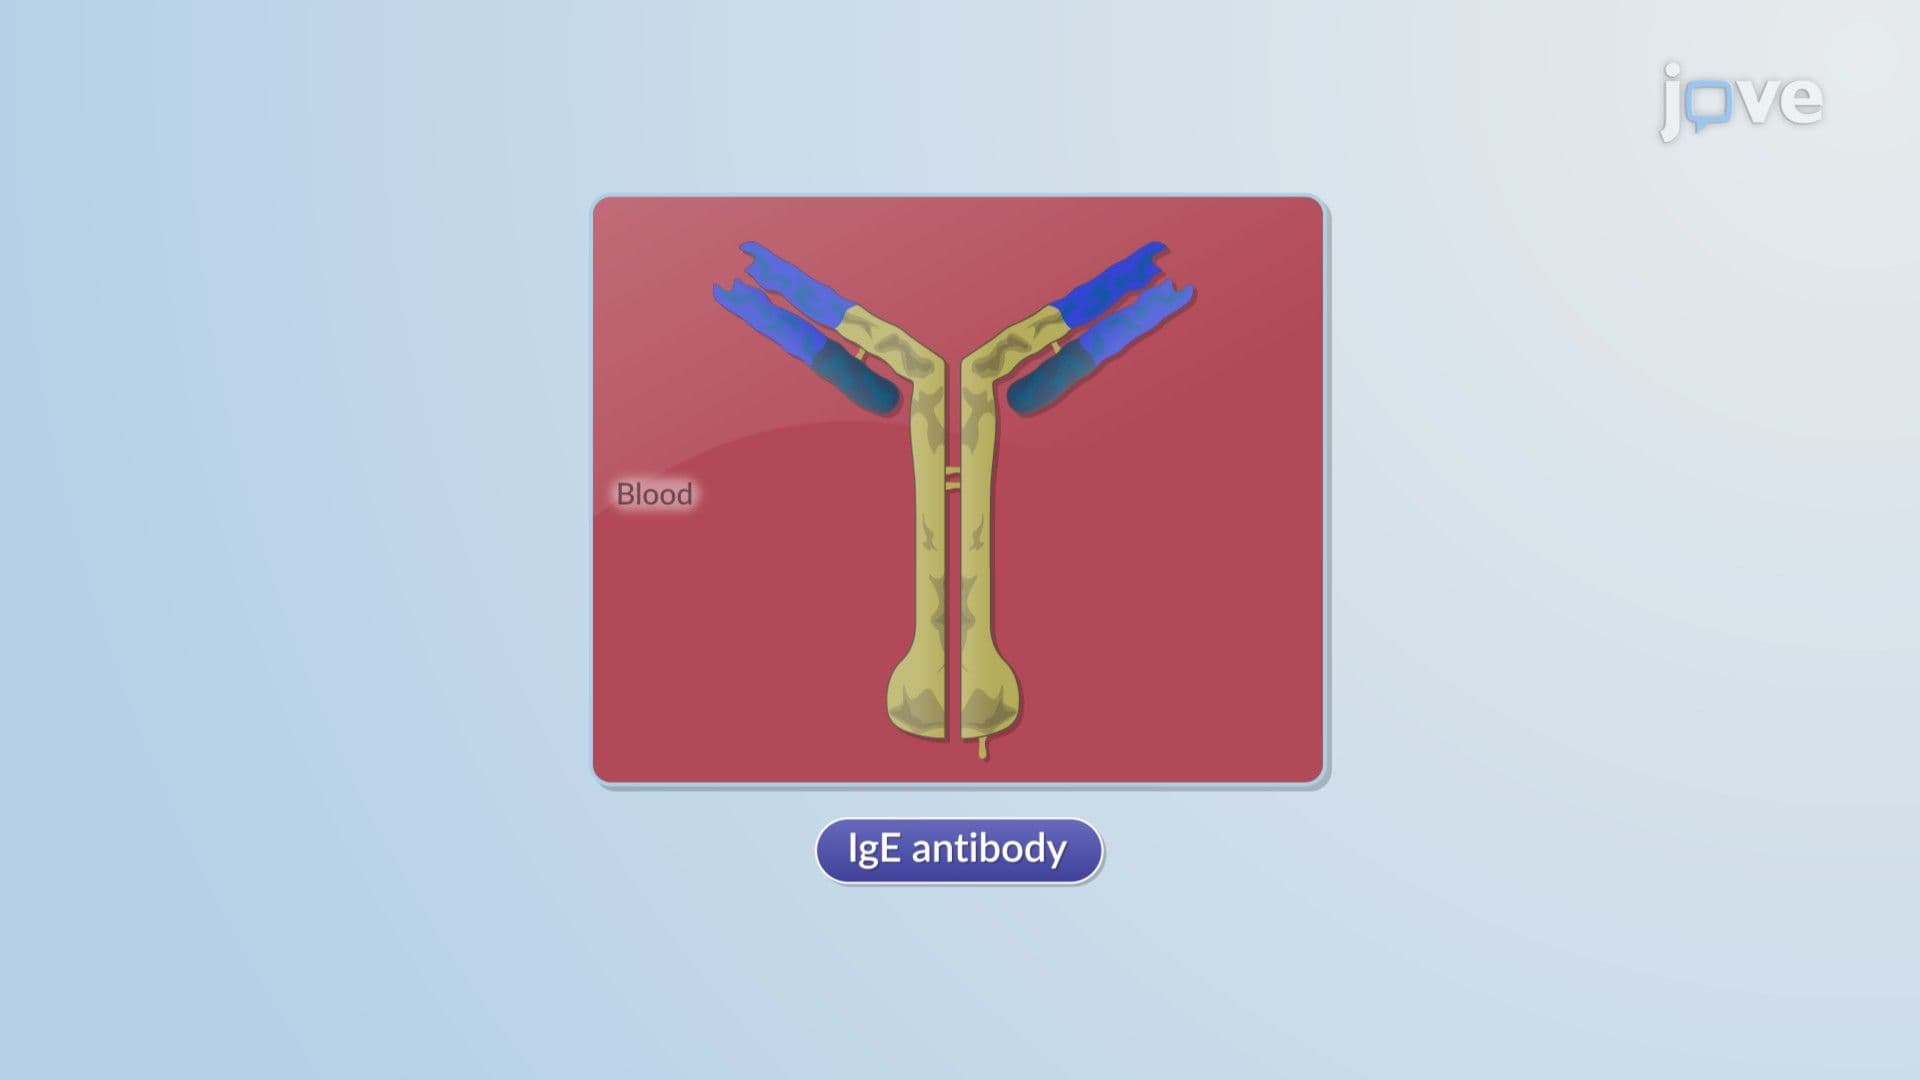
Allergic Reactions: Anaphylaxis
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:30
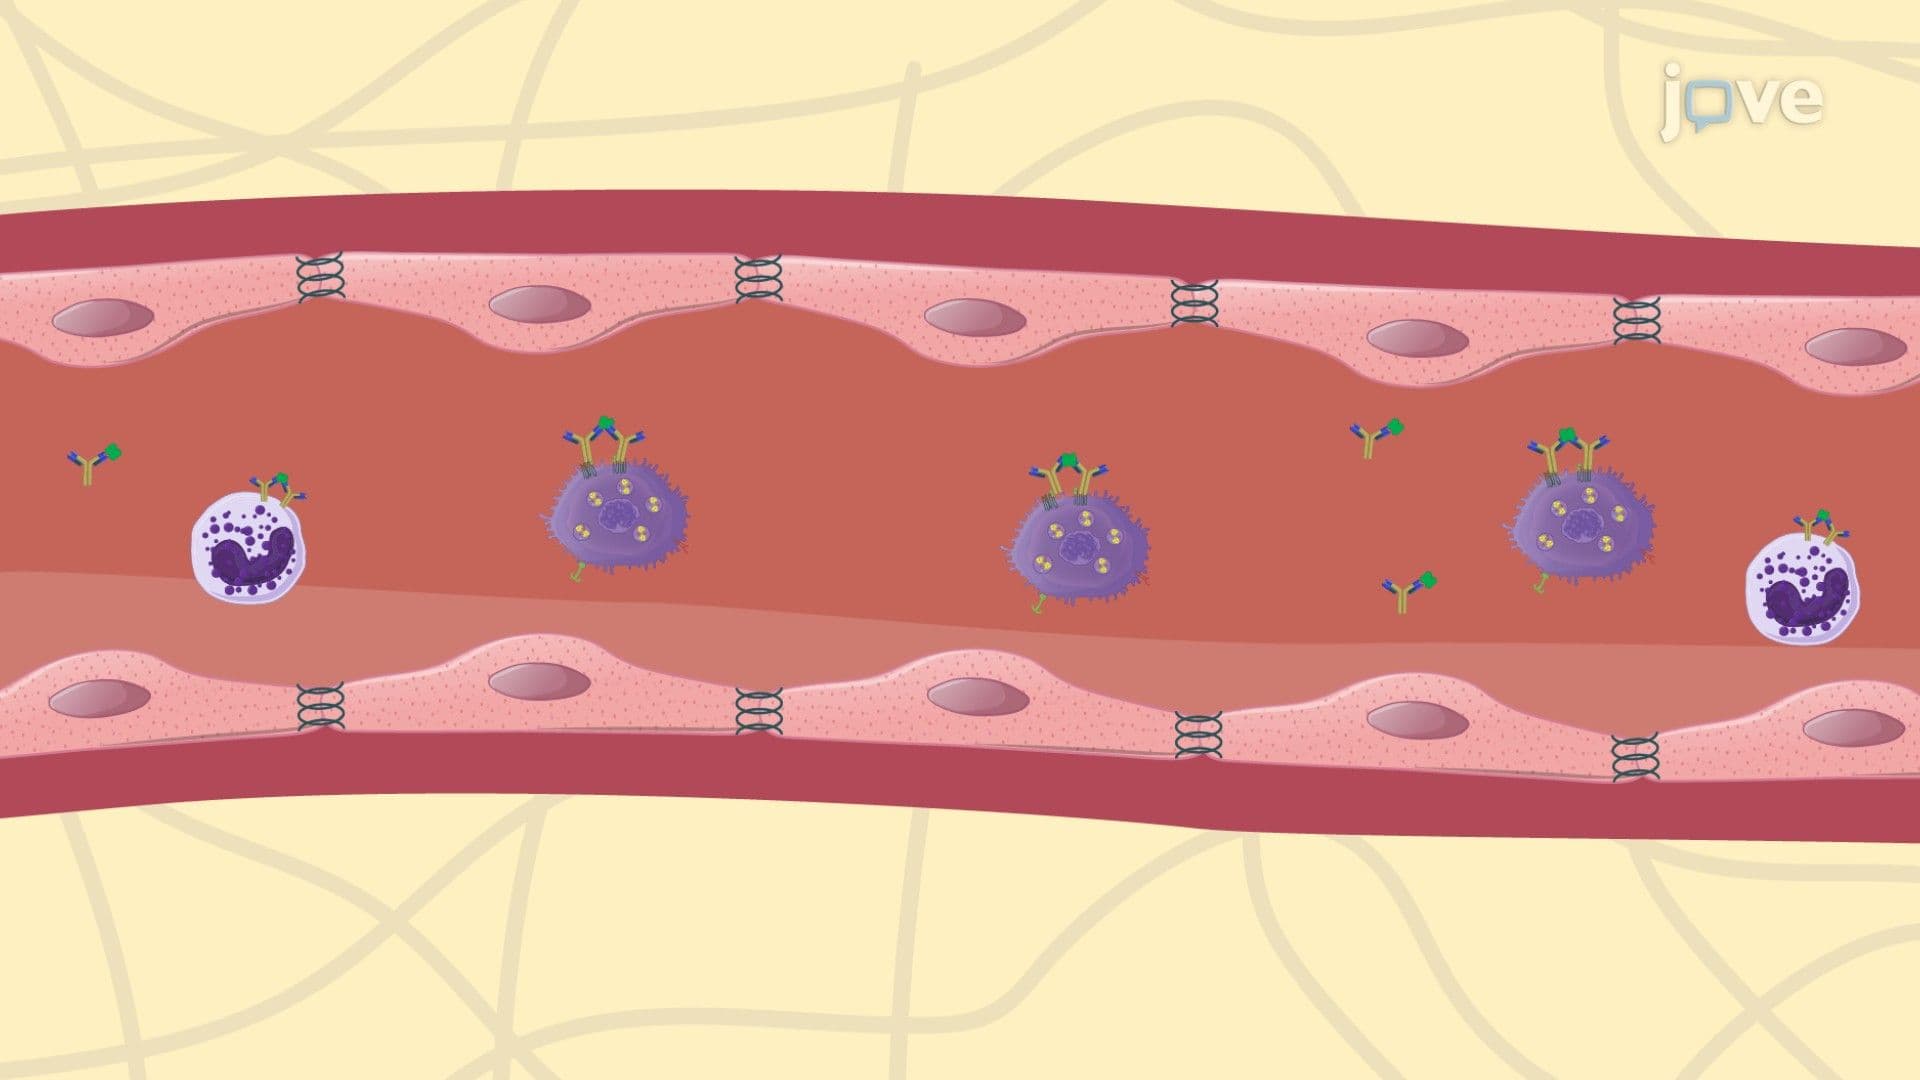
Drug Toxicity: Allergic Reactions