Related Experiment Video
Updated: Jul 11, 2026

03:57

Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Primary hyperparathyroidism and its management in a woman with hereditary long QT syndrome
Raymond Kennedy1, Sarah O'Hagan, Jawad Ahmad
1Department of Endocrine Surgery, Royal Victoria Hospital, Grosvenor Road, Belfast BT12 6BA, United Kingdom. rpg.kennedy@btinternet.com
The Ulster Medical Journal
|September 15, 2007

Abstract
No abstract available in PubMed .
Related Concept Videos
 01:27
Hyperthyroidism II: Pathophysiology
Hyperthyroidism is a hypermetabolic state caused by elevated levels of thyroid hormones, triiodothyronine (T3) and thyroxine (T4). It results from dysregulation at the thyroid, pituitary, or immune system level and affects multiple organ systems.PathophysiologyThe most common cause of hyperthyroidism is Graves’ disease, an autoimmune disorder in which antibodies, specifically thyroid-stimulating antibodies (TSAb), a subtype of TSH receptor antibodies (TRAb), bind to and activate TSH receptors...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
Hypertrophic cardiomyopathy, or HCM, is an autosomal dominant genetic disorder characterized by asymmetric left ventricular hypertrophy without ventricular dilation. It is more common in men and is typically diagnosed in young, athletic adults.EtiologyHCM is primarily genetic and is caused by mutations in genes encoding sarcomeric proteins. Researchers have identified over 1400 mutations across at least 11 different genes. Among these, the most frequently occurring mutations are found in the...
 01:25
Hyperthyroidism I: Introduction
Hyperthyroidism is a type of thyrotoxicosis characterized by the thyroid gland's overproduction of the thyroid hormones triiodothyronine (T3) and thyroxine (T4). This hormone excess increases the basal metabolic rate and enhances sensitivity to catecholamines.DiagnosisDiagnosis is based on clinical features and biochemical testing. It typically shows suppressed thyroid-stimulating hormone (TSH) levels below 0.4 mIU/L, with elevated free T3 and/or T4. Additional tests, including thyroid...
 00:59
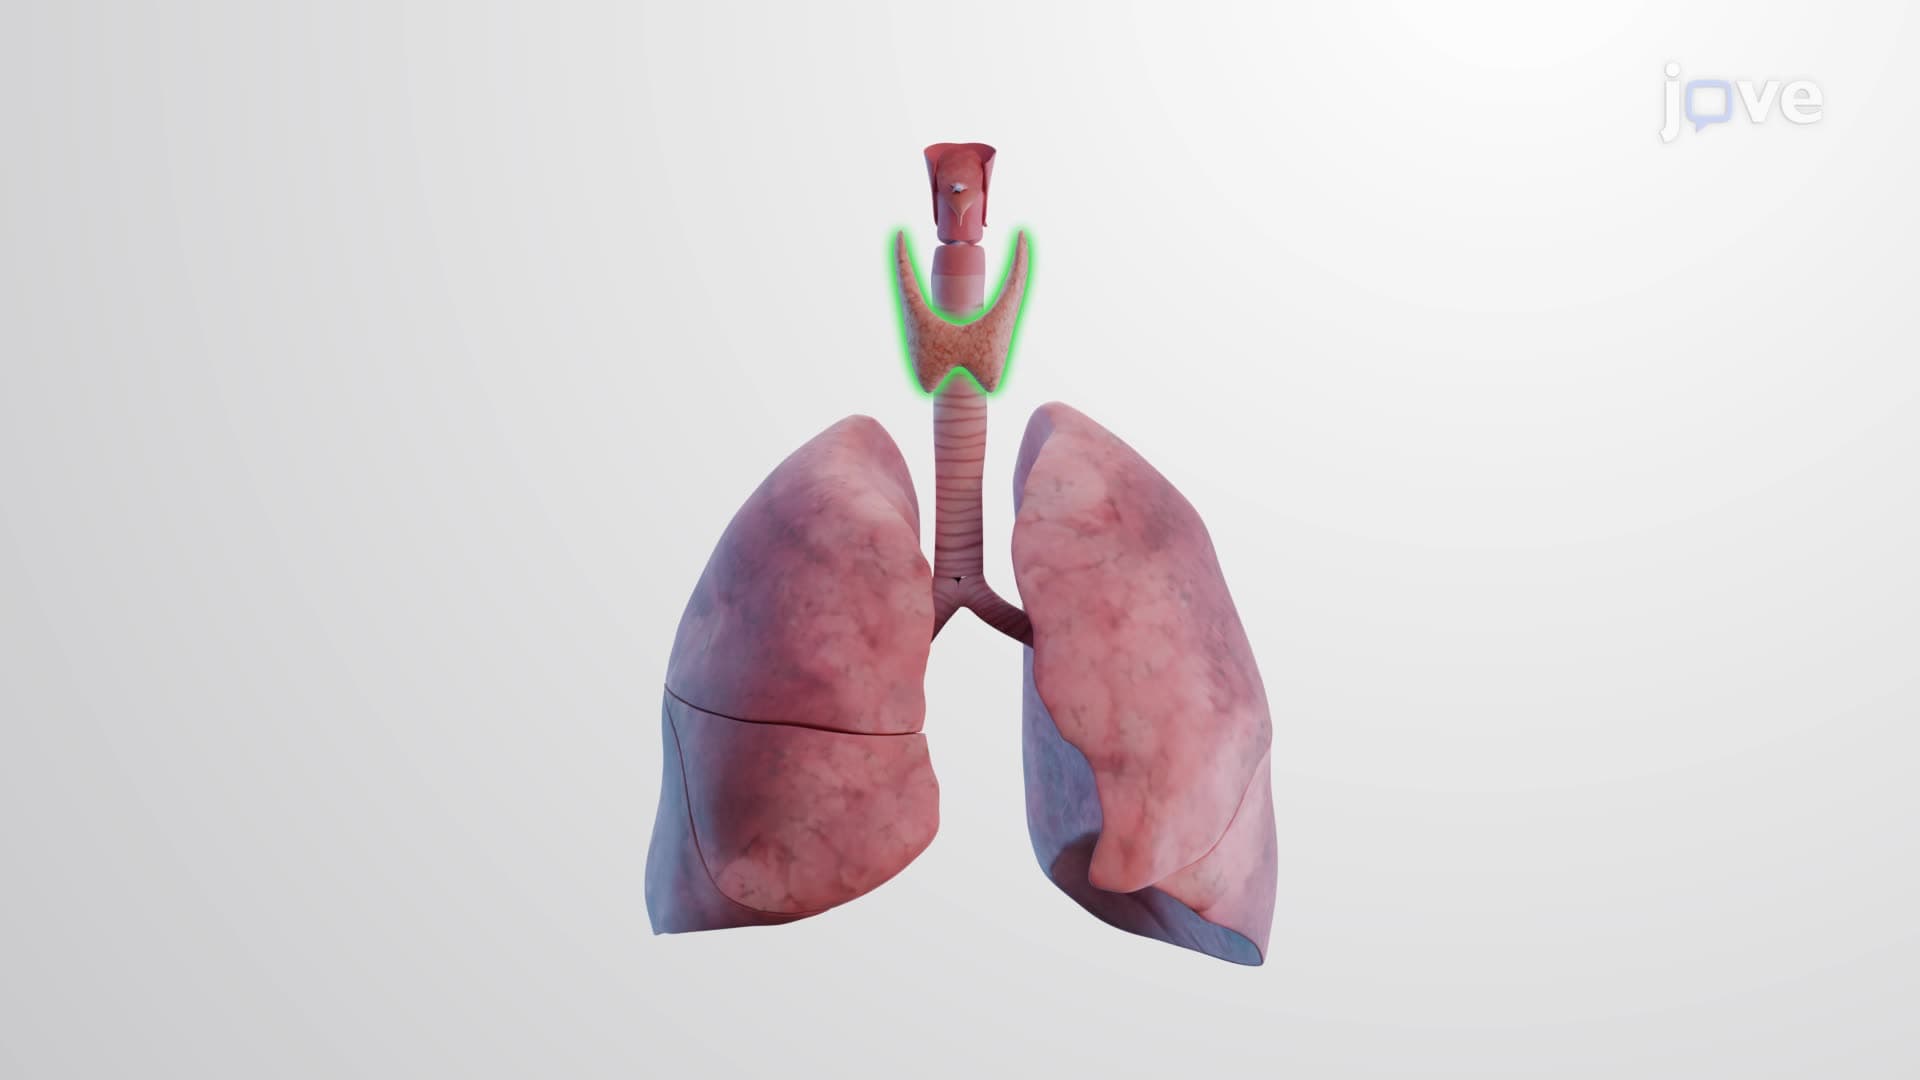
The Parathyroid Glands
The two pairs of parathyroid glands embedded within the posterior surface of the thyroid gland are restricted by a dense capsule around them. These glands comprise two distinct cell populations—parathyroid oxyphil and parathyroid principal cells- pivotal in calcium homeostasis.
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:24
Graves Disease II: Pathophysiology
Graves’ disease is an autoimmune disorder characterized by the production of thyroid-stimulating immunoglobulins (TSI) that activate TSH receptors, leading to excessive synthesis and release of thyroid hormones (T3 and T4) and resulting in hyperthyroidism.Among all causes of hyperthyroidism, Graves’ disease is the most common and can happen at any age, though it is more frequent in women. It produces a hypermetabolic state with features such as weight loss, tachycardia, tremor, and heat...
 01:25
Dysrhythmias VI: Management of Dysrhythmias
Dysrhythmia management involves a multifaceted approach, incorporating pharmacological treatments, medical procedures, surgical interventions, lifestyle modifications, and patient education.Pharmacological ManagementAntiarrhythmic Drugs:Class I (Sodium Channel Blockers): This class includes quinidine and procainamide, which reduce the speed of impulse conduction in the heart, stabilize the cardiac membrane, and control arrhythmias. Quinidine and procainamide are Class IA agents that prolong the...