Related Experiment Video
Updated: Jul 11, 2026
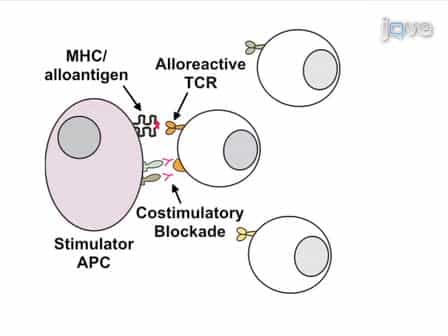

Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
Haploidentical allogeneic hematopoietic cell transplantation in adults using CD3/CD19 depletion and reduced intensity
Wolfgang A Bethge1, Christoph Faul, Martin Bornhäuser
1Medical Center, University of Tübingen, Hematology/Oncology Otfried-Mueller Str. 1072076 Tuebingen, Germany. wolfgang.bethge@med.uni-tuebingen.de

Haploidentical hematopoietic cell transplantation (HHCT) after high dose conditioning with CD34-selected stem cells has been complicated by high regimen related toxicities, slow engraftment and delayed immune reconstitution leading to increased treatment related mortality (TRM). A new regimen using reduced intensity conditioning (RIC) and graft CD3/CD19 depletion with anti-CD3 and anti-CD19 coated microbeads on a CliniMACS device may allow HHCT with lower toxicity and faster engraftment. CD3/CD19 depleted grafts not only contain CD34+ stem cells but also CD34 negative progenitors, natural killer, graft facilitating and dendritic cells. RIC was performed with fludarabine (150-200 mg/m(2)), thiotepa (10 mg/kg), melphalan (120 mg/m(2)) and OKT-3 (5 mg/day, day -5 to +14) and no posttransplant immunosuppression. Twenty nine patients (median age=42 (range, 21-59) years) have been transplanted with this regimen. Diagnosis were AML (n=16), ALL (n=7), NHL (n=3), MM (n=2) and CML (n=1). Patients were "high risk" with refractory disease or relapse after preceding HCT. The CD3/CD19 depleted haploidentical grafts contained a median of 7.6x10(6) (range, 3.4-17x10(6)) CD34+ cells/kg, 4.4x10(4) (range, 0.006-44x10(4)) CD3+ T cells/kg and 7.2x10(7) (range, 0.02-37.3x10(7)) CD56+ cells/kg. Donor-recipient KIR-ligand-mismatch was found in 19 of 29 patients. The regimen was well tolerated with maximum acute toxicity being grade 2-3 mucositis. Because of severe neurotoxicity in 4 patients treated with 200 mg/m(2) fludarabine, the dose was reduced to 150 mg/m(2). Engraftment was rapid with a median time to >500 granulocytes/microL of 12 (range, 10-21) days, >20,000 platelets/microL of 11 (range, 7-38) days and full donor chimerism after 2-4 weeks in all patients. Incidence of grade II-IV degrees GVHD was 48% with grade II degrees =10, III degrees =2 and IV degrees =2. One patient, who received the highest T-cell dose, developed lethal grade IV GVHD. TRM in the first 100 days was 6/29 (20%) with deaths due to idiopathic pneumonia syndrome (n=1), mucormycosis (n=1), pneumonia (n=3) or GVHD (n=1). Overall survival is 9/29 patients (31%) with deaths due to infections (n=7), GVHD (n=1) and relapse (n=12) with a median follow-up of 241 days (range, 112-1271). In conclusion, this regimen is promising in high risk patients lacking a suitable donor, and a prospective phase I/II study is ongoing.
Haploidentical hematopoietic cell transplantation (HHCT) after high dose conditioning with CD34-selected stem cells has been complicated by high regimen related toxicities, slow engraftment and delayed immune reconstitution leading to increased treatment related mortality (TRM). A new regimen using reduced intensity conditioning (RIC) and graft CD3/CD19 depletion with anti-CD3 and anti-CD19 coated microbeads on a CliniMACS device may allow HHCT with lower toxicity and faster engraftment. CD3/CD19 depleted grafts not only contain CD34+ stem cells but also CD34 negative progenitors, natural killer, graft facilitating and dendritic cells. RIC was performed with fludarabine (150-200 mg/m(2)), thiotepa (10 mg/kg), melphalan (120 mg/m(2)) and OKT-3 (5 mg/day, day -5 to +14) and no posttransplant immunosuppression. Twenty nine patients (median age=42 (range, 21-59) years) have been transplanted with this regimen. Diagnosis were AML (n=16), ALL (n=7), NHL (n=3), MM (n=2) and CML (n=1). Patients were "high risk" with refractory disease or relapse after preceding HCT. The CD3/CD19 depleted haploidentical grafts contained a median of 7.6x10(6) (range, 3.4-17x10(6)) CD34+ cells/kg, 4.4x10(4) (range, 0.006-44x10(4)) CD3+ T cells/kg and 7.2x10(7) (range, 0.02-37.3x10(7)) CD56+ cells/kg. Donor-recipient KIR-ligand-mismatch was found in 19 of 29 patients. The regimen was well tolerated with maximum acute toxicity being grade 2-3 mucositis. Because of severe neurotoxicity in 4 patients treated with 200 mg/m(2) fludarabine, the dose was reduced to 150 mg/m(2). Engraftment was rapid with a median time to >500 granulocytes/microL of 12 (range, 10-21) days, >20,000 platelets/microL of 11 (range, 7-38) days and full donor chimerism after 2-4 weeks in all patients. Incidence of grade II-IV degrees GVHD was 48% with grade II degrees =10, III degrees =2 and IV degrees =2. One patient, who received the highest T-cell dose, developed lethal grade IV GVHD. TRM in the first 100 days was 6/29 (20%) with deaths due to idiopathic pneumonia syndrome (n=1), mucormycosis (n=1), pneumonia (n=3) or GVHD (n=1). Overall survival is 9/29 patients (31%) with deaths due to infections (n=7), GVHD (n=1) and relapse (n=12) with a median follow-up of 241 days (range, 112-1271). In conclusion, this regimen is promising in high risk patients lacking a suitable donor, and a prospective phase I/II study is ongoing.
Related Concept Videos
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...
 01:21
Stem Cell Therapy for Tissue Regeneration
Types of Stem Cells used in Stem Cell Therapy
The two main cell types that...
 01:01
Regulation of Hematopoietic Stem Cells