A comparative study of release of interleukin-6 and tumour necrosis factor during normothermic and hypothermic cardiopulmonary bypass
Related Experiment Video
Updated: Jul 11, 2026

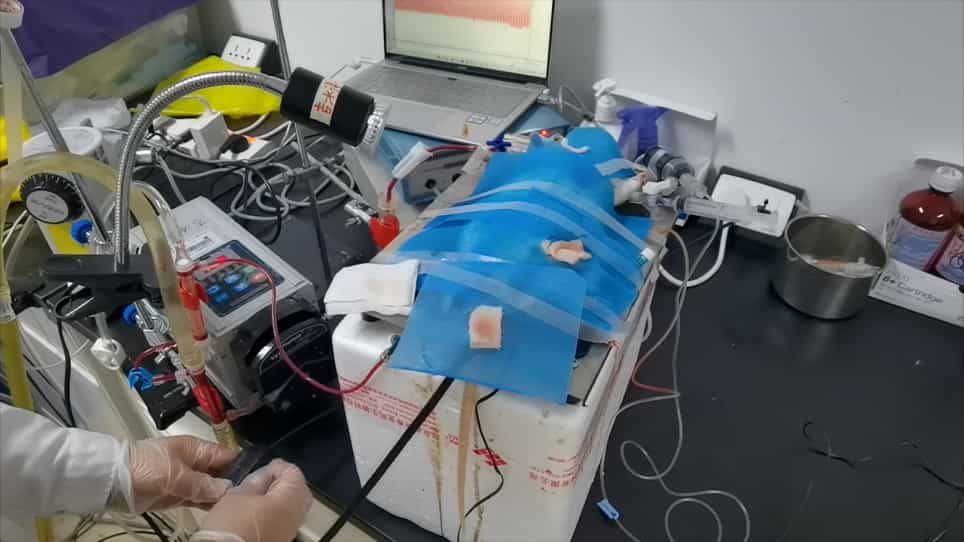
A Recovery Cardiopulmonary Bypass Model Without Transfusion or Inotropic Agents in Rats
Published on: March 23, 2018
Sandur Narasimhamurthy Naresh1, Mukul Chandra Kapoor, Trichur Ramaswamy Ramchandran
1Department of Anaesthesiology, Army Hospital Research and Referral, Delhi Cantt, Delhi, India.

Abstract:
The institution of cardiopulmonary bypass generates many pro-inflammatory cytokines and several clinical variables, including temperature, have been shown to influence cytokine release during and after cardiopulmonary bypass. The release of tumour necrosis factor and interleukin-6 are the best predictors of post-cardiopulmonary bypass related morbidity. Their release during normothermic and hypothermic cardiopulmonary bypass and the correlation with clinical parameters of organ injury was studied. This prospective study was carried out in 52 adult patients, scheduled for cardiac surgery, exposed to normothermic and 27 to hypothermic cardiopulmonary bypass. Samples for estimation of tumour necrosis factor and interleukin-6 were collected preoperatively, 1 hour and 24 hours post cardiopulmonary bypass and analysed by ELISA. Haemodynamic parameters and respiratory parameters were noted and lung injury scores calculated. Interleukin-6 levels were raised in both the groups at 1 hour and 24 hours post cardiopulmonary bypass and the response was higher in the normothermic group. Tumour necrosis factor response was, however, similar in both the groups, with a rise at 1 hour returning back to baseline by 24 hours post cardiopulmonary bypass. The normothermic group had a better respiratory index in the postoperative period, early extubation was possible, had better clinical haemodynamics, a shorter cardiopulmonary bypass time and had reduced requirement of defibrillation after the release of aortic cross clamp. We conclude that the release of interleukin-6 was thermo-dependent but did not correlate with the clinical signs of organ injury. Tumour necrosis factor levels were significantly raised after the cardiopulmonary bypass but the rise was not thermo-dependent.