Related Experiment Video
Updated: Feb 11, 2026
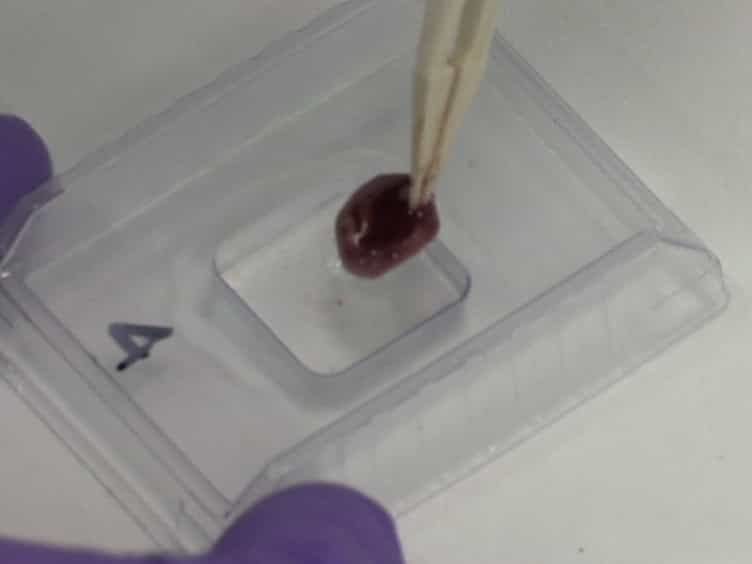

Histological Quantification of Chronic Myocardial Infarct in Rats
Published on: December 11, 2016
Infarct size, ejection fraction, and mortality in diabetic patients with acute myocardial infarction treated with
Jorge R Alegria1, Todd D Miller, Raymond J Gibbons
1Division of Cardiovascular Diseases, Department of Internal Medicine, Mayo Clinic, Rochester, MN 55905, USA.

Insights
Diabetic patients with acute myocardial infarction (MI) experience higher mortality. While larger infarct size and lower ejection fraction contribute, they only partially explain this increased risk in patients with ST-segment-elevation MI.
Area of Science:
- Cardiology
- Diabetology
- Medical Imaging
Background:
- Diabetic patients with acute myocardial infarction (MI) exhibit higher mortality rates compared to non-diabetic individuals.
- Investigating the role of infarct size in explaining this disparity is crucial for understanding ST-segment-elevation MI outcomes.
Purpose of the Study:
- To determine if larger infarct size accounts for the increased mortality observed in diabetic patients with acute ST-segment-elevation MI.
- To assess the relationship between infarct size, left ventricular ejection fraction (LVEF), and mortality in diabetic vs. non-diabetic patients post-MI.
Main Methods:
- Utilized data from the CORE trial, including quantitative radionuclide measurement of infarct size and gated equilibrium left ventricular ejection fraction (LVEF) in subsets of patients.
- Clinical follow-up was conducted at 6 months for 96.7% of patients.
Main Results:
- Diabetic patients (16-17% prevalence) had larger median infarct sizes (22% vs. 17%, P=.04) and lower median LVEF (48% vs. 51%, P=.002) compared to non-diabetic patients.
- Six-month mortality was significantly higher in diabetic patients across both infarct size (5.9% vs. 1.6%, P=.0016) and LVEF (6.1% vs. 1.0%, P<.0001) subsets.
- Diabetes, infarct size, and LVEF were identified as independent predictors of mortality in multivariable analyses.
Conclusions:
- Diabetic patients with ST-segment-elevation MI present with modestly larger infarct sizes and lower LVEF.
- The significantly higher mortality in diabetic patients is only partially explained by these imaging-derived variables, suggesting other contributing factors.
- Further research is needed to fully elucidate the mechanisms behind the elevated mortality in diabetic individuals post-MI.
Background:
Diabetic patients with acute myocardial infarction (MI) have higher mortality than nondiabetic patients. The purpose of this study was to examine if larger infarct size explains the higher mortality in diabetic patients with acute ST-segment-elevation MI.
Methods:
In the CORE trial (n = 2948), subsets of patients underwent quantitative radionuclide measurement of technetium Tc 99m sestamibi infarct size (n = 1164) or gated equilibrium left ventricular ejection fraction (LVEF) (n = 1137) at days 6 to 16 after thrombolytic therapy. Clinical follow-up was 96.7% complete at 6 months.
Results:
The prevalence of diabetes in these patient imaging subsets was 16% to 17%. Higher risk clinical characteristics including older age and a greater prevalence of prior MI were more common in diabetic patients. Median infarct size was larger in diabetic patients (22% vs 17% of the left ventricle, P = .04), a difference that remained significant after adjustment for clinical variables (P = .048). Patients with diabetes also had lower median LVEF (48% vs 51%, unadjusted P = .002, adjusted P = .007). Six-month mortality was higher in diabetic patients: infarct size subset, 5.9% vs 1.6% (P = .0016); LVEF subset, 6.1% vs 1.0% (P < .0001). Multivariable models demonstrated that diabetes and each imaging variable were independent predictors of mortality.
Conclusions:
Infarct size is modestly larger and LVEF modestly lower in diabetic patients with ST-segment-elevation MI. The substantially higher (4- to 6-fold) mortality rate in diabetic vs nondiabetic patients is only partially explained by relatively small differences in infarct size and LVEF.

Related Concept Videos
 01:28
Partial Fractions
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 00:59
Gene Therapy
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:22
Cell Size
Surface Area
Cells can take in nutrients and water via diffusion through the plasma membrane itself or through specific channels in the membrane. The area of the membrane surrounding...
 01:32
Subcellular Fractionation
Differential Centrifugation
Differential centrifugation is...