Related Experiment Video
Updated: Jul 11, 2026


Recognition of Epidermal Transglutaminase by IgA and Tissue Transglutaminase 2 Antibodies in a Rare Case of Rhesus Dermatitis
Published on: December 15, 2011
Pseudotumors due to IgG4 immune-complex tubulointerstitial nephritis associated with autoimmune pancreatocentric
Lynn D Cornell1, Sonia L Chicano, Vikram Deshpande
1Departments of Pathology, Massachusetts General Hospital, 55 Fruit Street, Boston, MA 02114, USA. cornell@alum.mit.edu

Abstract:
Autoimmune pancreatitis (AIP) is a mass-forming chronic fibroinflammatory condition centered on the pancreatobiliary system and characterized by predominant immunoglobulin G4 (IgG4)-positive plasma cells. Recent reports have brought to light the multiorgan involvement of this disease. We describe a series of 5 cases of tubulointerstitial nephritis (TIN) associated with AIP and characterize the clinical, pathologic, ultrastructural, and immunopathologic features of TIN. The specimens consisted of 4 biopsies and 1 nephrectomy. The average patient age was 64 years (range 45 to 78) and the male to female ratio was 4:1. All had histologic and/or clinical and radiographic evidence of AIP, mass-forming sclerosing cholangitis, or both. The clinical impression in 4 patients was a renal mass or vasculitis. Two patients had renal insufficiency. Histologic preparations revealed a dense tubulointerstitial lymphoplasmacytic infiltrate. Eosinophils were often numerous. Tubulitis and tubular injury were present, along with tubular atrophy with focally thickened tubular basement membranes (TBMs). The histologic appearance ranged from a cellular, inflammatory pattern without tubular atrophy to a striking expansive interstitial fibrosis with tubular destruction. The nephrectomy specimen demonstrated a masslike nodular pattern of inflammation with normal renal tissue elsewhere. Glomeruli were uninvolved. By immunohistochemistry or immunofluorescence, numerous plasma cells in the infiltrate were positive for IgG4. TBM granular IgG deposits, predominantly of the IgG4 subclass, were detected in 4 of 5 cases by either immunofluorescence or immunohistochemistry. By electron microscopy, corresponding amorphous electron-dense deposits were present in the TBM in these cases. This type of TIN, typically characterized by a masslike lesion consisting of a lymphoplasmacytic infiltrate with eosinophils and prominent IgG4-positive plasma cells and immune-complex deposits in the TBM, may be part of a systemic IgG4-related disease, which we term "IgG4-associated immune complex Multiorgan Autoimmune Disease" (IMAD).
More Related Videos
 10:10
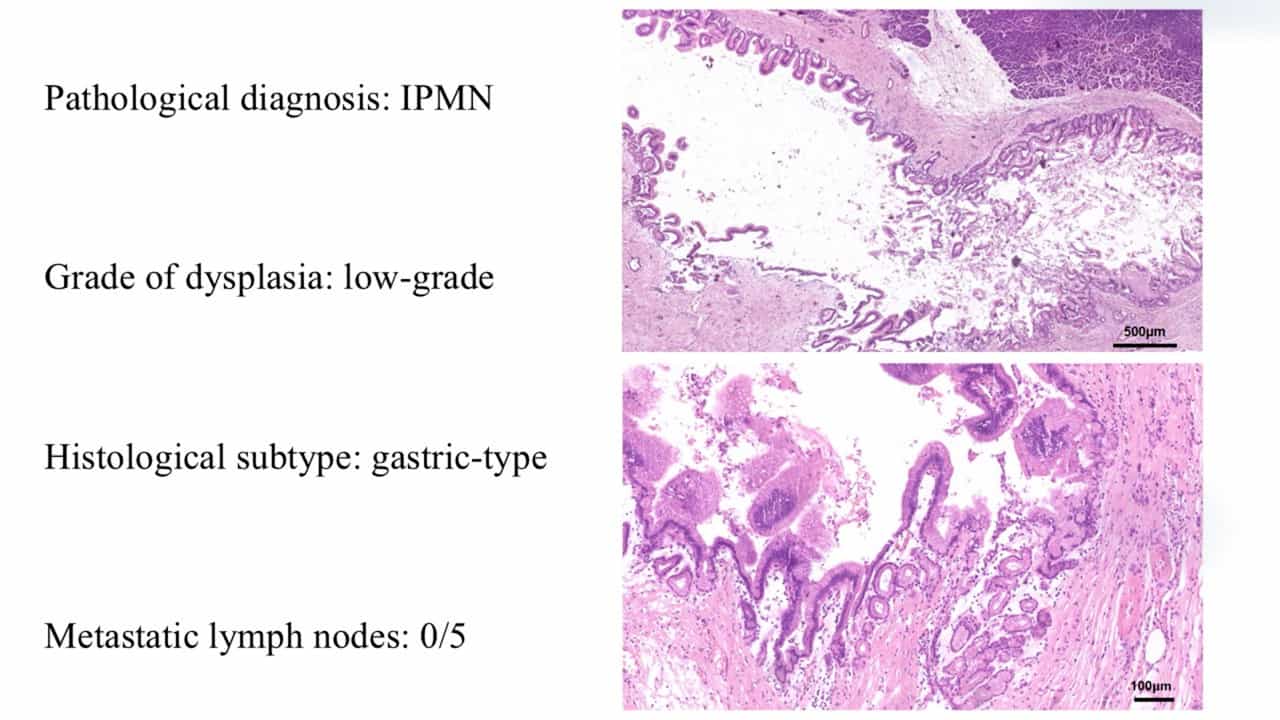
Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
 14:18
Dioscin Mediated IgA Nephropathy Alleviation by Inhibiting B Cell Activation In Vivo and Decreasing Galactose-Deficient IgA1 Production In Vitro
Published on: October 13, 2023
Related Concept Videos
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:12
Type I Diabetes I: Introduction
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:25
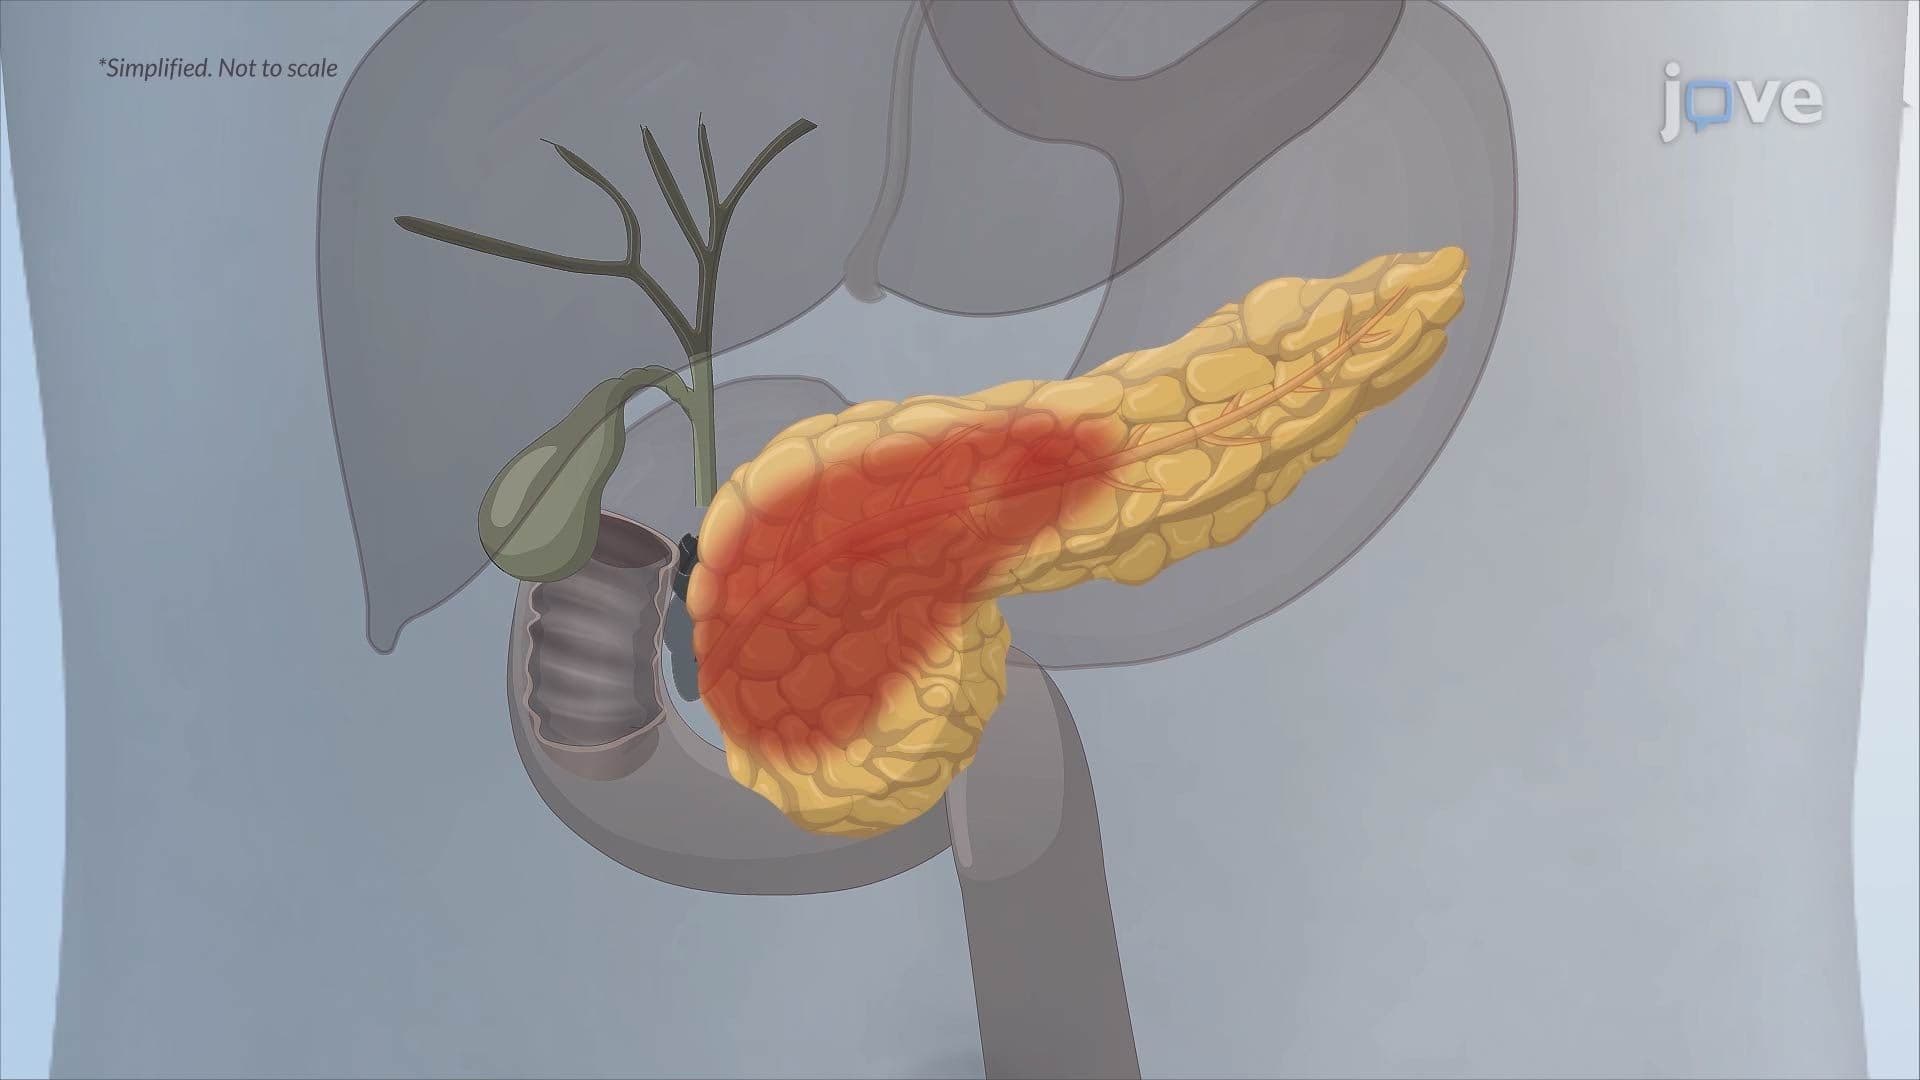
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:21
Acute Pancreatitis II: Pathophysiology