Related Experiment Video
Updated: Jul 11, 2026
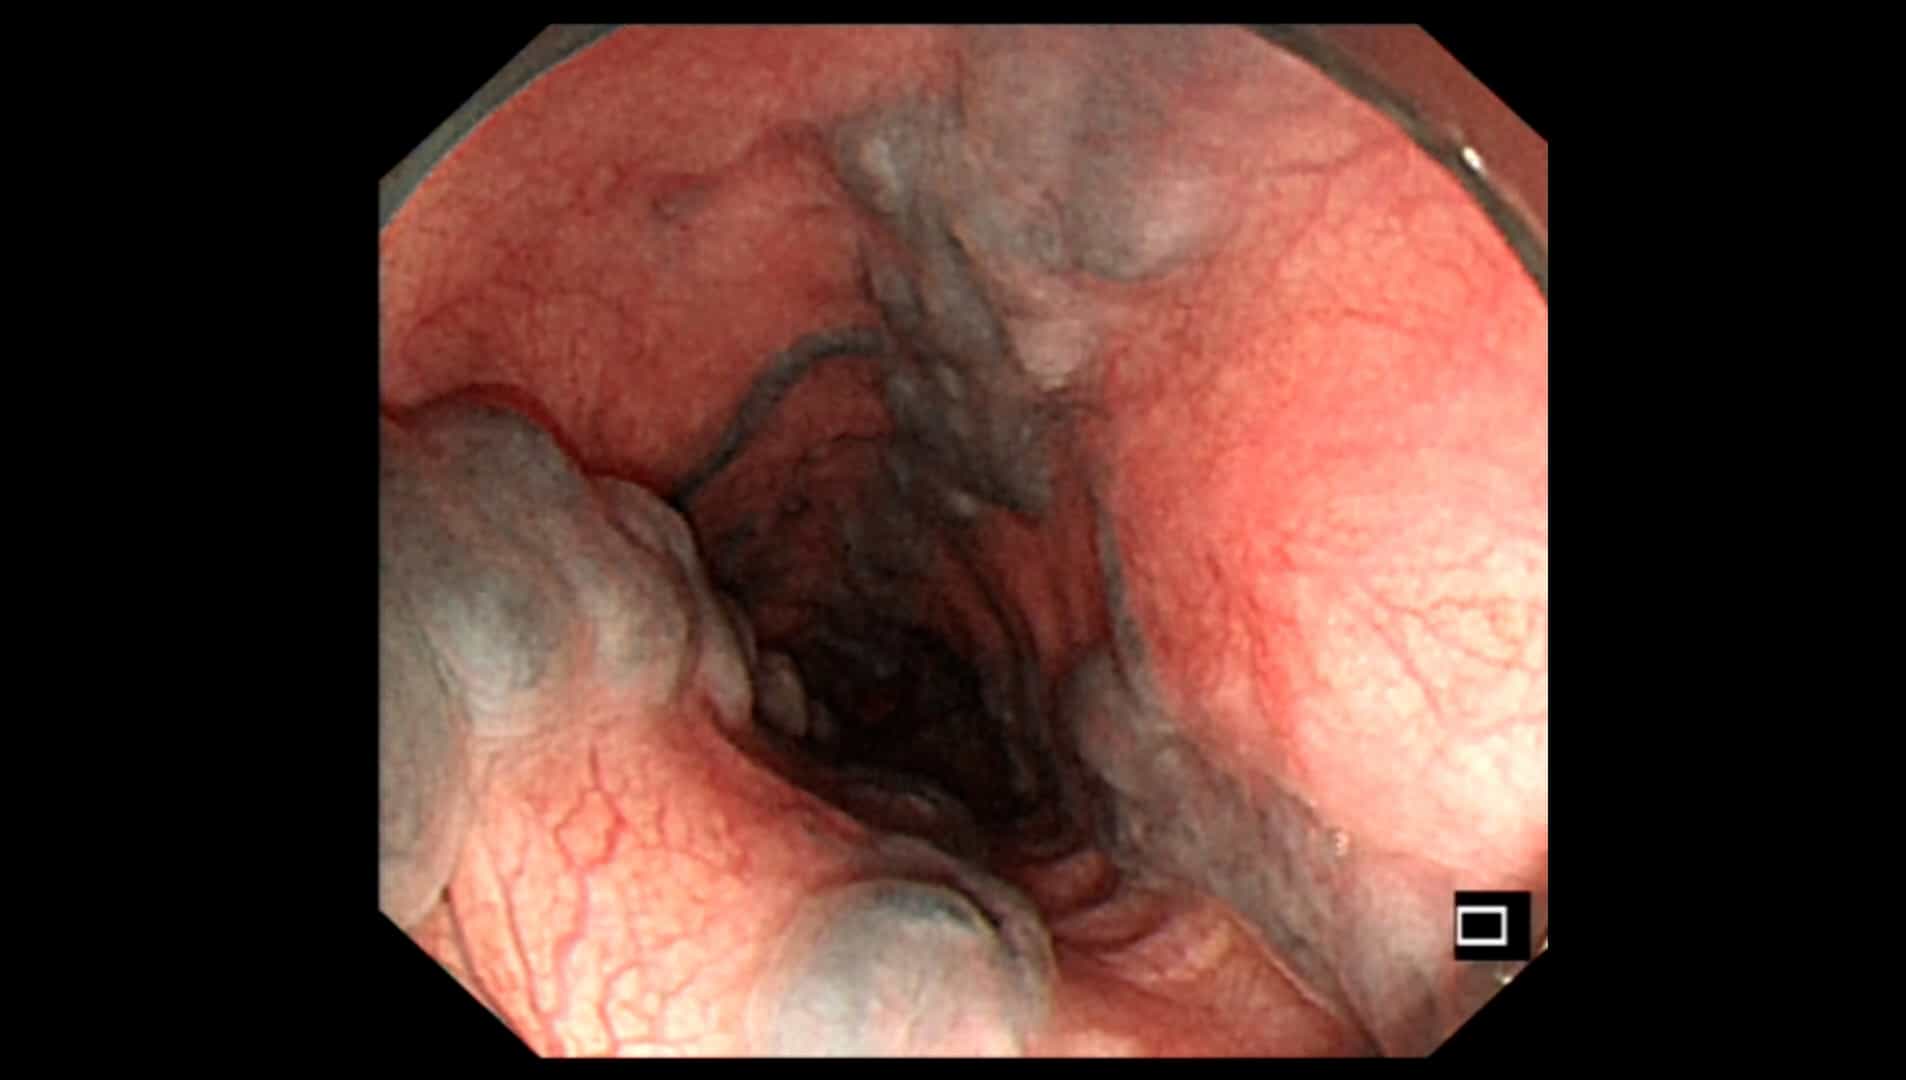

Underwater Endoscopic Injection Sclerotherapy for Gastroesophageal Varices
Published on: August 1, 2025
Endoscopic abnormalities in the oesophagus after variceal sclerotherapy--a long-term follow up study
Varghese Thomas1, Jose Tony, K Harish
1Department of Gastroenterology, Medical College Hospital, Calicut - 673 008, Kerala, India. drvarghesethomas@gmail.com

Abstract:
Endoscopic sclerotherapy is a well-established treatment modality for oesophageal varices. Various local, regional and systemic complications occur after sclerotherapy. Altered endoscopic appearances of the oesophagus have been observed on follow-up of patients after sclerotherapy. 171 consecutive patients with extra-hepatic portal venous obstruction on follow up after achieving variceal eradication by sclerotherapy during the period from January 2004 to June 2005 were enrolled in this study. The oesophagus was closely observed for mucosal abnormalities and the endoscopic findings were recorded. Out of 171 patients, 95 (55.5%) patients had no specific endoscopic changes in the oesophagus. The most common finding was mucosal neovascularization which was seen in 56 (32.7%) patients. Oval or oblong depressed areas were seen in 41 (23.9%) patients. Mucosal tags and polypoidal lesions were seen in 37 (21.6%) patients. 25 (15.6%) patients had stenosis of the lower oesophagus and 3 (1.7%) patients had mucosal bridges. On multivariate analysis, these abnormal endoscopic findings in the oesophagus correlated with the total volume of sclerosant injected when compared with those patients without similar findings on endoscopy (p value < 0.001). Endoscopic sclerotherapy leads to various abnormalities at the injection sites like neovascularization, oval or oblong depressed areas, mucosal tags, polypoidal lesions, stenosis and mucosal bridges. Endoscopic abnormalities correlated with the total volume of sclerosant used. The long-term significance of these changes is not known at present and further follow-up studies will be required.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...