Related Experiment Video
Updated: Jul 11, 2026

Laparoscopic Common Bile Duct Exploration in Patients with a Previous History of Biliary Tract Surgery
Published on: February 10, 2023
Small bowel obstruction due to broad ligament hernia successfully treated by laparoscopy
Miguel Garcia-Oria1, Josep Inglada, Josep Domingo
1Department of Surgery, Hospital de Figueres, Figueres, Spain. garcia-oria@operacio.com

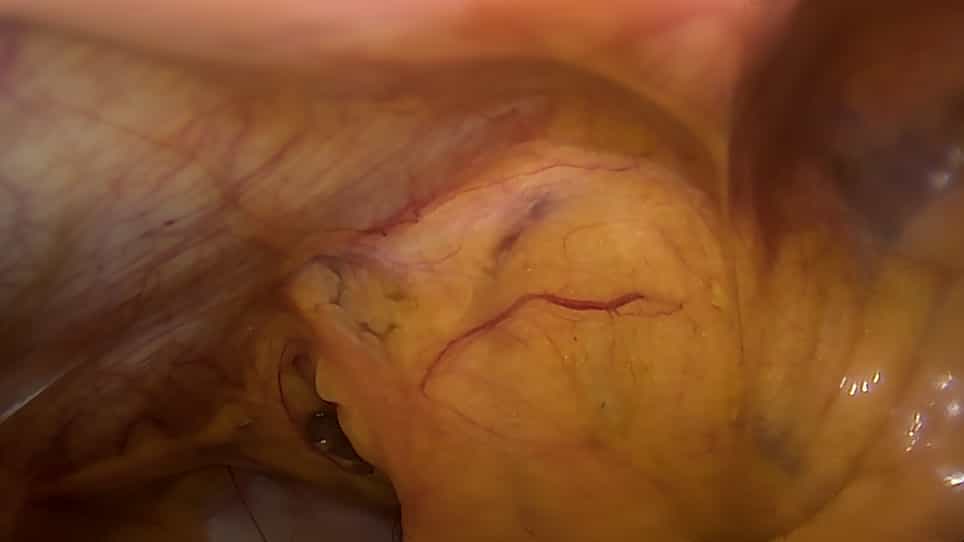
We present the second case of a broad ligament hernia to be treated by laparoscopy. A 43-year-old gravida 0, para 0 woman presented to our hospital with a chief complaint of right upper quadrant abdominal colicky pain and vomiting. Her clinical history was significant for an "unknown" bowel surgery through a Pfannenstiel incision. Her abdomen was soft, nondistended, and slightly tender to palpation in the right upper quadrant. The laboratory tests showed an elevated white blood cell count of 15.2 [1] 109/L with a left shift, and a normal serum C-reactive protein. Plain abdominal X-rays showed a lightly prominent small bowel loop in the pelvic area. An abdominal ultrasound revealed only a small amount of fluid in the pouch of Douglas. After 24 hours, the pain had migrated to the hypogastrium. There was an increase in the white blood cell count, in the C-reactive protein level, and in her temperature (37.7 degrees C). At this stage, we elected to perform an urgent laparoscopic exploration. We discovered 60-80 cm of ileum strangulated through a 2 x 3 cm defect in the left broad ligament of the uterus. The strangulated bowel was successfully reduced and the defect was closed with a 2-0 silk running suture. No bowel resection was required. The patient was discharged from the hospital on day 4, with no postoperative complications.
We present the second case of a broad ligament hernia to be treated by laparoscopy. A 43-year-old gravida 0, para 0 woman presented to our hospital with a chief complaint of right upper quadrant abdominal colicky pain and vomiting. Her clinical history was significant for an "unknown" bowel surgery through a Pfannenstiel incision. Her abdomen was soft, nondistended, and slightly tender to palpation in the right upper quadrant. The laboratory tests showed an elevated white blood cell count of 15.2 [1] 109/L with a left shift, and a normal serum C-reactive protein. Plain abdominal X-rays showed a lightly prominent small bowel loop in the pelvic area. An abdominal ultrasound revealed only a small amount of fluid in the pouch of Douglas. After 24 hours, the pain had migrated to the hypogastrium. There was an increase in the white blood cell count, in the C-reactive protein level, and in her temperature (37.7 degrees C). At this stage, we elected to perform an urgent laparoscopic exploration. We discovered 60-80 cm of ileum strangulated through a 2 x 3 cm defect in the left broad ligament of the uterus. The strangulated bowel was successfully reduced and the defect was closed with a 2-0 silk running suture. No bowel resection was required. The patient was discharged from the hospital on day 4, with no postoperative complications.
More Related Videos
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
 03:33
Laparoscopic Left Lateral Sectionectomy: Guided by the Ligamentum Teres Hepatis and the Umbilical Fissure Vein
Published on: September 27, 2024
Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:29
Intestinal Obstruction I: Introduction