Related Experiment Video
Updated: Jul 11, 2026


A Method of Trigonometric Modelling of Seasonal Variation Demonstrated with Multiple Sclerosis Relapse Data
Published on: December 9, 2015
Response to teriparatide in patients with baseline 25-hydroxyvitamin D insufficiency or sufficiency
Bess Dawson-Hughes1, Peiqi Chen, John H Krege
1Jean Mayer US Department of Agriculture Human Nutrition Research Center on Aging, Tufts University, 711 Washington Street, Boston, Massachusetts 02111-1524, USA. bess.dawson-hughes@tufts.edu

Context:
Serum 25-hydroxyvitamin D (25OHD) concentrations greater than 30 ng/ml have been recommended for lowering fracture risk.
Objective:
Our objective was to determine whether 25OHD sufficiency is a prerequisite for effective response to teriparatide (TPTD).
Design And Patients:
Data were from 1620 osteoporotic postmenopausal women in the Fracture Prevention Trial. The response to TPTD was assessed in women subgrouped by having 25OHD insufficiency (>10 but
Interventions:
At baseline, after at least 1 month of supplementation with calcium (1000 mg) and vitamin D (400-1200 IU) daily, women were randomized to placebo or 20 or 40 microg TPTD by daily sc injection for a median of 19 months. Observation was for a median of 21 months.
Main Outcome Measures:
Main outcome measures included vertebral and nonvertebral fractures, change in bone mineral density at the lumbar spine and femoral neck, change in bone formation marker amino-terminal extension peptide of procollagen type 1, and the proportion of women with serum calcium at least 2.76 mmol/liter 4-6 h after dosing.
Results:
TPTD reduced vertebral and nonvertebral fracture risk, increased lumbar spine and femoral neck bone mineral density, and increased amino-terminal extension peptide of procollagen type 1 relative to placebo in the two 25OHD subgroups. There were no significant differences in these endpoints between the subgroups (each treatment by subgroup interaction, P > 0.10). However, it should be noted that because of the limited number of fractures, this study does not exclude the possibility of differences in fracture outcome between the subgroups.
Conclusions:
In postmenopausal women with osteoporosis and normal intact PTH, the responses to TPTD did not differ significantly in women with baseline 25OHD insufficiency or sufficiency.
Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:21
Skeleton and Calcium Homeostasis
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:22
Connective Tissue Cell Types
Fat cells (adipocytes), smooth muscle cells (myoblasts), and bone cells (osteoblasts) are some connective tissue cell types. Some immune system cells...
 01:23
Role of Skin in Vitamin D Synthesis
The solar UV B rays (290-315 nm) are absorbed by the skin, and 7-dehydrocholesterol (provitamin D3) photolyzes it to previtamin D3, which undergoes a rapid transformation to vitamin D3(cholecalciferol).
 00:59
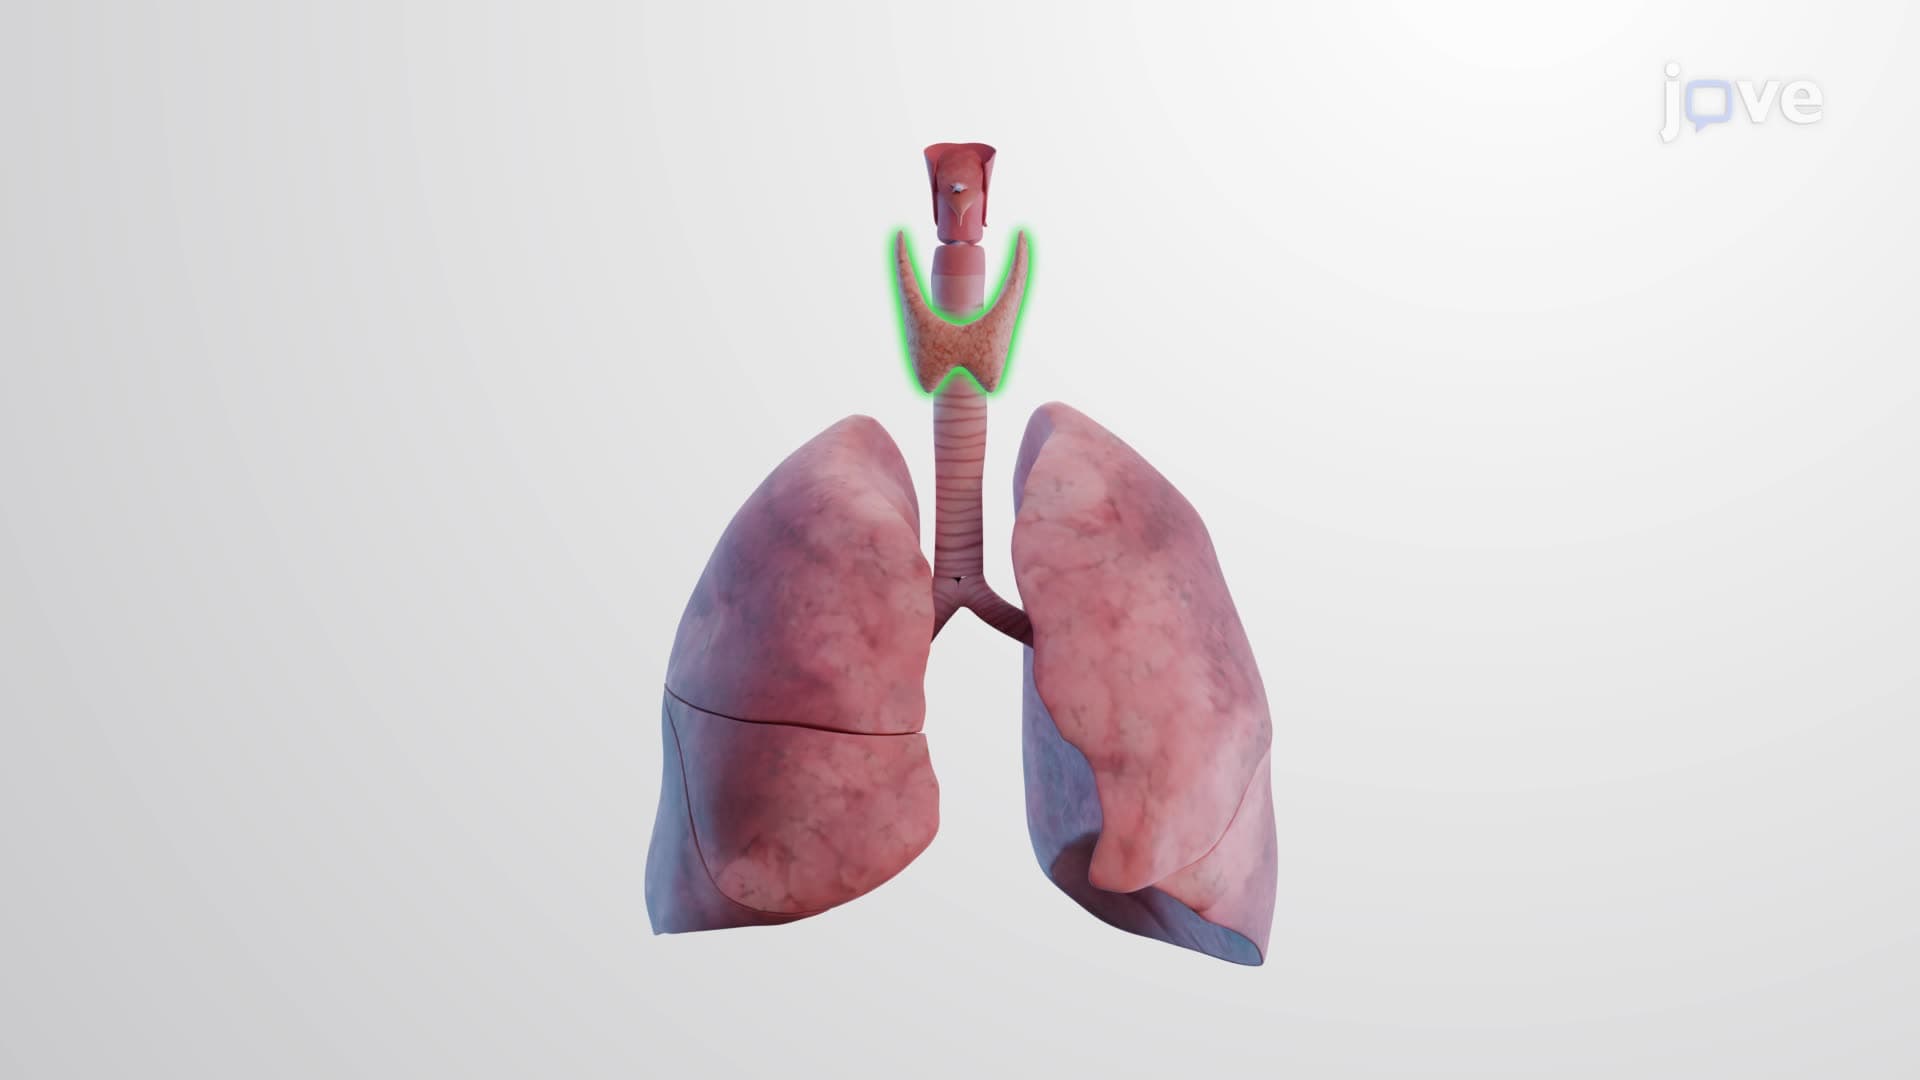
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...