Related Experiment Videos
Chlamydia pneumoniae seropositivity in aetiological subtypes of brain infarction and carotid atherosclerosis: a case
S Alamowitch1, J Labreuche, P-J Touboul
1Stroke Unit, Department of Neurology, Tenon University Hospital, AP-HP, 4 Rue de la Chine, Paris, France. sonia.alamowitch@tnn.aphp.fr

Insights
Chlamydia pneumoniae infection is not linked to brain infarction (BI) or carotid atherosclerosis. However, Chlamydia pneumoniae IgA antibodies may increase BI risk in normotensive individuals.
Area of Science:
- Neurology
- Infectious Diseases
- Cardiovascular Science
Background:
- Brain infarction (BI) often occurs without traditional risk factors.
- Infectious agents are potential contributors to stroke risk.
- Investigating Chlamydia pneumoniae as a potential factor in BI is warranted.
Purpose of the Study:
- To investigate the association between Chlamydia pneumoniae infection and brain infarction (BI).
- To examine this association across different etiological subtypes of BI.
- To assess the link between Chlamydia pneumoniae and carotid atherosclerosis.
Main Methods:
- Serum IgG and IgA to Chlamydia pneumoniae were measured in 483 BI cases and 483 controls.
- BI cases were confirmed by MRI and classified into etiological subtypes.
- Carotid atherosclerosis was assessed using duplex ultrasonography.
Main Results:
- Chlamydia pneumoniae IgG seropositivity showed no association with BI or its subtypes.
- Chlamydia pneumoniae IgA seropositivity was not generally linked to BI.
- IgA seropositivity increased BI risk in normotensive patients and those with BI of unknown cause.
Conclusions:
- Chlamydia pneumoniae infection is not associated with carotid atherosclerosis or most BI subtypes.
- A potential increased risk of BI exists in normotensive patients with Chlamydia pneumoniae IgA antibodies.
- Further research is needed to clarify the role of Chlamydia pneumoniae in specific stroke populations.
Background And Objective:
Many patients with brain infarction (BI) lack traditional risk factors, suggesting that other factors (including infectious agents) might contribute to stroke risk. We investigated Chlamydia pneumoniae infection in a large cohort of patients with BI according to aetiological subtypes and carotid atherosclerosis.
Methods:
We measured serum IgG and IgA to C. pneumoniae by microimmunofluorescence in 483 BI cases and 483 controls matched for age, sex and centre. IgG > or = 1/32 and IgA > or = 1/24 were considered positive. Cases with BI proven by magnetic resonance imaging were consecutively recruited and were classified into aetiological subtypes. Carotid atherosclerosis (intima-media thickness, plaques, stenosis) was evaluated by duplex ultrasonography in all subjects following the same method and with central reading.
Results:
C. pneumoniae IgG seropositivity was not associated with BI (adjusted odds ratio (OR) 1.10, 95% confidence interval (CI) 0.80-1.51) and did not increase the risk of any aetiological subtype. Overall, C. pneumoniae IgA was not associated with BI (adjusted OR 1.54, 95% CI 0.84-2.81), but there was a significant interaction with hypertension. IgA seropositivity increased the BI risk in patients without hypertension (adjusted OR 2.79, 95% CI 1.15 to 6.74). When stratifying BI into subtypes, IgA seropositivity increased the risk of BI of unknown cause, but without significant heterogeneity. There was neither association with atherothrombotic, lacunar and cardioembolic BI nor with carotid intima-media thickness, carotid plaques or stenosis.
Conclusions:
We found no evidence that C. pneumoniae seropositivity is associated with carotid atherosclerosis and BI, regardless of aetiological subtype; but it might be associated with an increased risk of BI in normotensive patients.
Related Concept Videos
 01:29
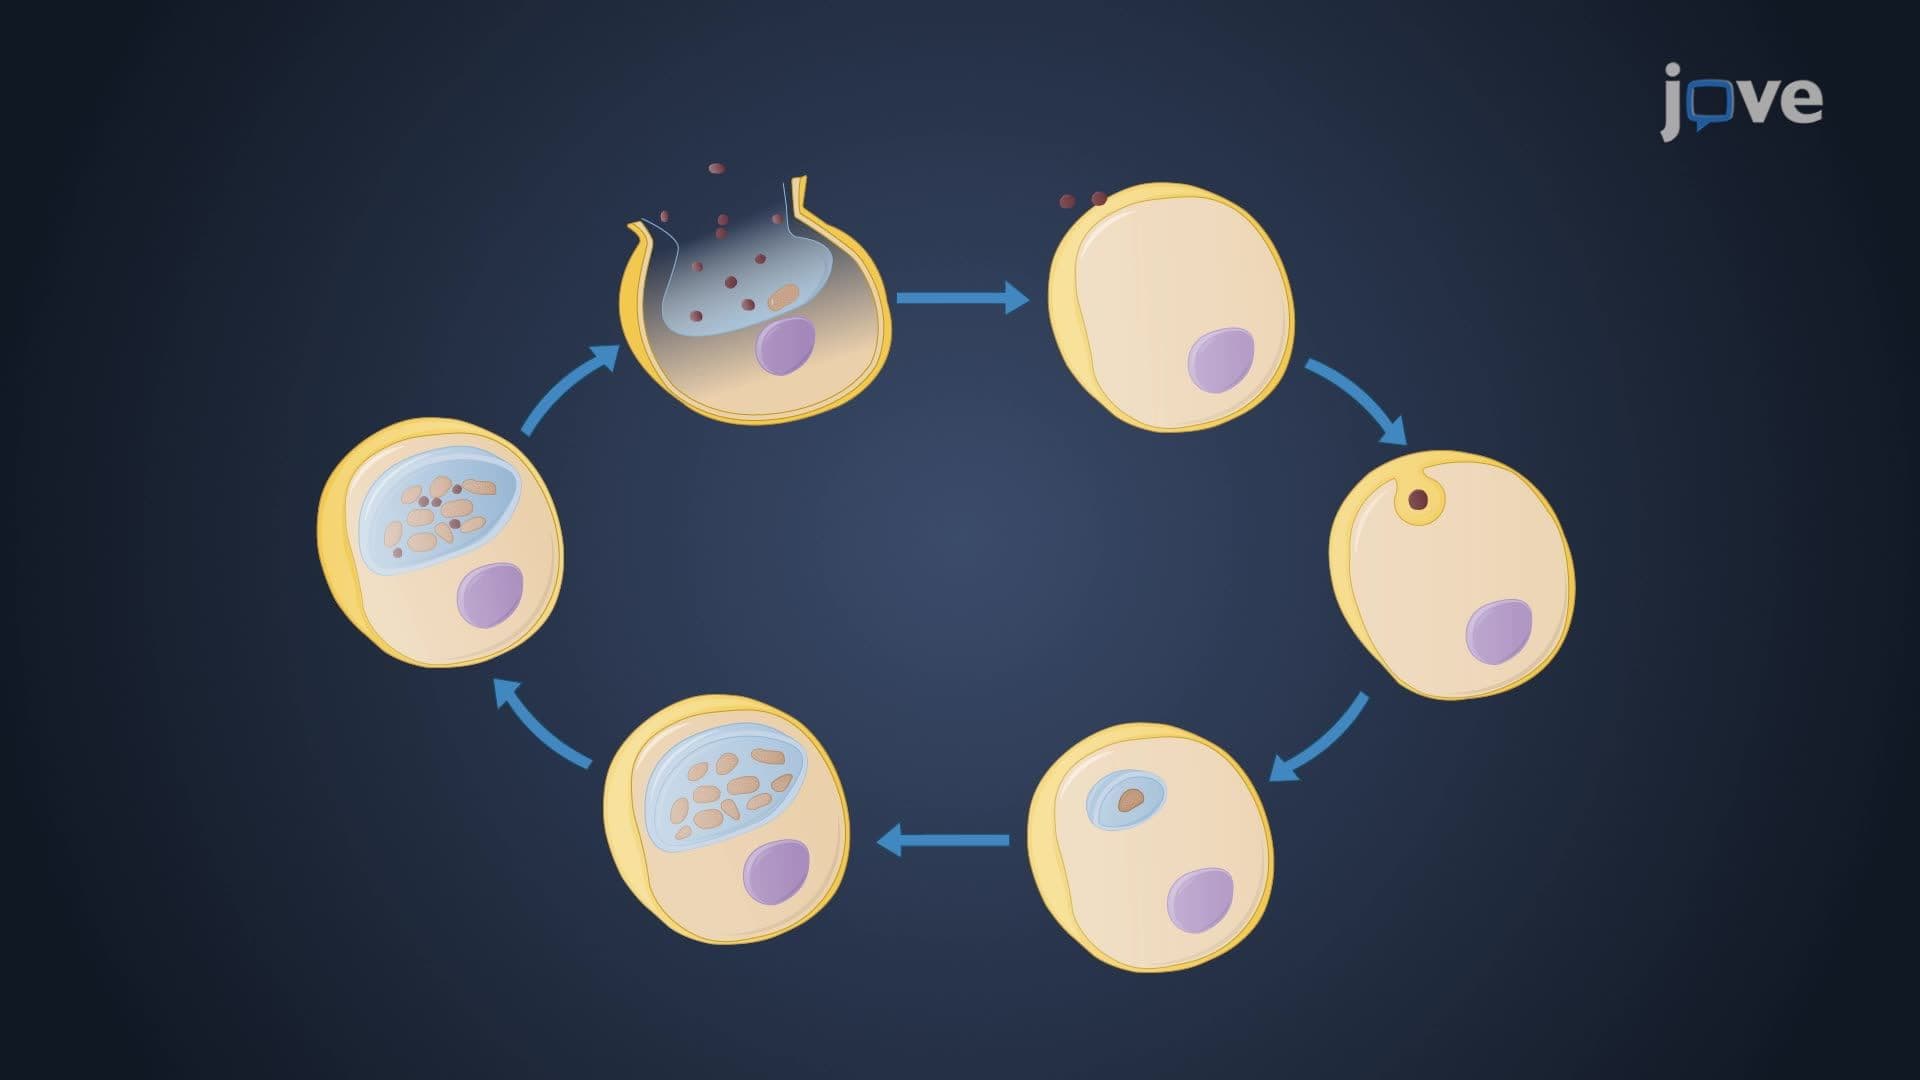
Bacterial Phylum Chlamydiae
 01:14
Atypical Pneumonia
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia I: Introduction
 01:19
Encephalitis l: Introduction
 01:22
Bacterial Meningitis I: Introduction