Related Experiment Video
Updated: Jul 11, 2026
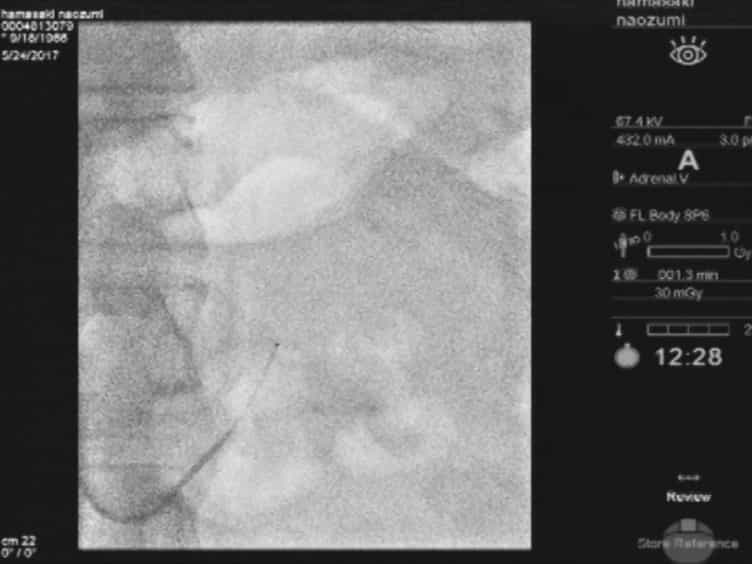
A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Adrenal causes of hypertension: pheochromocytoma and primary aldosteronism
1Mayo Medical School, Mayo Clinic, Rochester, MN 55905, USA. young.william@mayo.edu

Abstract:
The clinical presentations of the patient with pheochromocytoma -- a rare endocrine neoplasm -- include adrenal incidentaloma, hypertensive paroxysms, sustained apparent polygenic hypertension, hypertension in pregnancy, and hypertensive crisis induced by anesthesia. Although when undiagnosed a pheochromocytoma can be lethal, it can usually be cured with surgery. Biochemical documentation with measurements of fractionated metanephrines and catecholamines should precede imaging studies. Abdomen and pelvis computed imaging is usually the first imaging test. Careful preoperative pharmacologic preparation is important for a successful surgical outcome. Adrenal pheochromocytomas can usually be removed laparoscopically, whereas, catecholamine-secreting paragangliomas typically require an open approach. All first degree relatives of pheochromocytoma patients should have biochemical testing. In addition, molecular genetic testing for germline mutations should be considered in most patients with adrenal pheochromocytoma and in all patients with paraganglioma. Primary aldosteronism is a relatively common form of secondary hypertension -- affecting 5 to 10% of all patients with hypertension. A plasma aldosterone concentration (PAC) to plasma renin activity (PRA) ratio should be obtained in patients with hypertension and hypokalemia, resistant hypertension, adrenal incidentaloma and hypertension, onset of hypertension at a young age (e.g., < 20 years of age), severe hypertension (e.g., > or =160 mm Hg systolic or > or =100 mm Hg diastolic), or whenever the clinician is considering other forms of secondary hypertension. The PAC/PRA ratio is a case finding test and a positive result should be confirmed with aldosterone suppression testing with either oral or intravenous sodium loading. The treatment goals for patients with primary aldosteronism are to prevent the morbidity and mortality associated with hypertension, hypokalemia, and cardiovascular damage. Both the subtype of primary aldosteronism and patient preference should dictate the treatment approach.
Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:29
Hypertension II: Pathophysiology
 01:18
Hypertension and Regulation of Blood Pressure
 01:17
Hormonal Regulation of Blood Pressure
Epinephrine and Norepinephrine
The adrenal medulla releases epinephrine and norepinephrine, catecholamines that enhance and extend the sympathetic or "fight or flight" physiological response. These hormones escalate heart rate and the force of contraction while...
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:33
Hormonal Regulation