Related Experiment Video
Updated: Jul 11, 2026
An Approach to Point-Of-Care Ultrasound Evaluation of the Abdominal Aorta
Published on: September 8, 2023
Clinical and anatomical characteristics of subtle-discrete dissection of the ascending aorta
Fabio Chirillo1, Loris Salvador, Francesco Bacchion
1Division of Cardiology, Ca'Foncello Hospital, Treviso, Italy. fchirillo@ulss.tv.it

Insights
Subtle aortic dissection is often overlooked. Early identification via transesophageal echocardiography improves outcomes, reducing mortality and hospital stays for this rare condition.
Area of Science:
- Cardiovascular Medicine
- Diagnostic Imaging
- Surgical Outcomes
Background:
- Subtle or discrete aortic dissection (Class 3) is a neglected variant of aortic dissection.
- Ascending aortic involvement presents unique diagnostic and management challenges.
- Understanding its clinical profile is crucial for timely intervention.
Purpose of the Study:
- To define the clinical manifestations of subtle ascending aortic dissection.
- To identify diagnostic findings associated with discrete aortic dissection.
- To evaluate the outcomes of patients with subtle ascending aortic dissection.
Main Methods:
- Retrospective review of 109 patients with ascending aortic dissection (1995-2005).
- Analysis of clinical records, preoperative studies, and outcomes.
- Focus on identifying discrete dissections and diagnostic modalities, particularly transesophageal echocardiography (TEE).
Main Results:
- Eight patients (7.3%) had discrete ascending aortic dissection.
- Traditional imaging (aortography, MRI, CT) failed to identify intimal tears; TEE revealed intimal discontinuity, intramural hematoma, and pericardial fluid.
- Patients undergoing emergency surgery based on TEE had 0% operative mortality, shorter hospital stays, and reduced blood transfusion needs compared to classic dissection.
Conclusions:
- High clinical suspicion and detailed TEE are vital for diagnosing subtle aortic dissection.
- Prompt surgical intervention guided by TEE leads to improved patient outcomes.
- Discrete aortic dissection, when identified early, is associated with significantly better results than classic forms.
Abstract:
Subtle or discrete (class 3 in the classification of the European Society of Cardiology) dissection is the most neglected variant of aortic dissection. This study was conducted to define the clinical manifestations, diagnostic findings, and outcomes of subtle or discrete dissection involving the ascending aorta. The clinical and surgical records, preoperative studies, and outcomes of 109 consecutive patients with ascending aortic dissection observed from 1995 to 2005 were reviewed. Eight patients (7.3%) had discrete dissection. Five patients presented with acute anterior chest pain, 2 with abdominal pain, and 4 with syncope. The mean diameter of the ascending aorta was 44 +/- 8.8 mm. The intimal tears were located in all patients on the posterior aspect of the ascending aorta 1 to 40 mm above the left coronary ostium; its length varied from 2.8 to 12.3 mm. Preoperative aortography, magnetic resonance imaging, and computed tomography could not identify the discrete intimal tears. Transesophageal echocardiography provided unique diagnostic information on (1) subtle intimal discontinuity, (2) circumscribed intramural hematoma, and (3) discrete pericardial fluid around the dissected aorta. Six patients underwent emergency surgery on the basis of echocardiographic findings, and they were all alive at follow-up. Compared with patients with classic aortic dissection, those with discrete dissection had lower operative mortality (0% vs 26%, p = 0.11), shorter hospital stay (7.2 +/- 2.8 vs 21 +/- 19 days, p = 0.01), and less frequent need for blood transfusions (0% vs 39%, p = 0.02). In conclusion, elevated clinical suspicion and detailed transesophageal echocardiographic examination are important for the early identification of discrete aortic dissection, leading to prompt surgery, shorter hospital stays, and better outcomes.
Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:30
Aneurysm I: Introduction
 01:14
The Aorta
The average diameter of the aorta is approximately 2-3 cm, but the size can vary depending on the section of the aorta and the individual's age, sex, and body size. The aorta is...
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...
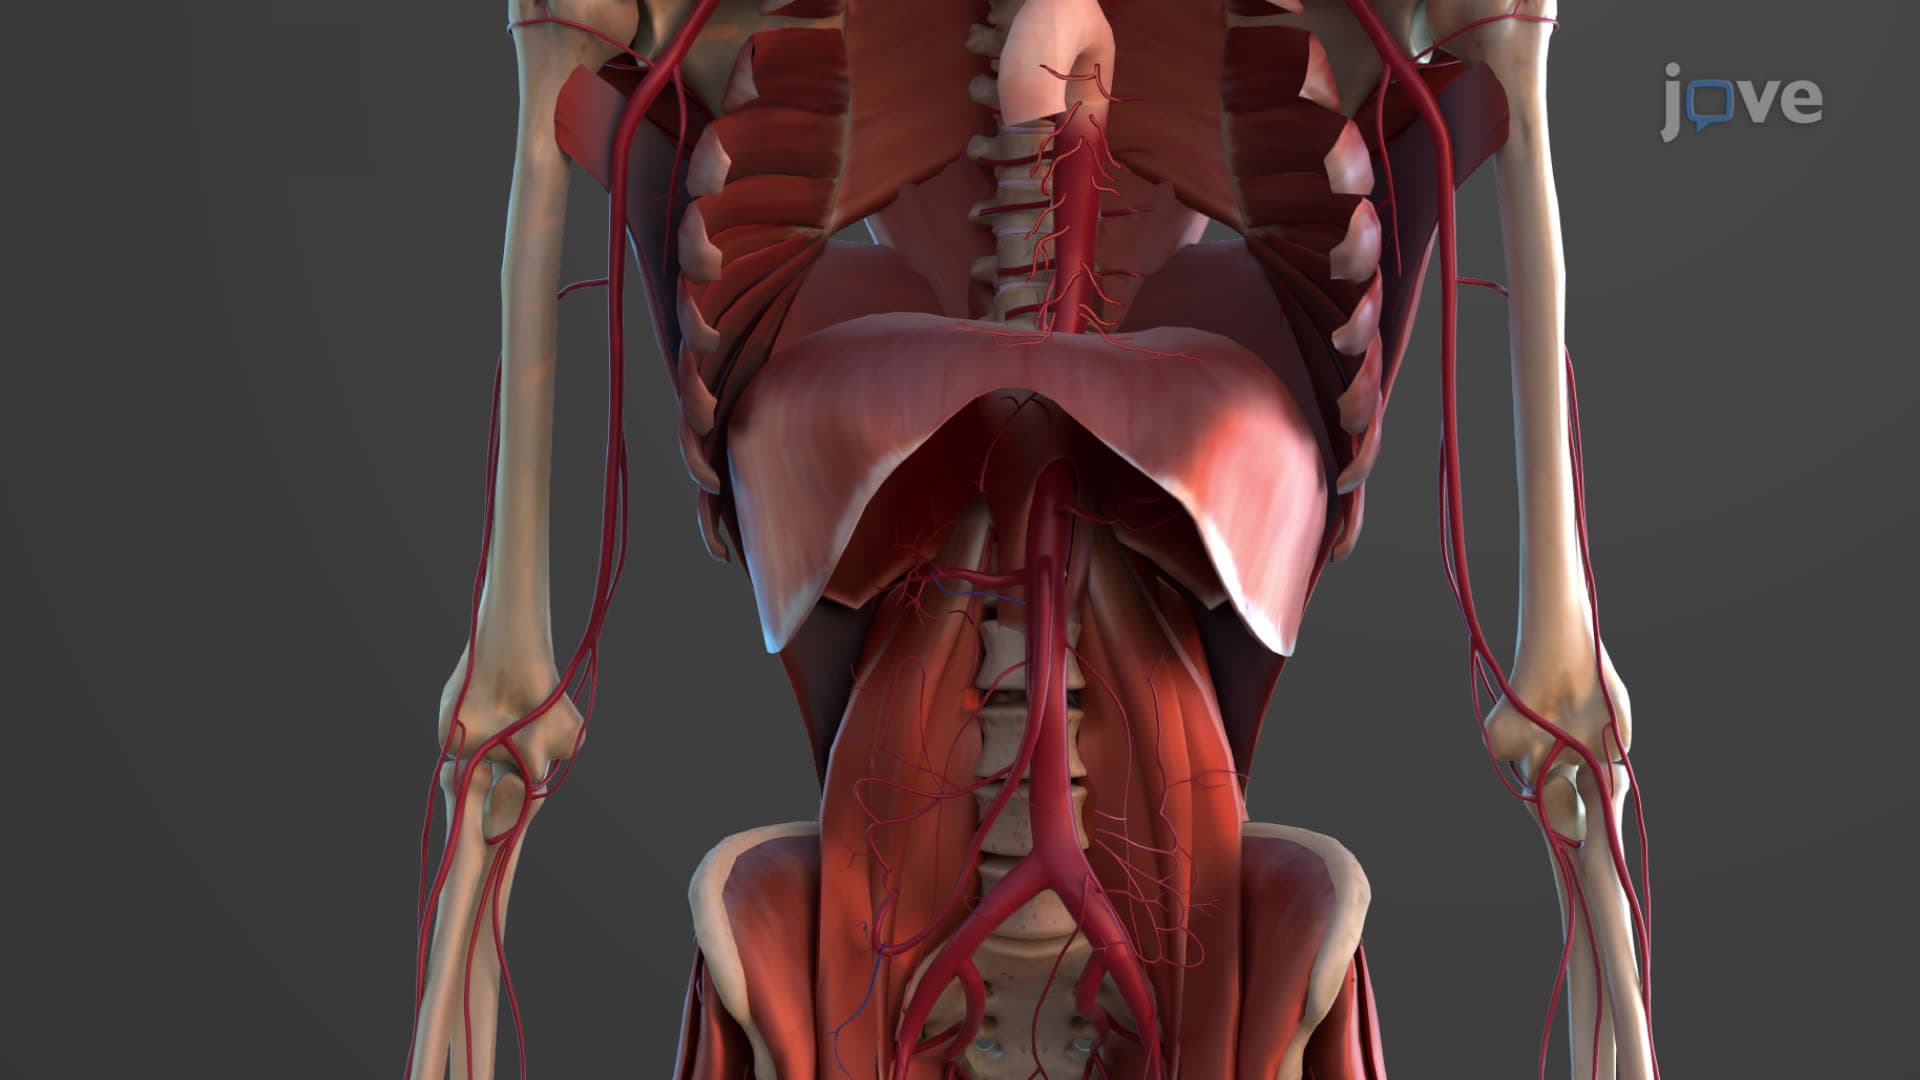 01:15
Thoracic Aorta