Related Experiment Video
Updated: Jul 11, 2026

Herbal Munziq Ameliorates Myocardial Ischemia-Reperfusion Injury by Inhibiting Inflammation
Published on: January 10, 2025
Comparison of the cardiac effects between quinazoline-based alpha1-adrenoceptor antagonists on occlusion-reperfusion
1Institute of Pharmacology, College of Medicine, National Taiwan University, Taipei, Taiwan ROC.

Abstract:
Quinazoline-based compounds such as prazosin and its congeners including doxazosin, bunazosin, and terazosin are widely used as antihypertensive agents. However, there were many clinical observations showing that using these agents may result in higher risk of cardiovascular accidents in recent years. In this study, we compared the effects of four alpha-adrenoceptor antagonists: prazosin, doxazosin, bunazosin, and terazosin on occlusion-reperfusion injury. Langendorff-perfused rat hearts were pretreated with these four antagonists, and then the left main coronary artery was occluded. After 30 min occlusion, the hearts were reperfused for 2 h and the infarct sizes were measured. Two of the compounds studied, prazosin and doxazosin, apparently increased infarct size, CK-MB, and LDH activities after 2 h reperfusion. In contrast, bunazosin decreased infarct size and those biochemical indicators of cellular damage compared to control hearts. Although infarct size after reperfusion was differently changed by these four alpha-adrenoceptor antagonists, TUNEL-positive nuclei and caspase-3 protein expressions of all the groups were not significantly different. We supposed that the different effects of these four agents on infarct size came from the difference in necrosis rather than apoptosis.
More Related Videos
 09:47
A Rat Model of Ventricular Fibrillation and Resuscitation by Conventional Closed-chest Technique
Published on: April 26, 2015
 05:41
Left Anterior Descending Coronary Artery Ligation for Ischemia-Reperfusion Research: Model Improvement via Technical Modifications and Quality Control
Published on: December 16, 2022
Related Concept Videos
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:17
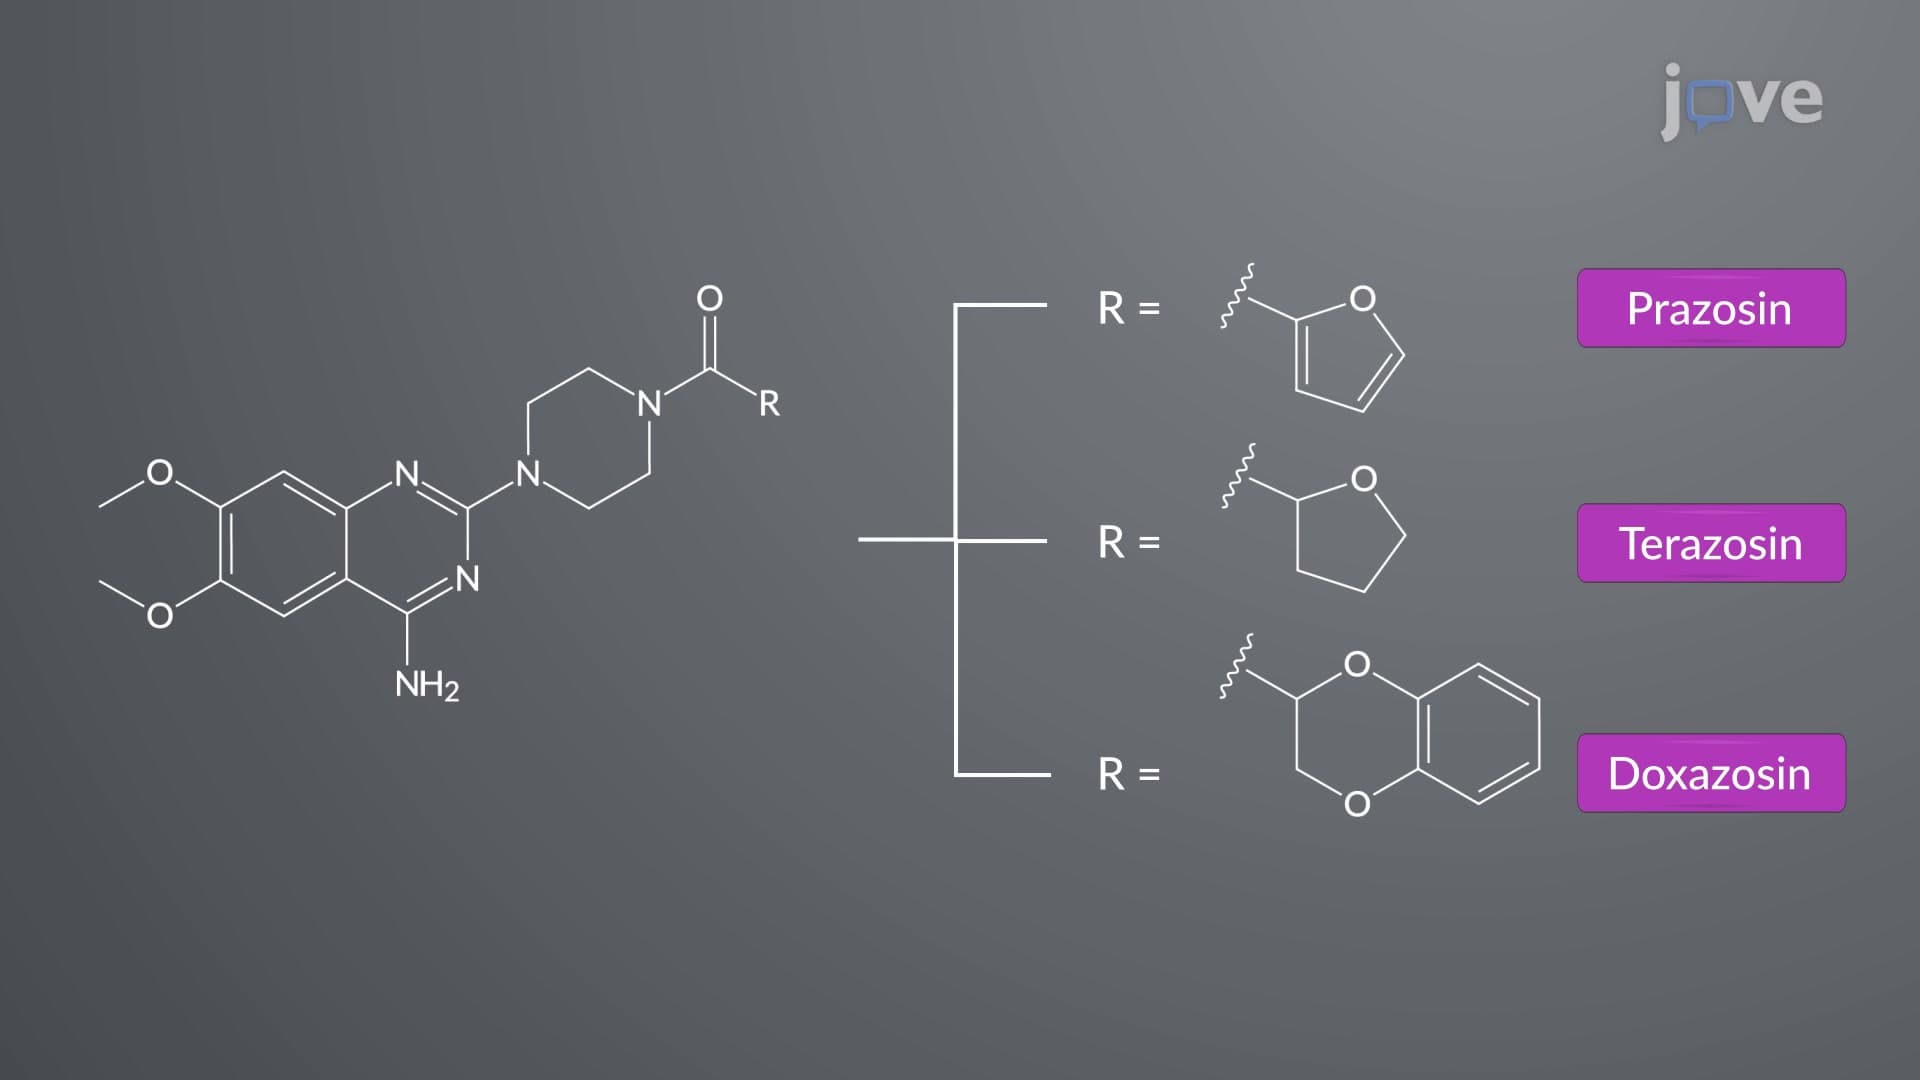
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers