Related Experiment Video
Updated: Jul 10, 2026

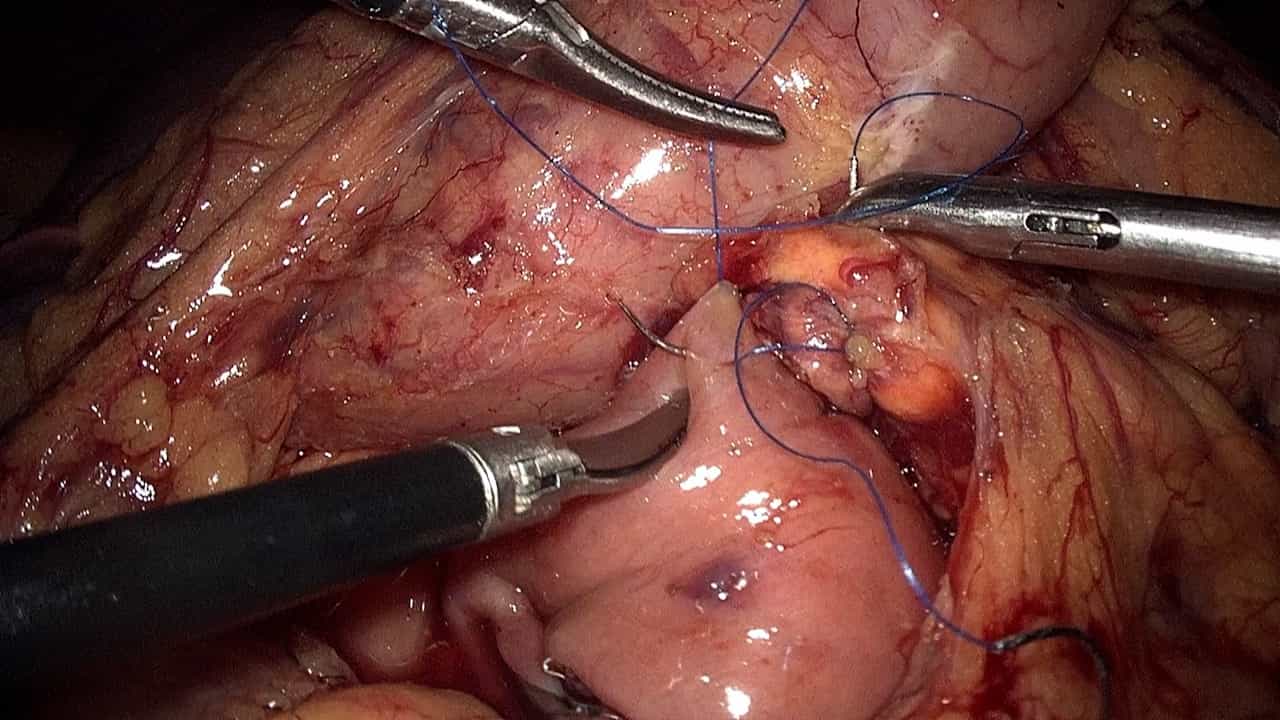
Robotic Enucleation of an Intra-Pancreatic Insulinoma in the Pancreatic Head
Published on: January 3, 2020
The laparoscopic approach toward hyperinsulinism in children
Klaas N M A Bax1, D C van der Zee
1Sophia Children's Hospital, Erasmus Medical Centre, Rotterdam, The Netherlands. n.bax@erasmusmc.nl

Insights
Surgery for hyperinsulinemic hypoglycemia (HH) in children is rare but necessary for therapy-resistant cases. Laparoscopic surgery, including pancreatectomy and lesion enucleation, is effective for managing HH, with a need to consider malignancy.
Area of Science:
- Pediatric Surgery
- Endocrinology
- Genetics
Background:
- Hyperinsulinemic hypoglycemia (HH) in children requiring surgery is uncommon.
- Early HH can stem from focal or diffuse pancreatic pathology, with genetic causes identified in some cases.
- Therapy-resistant forms necessitate early surgical intervention.
Purpose of the Study:
- To review surgical management strategies for pediatric hyperinsulinemic hypoglycemia.
- To discuss diagnostic challenges and therapeutic approaches for focal and diffuse HH.
- To highlight the role of laparoscopic surgery in managing HH.
Main Methods:
- Review of surgical techniques for hyperinsulinemic hypoglycemia.
- Discussion of diagnostic modalities including 18F-DOPA PET-CT and laparoscopic exploration.
- Analysis of surgical outcomes for pancreatectomy and lesion enucleation.
Main Results:
- Preoperative differentiation between focal and diffuse HH is challenging.
- 18F-DOPA PET-CT and laparoscopic exploration show promise for diagnosis.
- Laparoscopic spleen-saving pancreatectomy and enucleation are effective surgical treatments.
- Suspicion of malignancy should always be maintained.
Conclusions:
- Laparoscopic surgery is the preferred approach for older children with HH.
- Surgical strategies vary based on whether HH is associated with MEN-1 syndrome.
- Enucleation of insulin-producing lesions and pancreatectomy are key surgical interventions for HH.
Abstract:
Hyperinsulinemic hypoglycemia (HH) in children requiring surgery is rare. Early HH can be the result of focal or diffuse pancreatic pathology. A number of genetic abnormalities in early HH have been identified, but in the majority of patients no abnormality is found. The sporadic focal and diffuse forms as well the autosomal recessive form are particularly therapy-resistant and demand for early surgery. Preoperative discrimination between focal and diffuse disease in early HH is difficult. 18 F DOPA PET in combination with CT is promising as is laparoscopic exploration of the pancreas. Frozen section biopsy analysis has not been uniformly beneficial. If macroscopically no focal lesion is found, limited laparoscopic distal pancreatectomy provides tissue for definitive pathologic examination. Subsequent near total laparoscopic spleen-saving pancreatectomy surgery is not particularly difficult. Later HH may occur in the context of the MEN-1 syndrome and is then multifocal in nature. In MEN-1 patients, a distal spleen-saving pancreatectomy with enucleation of lesions in the head seems justified. Insulin-producing lesions in non-MEN-1 patients should be enucleated. There should always be a suspicion of malignancy. Also, in older children, surgery for hyperinsulinism should be performed laparoscopically.