Related Experiment Video
Updated: Jul 10, 2026


Methods for Quantitative Detection of Antibody-induced Complement Activation on Red Blood Cells
Published on: January 29, 2014
Hypocomplementemia in systemic sclerosis--clinical and serological correlations
Marie Hudson1, Jennifer G Walker, Marvin Fritzler
1SMBD-Jewish General Hospital and McGill University, 3755 Cote Sainte-Catherine Road, Montreal, Quebec, Canada. marie.hudson@mcgill.ca

Insights
Low complement levels in systemic sclerosis (SSc) patients may signal overlap disease, specifically inflammatory myositis and vasculitis. This finding helps identify a distinct SSc subgroup.
Area of Science:
- Rheumatology
- Immunology
- Systemic Sclerosis Research
Background:
- Hypocomplementemia, or low complement levels, is observed in systemic sclerosis (SSc) but not typically linked to its pathogenesis.
- The association of hypocomplementemia with SSc suggests a potential role in disease subsets or related conditions.
Purpose of the Study:
- To investigate whether hypocomplementemia in SSc patients is associated with an increased prevalence of overlap disease features.
- To compare the rates of concomitant rheumatic conditions and autoantibody profiles between SSc patients with normal and low complement levels.
Main Methods:
- Analysis of 321 patients from the Canadian Scleroderma Research Group Registry, categorized by normal (C3 and C4) or hypocomplementemia (low C3 or C4).
- Overlap disease was defined by physician reports of other rheumatic conditions.
- Comparison of disease frequencies and autoantibody profiles between the two complement groups.
Main Results:
- Of 321 SSc patients, 14% exhibited hypocomplementemia.
- Patients with hypocomplementemia showed significantly higher rates of physician-reported inflammatory myositis (27% vs. 12%) and vasculitis (11% vs. 2%) compared to those with normal complement levels.
- A trend towards increased antichromatin antibodies was observed in the hypocomplementemia group (18% vs. 9%).
Conclusions:
- Hypocomplementemia may serve as a clinical marker for identifying a specific subgroup of systemic sclerosis patients.
- This subgroup is characterized by a higher likelihood of having overlap disease, including inflammatory myositis and vasculitis.
Objective:
Although complement fixation is not commonly thought to be part of the pathogenesis of systemic sclerosis (SSc), hypocomplementemia has been associated with SSc. We hypothesized that hypocomplementemia in SSc might indicate the presence of overlap disease. We investigated if SSc patients with hypocomplementemia had more features of overlap disease than those with normal complement levels.
Methods:
Study subjects consisted of those enrolled in the Canadian Scleroderma Research Group Registry. Patients were divided into 2 groups: those with normal complement levels (normal C3 and C4) and those with hypocomplementemia (low C3 or C4). Evidence of overlap disease was defined as physician reports of other specific rheumatic conditions. Autoantibodies were assayed. Differences in rates of concomitant diseases and in antibody profiles were compared between groups.
Results:
Our study included 321 patients (88% women, mean age 56 +/- 13 yrs, mean disease duration 11 +/- 9 yrs). Of these, 276 (86%) had normal complements and 45 (14%) had hypocomplementemia. Patients with hypocomplementemia were significantly more likely to have physician-reported inflammatory myositis (27% vs 12%; p < 0.008) and vasculitis (11% vs 2%; p < 0.011) than those with normal complement. There was also a trend toward more antichromatin antibodies (18% vs 9%; p = 0.051) in patients with hypocomplementemia compared to normals.
Conclusion:
Hypocomplementemia may identify a particular subgroup of SSc patients who have overlap disease.

Related Concept Videos
 01:19
Hypersensitivity Reactions: Immune-Complex Reactions
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:27
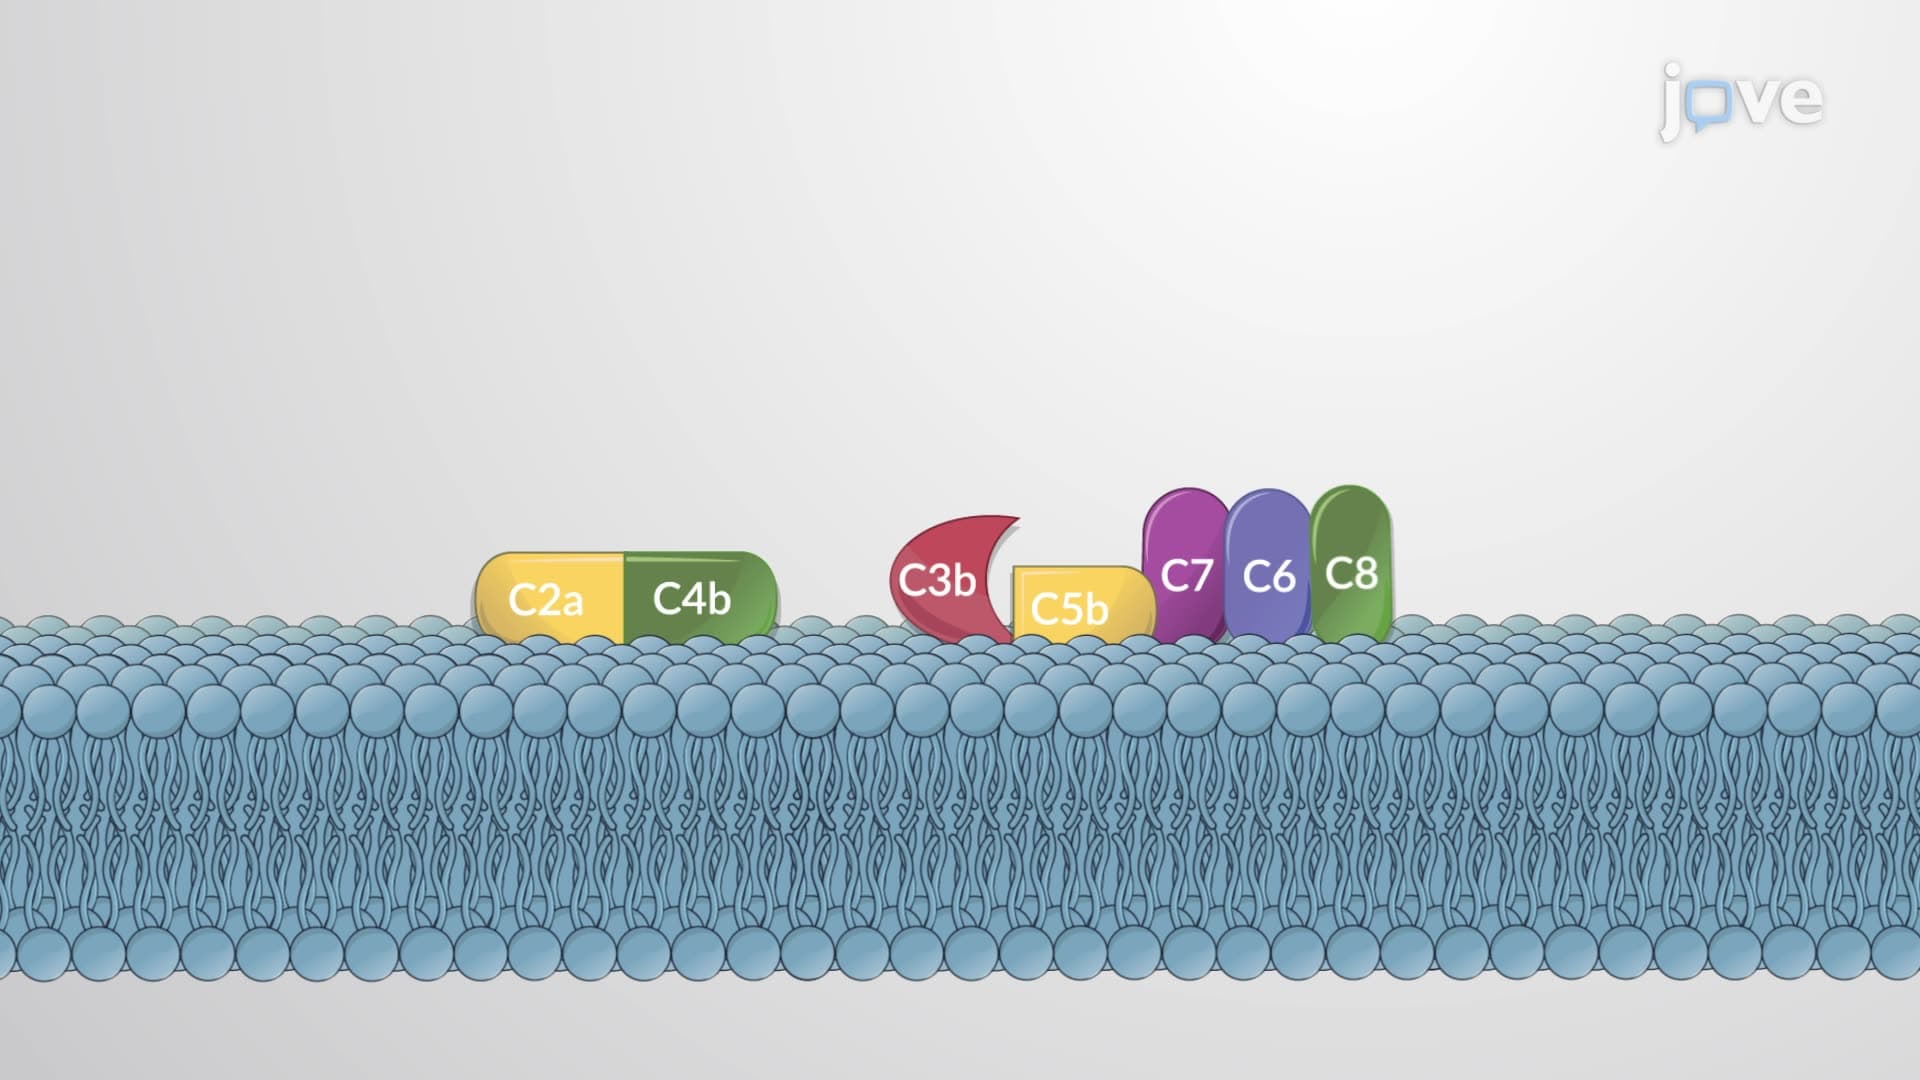
Complement System