Related Experiment Video
Updated: Jul 10, 2026
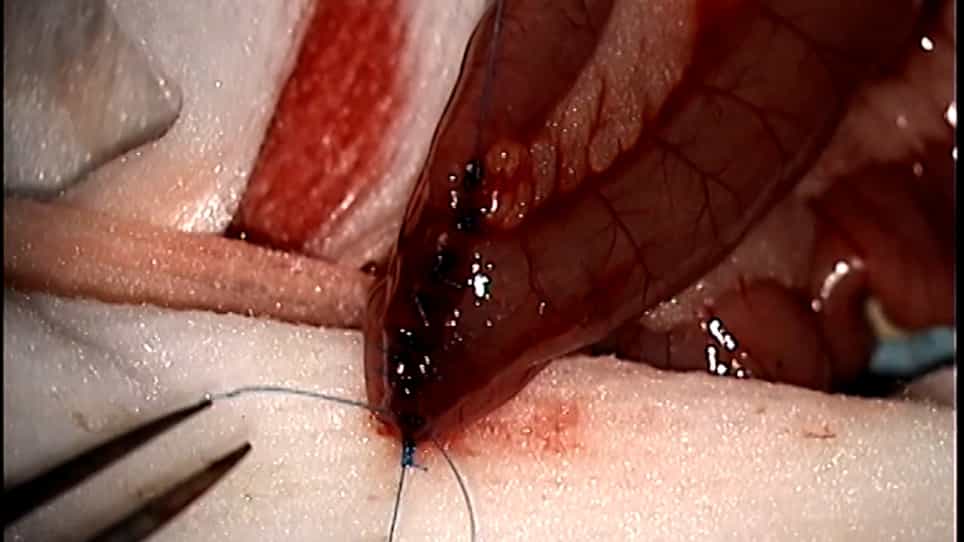
A Protocol for Roux-en-Y Gastric Bypass in Rats using Linear Staplers
Published on: August 21, 2021
Small-bowel obstruction after laparoscopic Roux-en-Y gastric bypass: etiology, diagnosis, and management
Syed Husain1, Ahmed R Ahmed, Joseph Johnson
1Department of Bariatric Surgery, University of Rochester, Highland Hospital, 1000 South Ave, Rochester, NY 14620, USA.

Objective:
To summarize our experience with small-bowel obstructions after laparoscopic Roux-en-Y gastric bypass.
Design:
Retrospective record review.
Setting:
University-affiliated hospital.
Patients:
One hundred five consecutive patients undergoing surgery for intestinal obstruction after laparoscopic Roux-en-Y gastric bypass between May 24, 2001, and December 1, 2006.
Main Outcome Measures:
Common presenting symptoms, causes, yield of radiological studies, and types of surgical procedures performed for post-gastric bypass bowel obstruction.
Results:
A total of 2325 laparoscopic Roux-en-Y gastric bypass procedures were performed during the study period. A total of 105 patients underwent 111 procedures. Bowel obstruction was confirmed in 102 patients, yielding an overall incidence of 4.4%. The most common presenting symptom was abdominal pain (82.0%), followed by nausea (48.6%) and vomiting (46.8%). Thirty-one patients (27.9%) presented with all of the 3 mentioned symptoms. The mean time to presentation was 313 days after bypass (range, 3-1215 days). Among the studies, results in 48.0% of computed tomographic scans, 55.4% of upper gastrointestinal studies, and 34.8% of plain abdominal radiography studies were positive for intestinal obstruction. In 15 patients (13.5%), all of the radiological study results were negative. The most common causes were internal hernias (53.9%), Roux compression due to mesocolon scarring (20.5%), and adhesions (13.7%). Laparoscopic explorations were carried out in 92 cases (82.9%). The incidences of bowel obstructions were 4.8% with retrocolic Roux placement and 1.8% with antecolic Roux placement.
Conclusions:
Altered gastrointestinal tract anatomy results in vague symptoms and a poor yield with imaging studies. A sound knowledge of altered anatomy is the key to correct interpretation of imaging studies and prompt diagnosis.

Related Concept Videos
 01:11
Pyloric Obstruction
 01:07
Intestinal Obstruction II: Pathophysiology
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease