Related Experiment Video
Updated: Jul 10, 2026
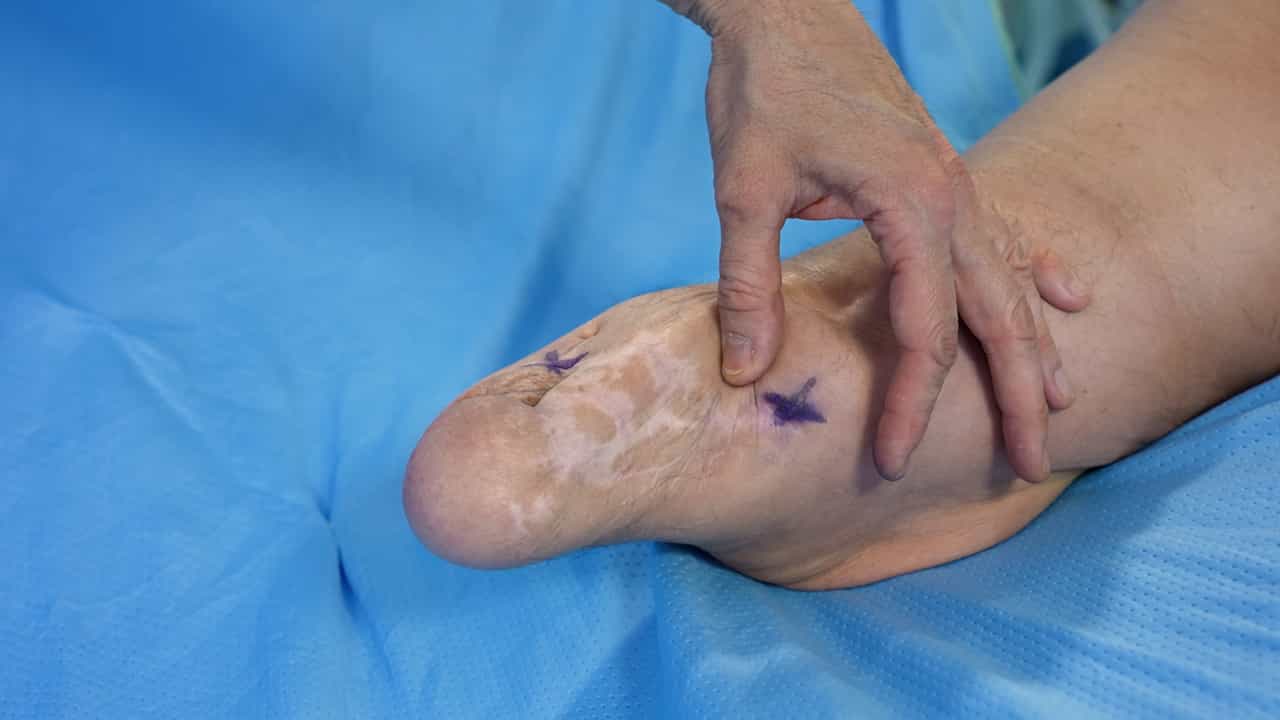

Targeted Muscle Reinnervation: Surgical Protocol for a Randomized Controlled Trial in Postamputation Pain
Published on: March 8, 2024
Zoster-associated pain: what is known, who is at risk and how can it be managed?
1University of Bristol, Bristol, UK. r.w.johnson@bris.ac.uk

Herpes zoster episodes commence with a prodromal period of about 4 days with symptoms including pain and malaise. This is followed by a rash lasting approximately 2-4 weeks, with possible subacute herpetic neuralgia for up to 3 months, followed, in some patients, by a period of post-herpetic neuralgia (PHN) lasting months or possibly years. Severe acute pain is more likely in older females and those with a prodrome or severe rash. Two separate mechanisms of PHN have been proposed: the first is that the excitability of primary afferent neurons is increased after nerve damage, causing irritable nociceptors and central sensitization, resulting in pain and allodynia; the second involves the degeneration of nociceptive neurons, which leads to deafferentation with central hyperactivity, causing pain but without allodynia. Both mechanisms may co-exist in an individual patient. Treatments for acute herpes zoster and PHN include established antivirals, alone or in combination with steroids, analgesics and neural blockade with local anaesthetics. Commonly used pain relief includes acetaminophen/paracetamol, non-steroidal anti-inflammatory drugs (NSAIDs), opioid analgesics, tricyclic antidepressants, gabapentin, pregabalin and topical analgesics. Effective and long-lasting pain relief in herpes zoster and PHN remains a largely unmet medical need.
Herpes zoster episodes commence with a prodromal period of about 4 days with symptoms including pain and malaise. This is followed by a rash lasting approximately 2-4 weeks, with possible subacute herpetic neuralgia for up to 3 months, followed, in some patients, by a period of post-herpetic neuralgia (PHN) lasting months or possibly years. Severe acute pain is more likely in older females and those with a prodrome or severe rash. Two separate mechanisms of PHN have been proposed: the first is that the excitability of primary afferent neurons is increased after nerve damage, causing irritable nociceptors and central sensitization, resulting in pain and allodynia; the second involves the degeneration of nociceptive neurons, which leads to deafferentation with central hyperactivity, causing pain but without allodynia. Both mechanisms may co-exist in an individual patient. Treatments for acute herpes zoster and PHN include established antivirals, alone or in combination with steroids, analgesics and neural blockade with local anaesthetics. Commonly used pain relief includes acetaminophen/paracetamol, non-steroidal anti-inflammatory drugs (NSAIDs), opioid analgesics, tricyclic antidepressants, gabapentin, pregabalin and topical analgesics. Effective and long-lasting pain relief in herpes zoster and PHN remains a largely unmet medical need.

Related Concept Videos
 01:20
Chickenpox
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:25
Analgesia and Pain Management
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:23
Atherosclerosis IV: Nursing Management