Related Experiment Video
Updated: Jul 10, 2026
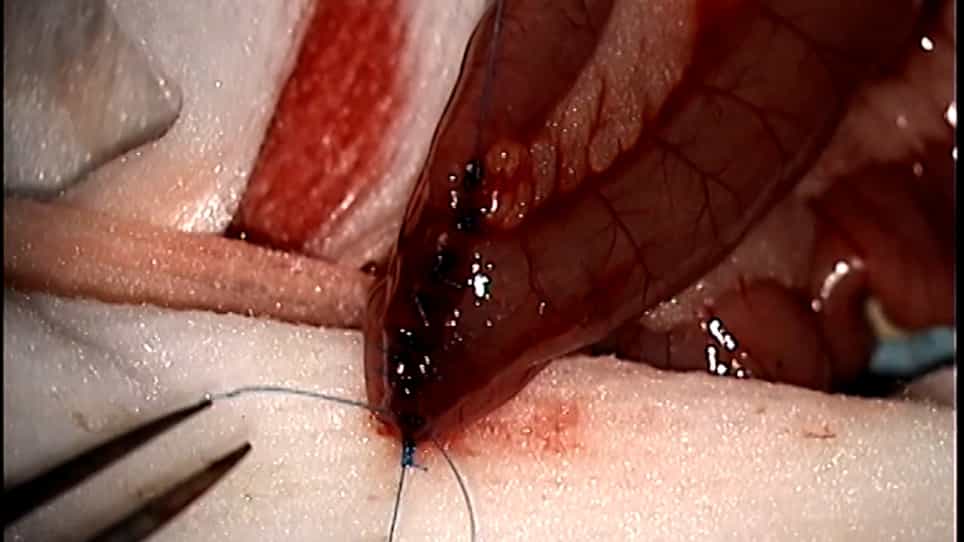

A Protocol for Roux-en-Y Gastric Bypass in Rats using Linear Staplers
Published on: August 21, 2021
Endoscopic management of early upper gastrointestinal hemorrhage following laparoscopic Roux-en-Y gastric bypass
Laith H Jamil1, Kevin R Krause, David L Chengelis
1Division of Gastroenterology/Hepatology, William Beaumont Hospital, Royal Oak, Michigan, USA.

Background And Aims:
Upper gastrointestinal hemorrhage (UGIH) is an infrequent complication (1-3.8%) following laparoscopic Roux-en-Y gastric bypass (LRYGB). The safety and efficacy of endoscopic management of immediate postoperative bleeding is unknown. We sought to determine how frequently UGIH complicates LRYGB and whether endoscopic management is successful in controlling hemorrhage.
Methods:
Retrospective chart review of all patients who developed UGIH following LRYGB from November 2001 to July 2005 at a large suburban teaching hospital.
Results:
Of 933 patients who underwent LRYGB, 30 (3.2%) developed postoperative UGIH. An endoscopic esophagogastroduodenoscopy (EGD) was performed in 27/30 patients (90%). All were found to have bleeding emanating from the gastrojejunostomy (GJ) staple line. Endoscopic intervention was performed in 24/30 (80%) with epinephrine injection and heater probe cautery being used most commonly. Endoscopic therapy was ultimately successful in controlling all hemorrhage, with 5 patients (17%) requiring a second EGD for rebleeding. No patient required surgery to control hemorrhage. One patient aspirated during the endoscopic procedure with subsequent anoxic encephalopathy and died 5 days postoperatively. Twenty-one patients (70%) developed UGIH in the intraoperative or immediate postoperative period (<4 h postoperative). The mean length of stay was significantly longer in these patients (2.84 vs 4.1, P= 0.001).
Conclusions:
(a) UGIH complicates LRYGB in a small but significant number of patients. (b) Bleeding usually occurs at the GJ site. (c) EGD is safe and effective in controlling hemorrhage with standard endoscopic techniques. (d) UGIH occurs most commonly in the immediate postoperative period and may be best managed in the operating room with the patient intubated to prevent aspiration.
More Related Videos
 04:05
Endoscopic Vacuum Therapy for the Treatment of Anastomotic Leakage after Total Gastrectomy with Esophagojejunostomy
Published on: August 22, 2025
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...