Related Experiment Videos
Acute upper gastrointestinal haemorrhage
1GI Unit, Western General Hospital, Edinburgh, UK. Kelvin.Palmer@luht.scot.nhs.uk

Abstract:
Acute gastrointestinal haemorrhage is a common medical emergency that has a hospital mortality of approximately 10%. Peptic ulcer bleeding, complicating non-steroidal anti-inflammatory drugs, aspirin or Helicobacter pylori infection is the most common cause of major bleeding. Gastro-oesophageal varices are less common but managing the underlying liver disease and the severity of bleeding may be demanding. The prognosis of patients presenting with acute bleeding is dictated by the presence of medical co-morbidities and by the severity of liver disease in patients with varices. Validated prognostic scoring systems, based upon the severity of bleeding, diagnosis, endoscopic findings and extent of co-morbidities, predict mortality and have clinical utility. The treatment of non-variceal bleeding is based upon cardiovascular resuscitation followed by endoscopic therapy in patients with active bleeding or major stigmata of recent haemorrhage. Proton pump inhibitor drugs reduce the risk of re-bleeding but have little effect on mortality. Emergency surgery is undertaken for uncontrolled bleeding or re-bleeding that cannot be controlled by further endoscopic therapy. Oesophageal varices are managed by fluid resuscitation, antibiotics and endoscopic band ligation. Vasoactive drugs may stop active bleeding but have no effect upon mortality. Management of the complications of the underlying liver disease and complete variceal ablation in a banding programme are essential. Gastric varices are treated by injection with tissue adhesives or transjugular intrahepatic porto-systemic shunt (TIPSS) insertion. Surgical intervention has little role in the management of varices and patients who do not respond to endoscopic therapies are best treated by TIPSS.
Related Concept Videos
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:27
Peptic Ulcer
 01:24
Esophageal Varices-I: Introduction
 01:24
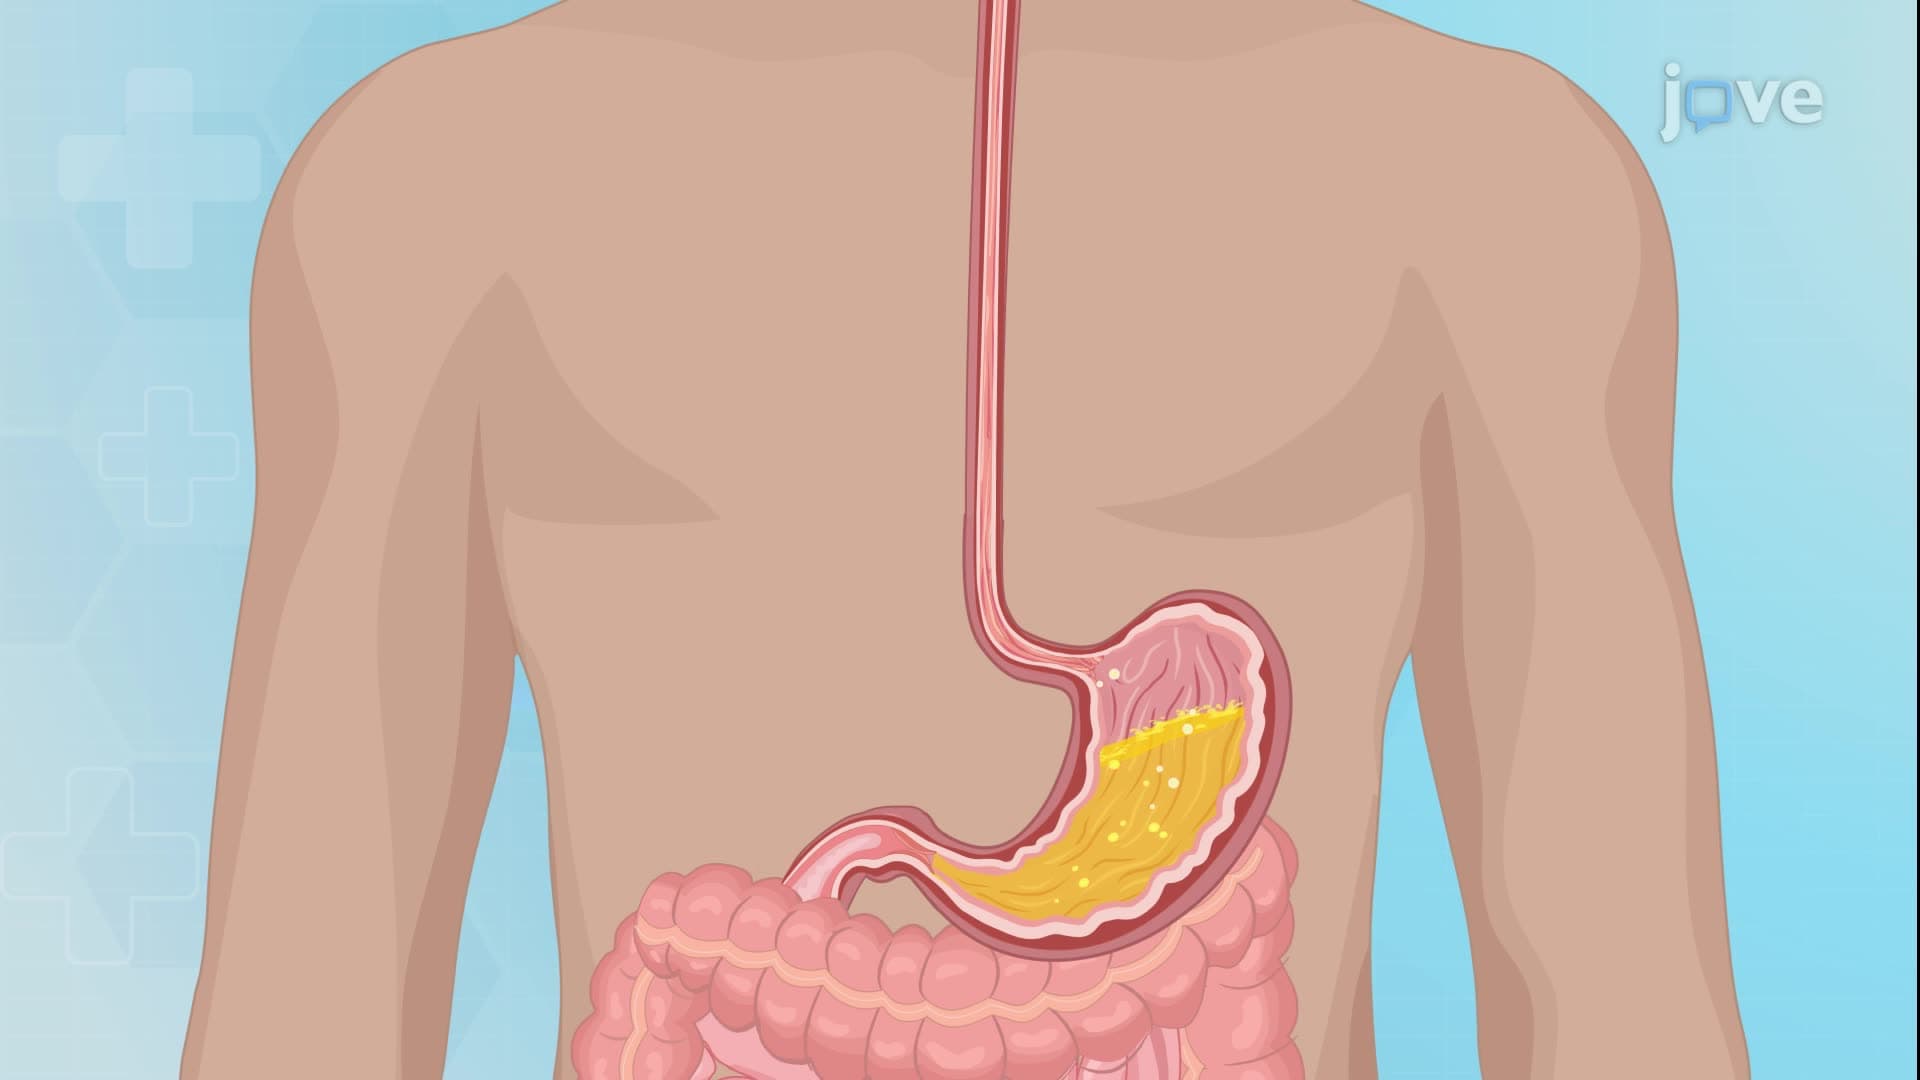
Upper GI Series: Barium Swallow
Purpose and Procedure
Patients undergoing this procedure ingest a liquid containing barium sulfate with a chalky...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications