Variability of the prevalence of undiagnosed airflow obstruction in smokers using different diagnostic criteria
Related Experiment Video
Updated: Jul 10, 2026
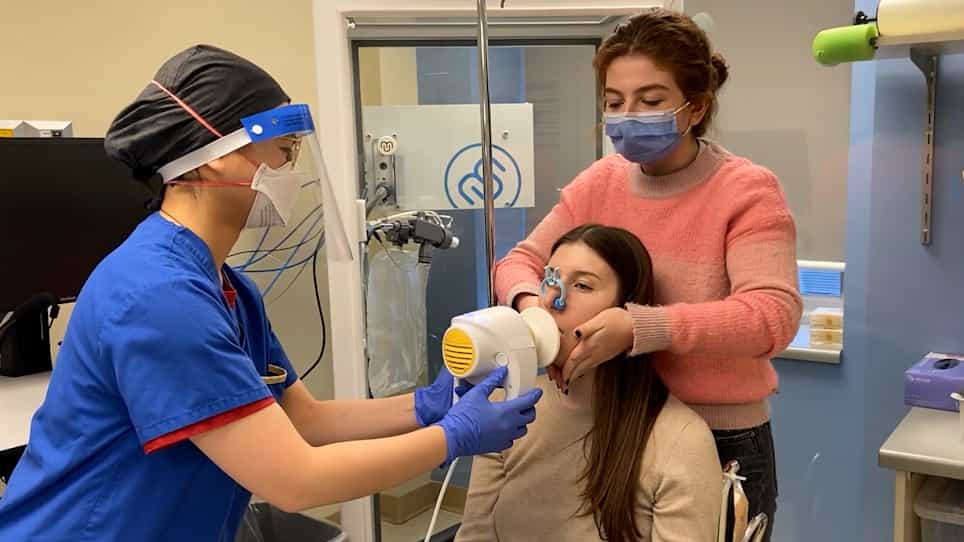
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Arthur Chun-Wing Lau1, Mary Sau-Man Ip, Christopher Kei-Wai Lai
1Department of Intensive Care, The University of Hong Kong, Queen Mary Hospital Pokfulam, Hong Kong SAR, China.

Purposes:
To estimate the prevalence of undiagnosed airflow obstruction (AFO) in Hong Kong smokers with no previous diagnosis of respiratory disease, and to assess its variability when applying different prediction equations and diagnostic criteria.
Methods:
A multicenter, population-based, cross-sectional prevalence study was performed in smokers aged 20 to 80 years. Three different criteria (fixed 70% [Global Initiative for Chronic Obstructive Lung Disease and British Thoracic Society], fixed 75%, and European Respiratory Society [ERS]) were applied to define a lower limit of normal (LLN) of the FEV(1)/FVC ratio to compare with the Hong Kong Chinese reference equation (criterion 1), which had used a distribution-free method to obtain the lower fifth percentile of FEV(1)/FVC ratio as the LLN.
Results:
In 525 male patients, using criterion 1 (local internal prediction equation) and defining AFO as FEV(1)/FVC less than LLN, the overall prevalence of AFO was 13.7%: 8.3% in age > or = 20 to 40 years, 14.0% in age > or = 40 to 60 years, and 17.8% in age > or = 60 to 80 years. When the local internal prediction equation was used as the comparison reference, the fixed-ratio methods tended to miss AFO in younger age groups and overdiagnose AFO in old age, while the ERS criteria, which uses an almost lower fifth percentile-equivalent method, showed less of such a trend but still only showed moderate agreement with criterion 1.
Conclusions:
Undiagnosed AFO was prevalent in Hong Kong smokers. Estimated prevalence rates were highly affected by the criteria used to define AFO. The predicted lower fifth percentile values calculated from a local reference equation as the LLN of FEV(1)/FVC ratio should be used for the diagnosis of AFO.
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...