Related Experiment Video
Updated: Jul 10, 2026

Rapid Generation of Amyloid from Native Proteins In vitro
Published on: December 5, 2013
Is beta2-microglobulin-related amyloidosis of hemodialysis patients a multifactorial disease? A new pathogenetic
G Cianciolo1, L Colí, G La Manna
1Nephrology Dialysis and Renal Transplantation Unit, S. Orsola University Hospital, Bologna, Italy.

Purpose:
Beta2-microglobulin amyloidosis (Abeta(2)M) is one of the main long-term complications of dialysis treatment. The incidence and the onset of Abeta(2)M has been related to membrane composition and/or dialysis technique, with non-homogeneous results. This study was carried out to detect: i) the incidence of bone cysts and CTS from Abeta(2)M; ii) the difference in Abeta(2)M onset between cellulosic and synthetic membranes; iii) other risk factors besides the membrane.
Methods:
480 HD patients were selected between 1986 to 2005 and grouped according to the 4 types of membranes used (cellulose, synthetically modified cellulose, synthetic low-flux, synthetic high-flux). The patients were analyzed before and after 1995, when the reverse osmosis treatment for dialysis water was started at our center, and the incidence of Abeta(2)M was compared between the two periods. Routine plain radiography, computer tomography (CT) and nuclear magnetic resonance imaging (MRI) as well as electromyography were used to investigate the clinical symptoms.
Results:
Bone cysts occurred in 29.2% of patients before 1995 vs. 12.2% after 1995 (p<0.0001). CTS occurred in 24% of patients before 1995 vs. 7.1% after 1995 (p<0.0001). Bone cysts and CTS occurred in older patients, who began dialysis at a late age, with high CRP, low albumin, low residual GFR, and low Hb. Cox regression analysis showed that the risk factor for bone cysts was high CRP (RR 1.3, p<0.01), while albumin (RR 0.14, p<0.0001) and residual GFR (RR 0.81, p<0.0001) were revealed to be protective factors. Cox analysis for CTS confirmed CRP as a risk factor (RR 1.2, p<0.01), and albumin (RR 0.59, p<0.0001) and residual GFR (RR 0.75, p<0.0001) as protective factors. The comparison obtained between membranes did not suggest any protective effect on Abeta(2)M.
Conclusions:
The findings that the inflammatory status as well as low albumin and the residual GFR of the uremic patient are predictive of Abeta(2)M lesions suggests that Abeta(2)M has a multifactorial origin rather than being solely a membrane- or technique-related side effect.
Insights
Beta2-microglobulin amyloidosis (Abeta(2)M) complications like bone cysts and carpal tunnel syndrome (CTS) decreased significantly after improved dialysis water treatment. Inflammatory status, low albumin, and low residual GFR are key risk factors for Abeta(2)M.
Area of Science:
- Nephrology
- Clinical Medicine
- Biomaterials Science
Background:
- Beta2-microglobulin amyloidosis (Abeta(2)M) is a serious long-term complication of hemodialysis.
- The etiology of Abeta(2)M, particularly its association with dialysis membranes and techniques, remains incompletely understood.
- Previous studies have yielded inconsistent results regarding the influence of membrane composition and dialysis techniques on Abeta(2)M incidence.
Purpose of the Study:
- To determine the incidence of bone cysts and carpal tunnel syndrome (CTS) associated with Abeta(2)M.
- To compare the onset of Abeta(2)M between patients using cellulosic and synthetic dialysis membranes.
- To identify risk factors for Abeta(2)M beyond membrane type and dialysis technique.
Main Methods:
- A cohort of 480 hemodialysis (HD) patients treated between 1986 and 2005 was analyzed.
- Patients were grouped by dialysis membrane type: cellulose, synthetically modified cellulose, synthetic low-flux, and synthetic high-flux.
- Data were compared between periods before and after the implementation of reverse osmosis (RO) for dialysis water treatment in 1995. Diagnostic tools included radiography, CT, MRI, and electromyography.
Main Results:
- Incidence of bone cysts decreased from 29.2% before 1995 to 12.2% after 1995 (p<0.0001).
- CTS incidence dropped from 24% before 1995 to 7.1% after 1995 (p<0.0001).
- High C-reactive protein (CRP), low albumin, and low residual glomerular filtration rate (GFR) were identified as significant risk factors for Abeta(2)M, while albumin and residual GFR demonstrated protective effects. Dialysis membrane type did not show a significant protective effect.
Conclusions:
- Abeta(2)M development is multifactorial, influenced by the patient's inflammatory status, nutritional status (albumin levels), and residual renal function.
- The findings suggest that Abeta(2)M is not solely a side effect of dialysis membrane or technique.
- Improving dialysis water quality and managing patient-specific factors like inflammation and nutritional status are crucial for mitigating Abeta(2)M.

Related Concept Videos
 03:03
Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
03:03Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
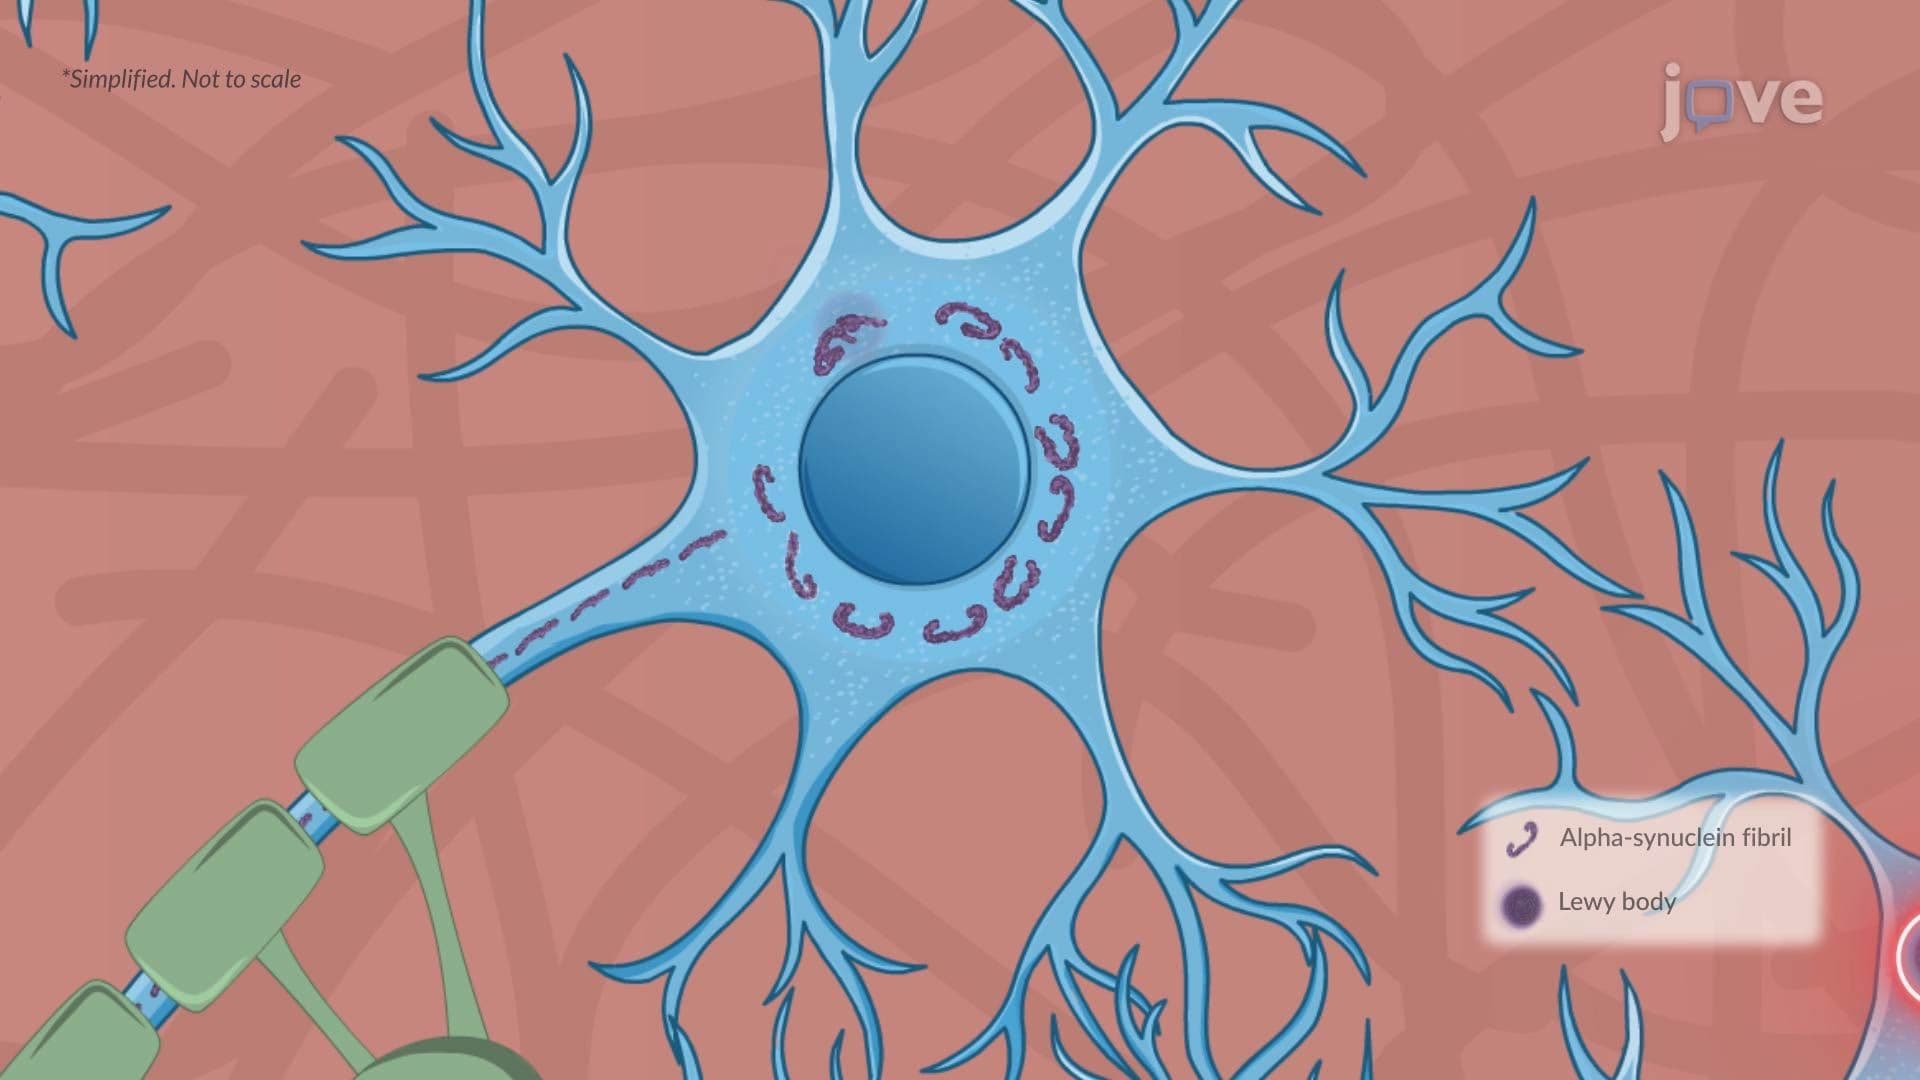 01:24
Parkinson Disease ll: Pathophysiology
 01:28
Diabetic Nephropathy
 01:24
Nephrotic Syndrome I : Introduction
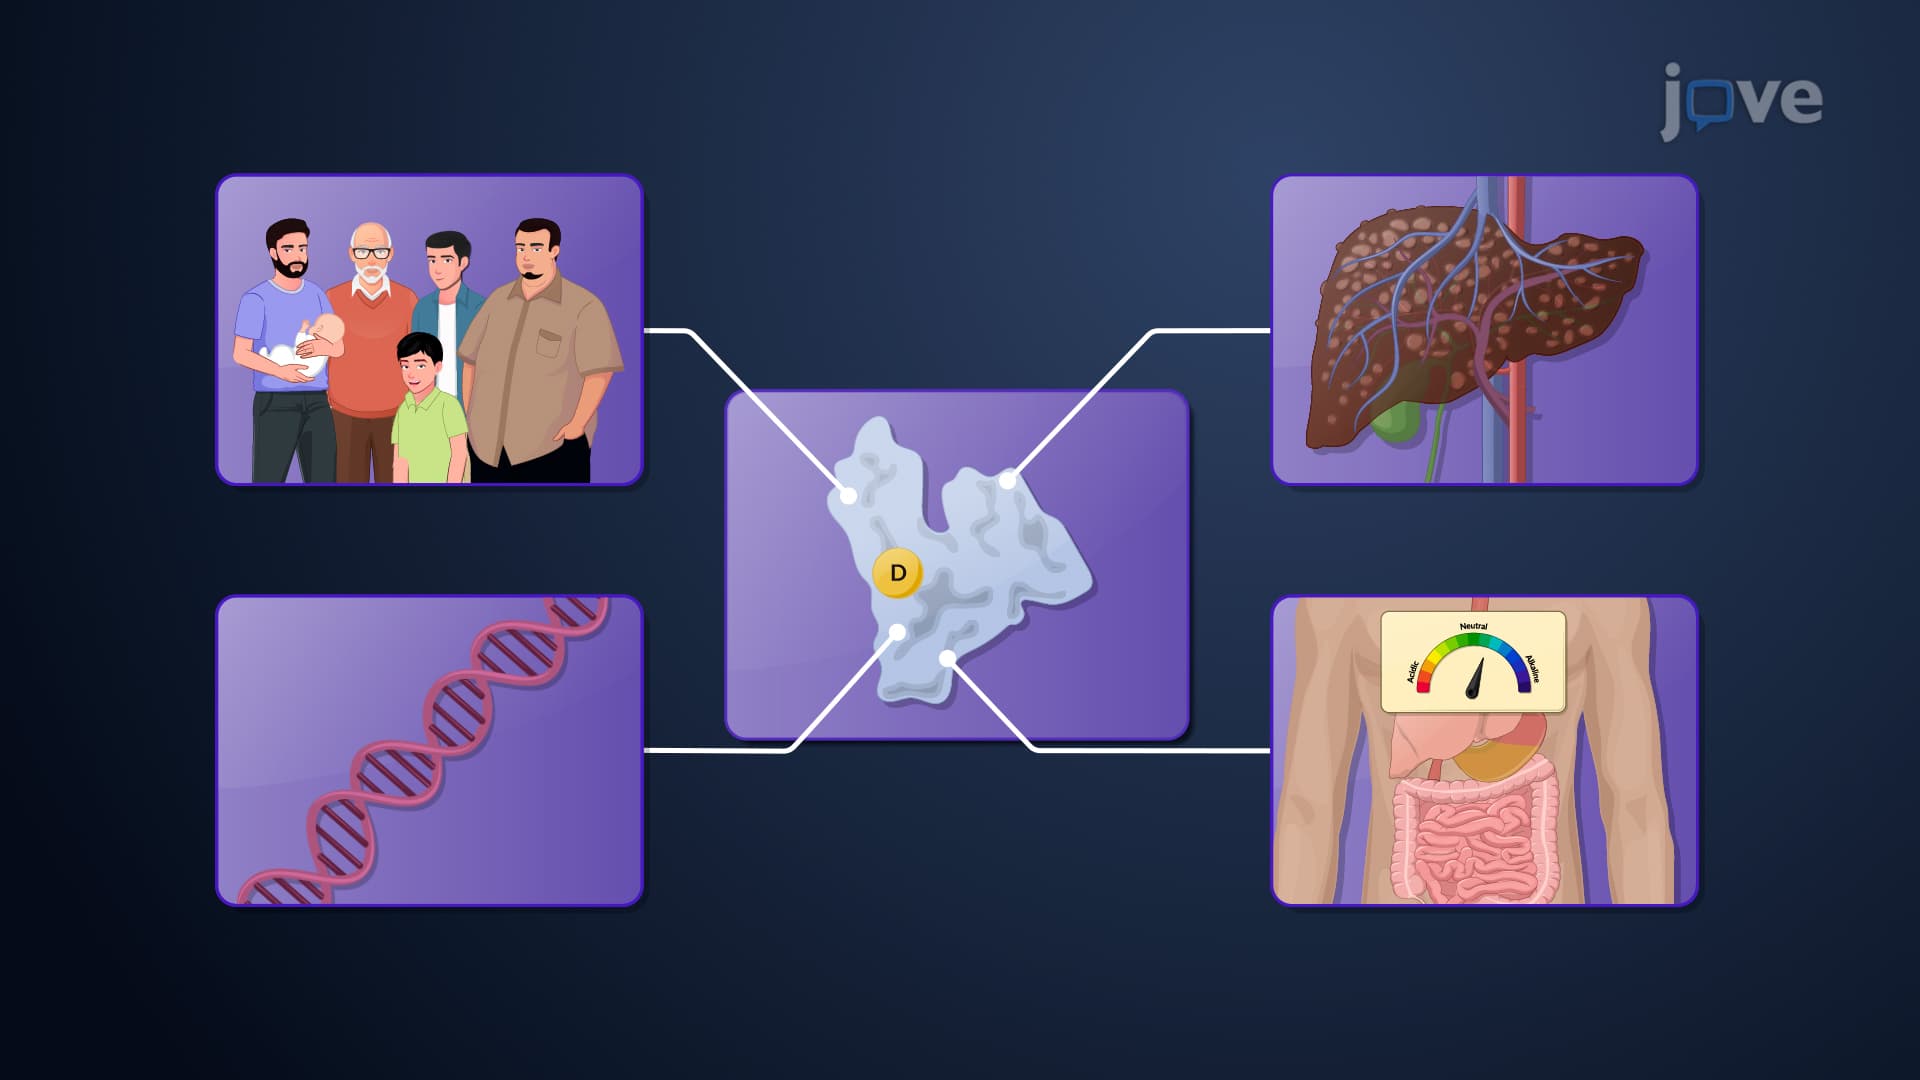 01:29
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...