Related Experiment Video
Updated: Jul 10, 2026
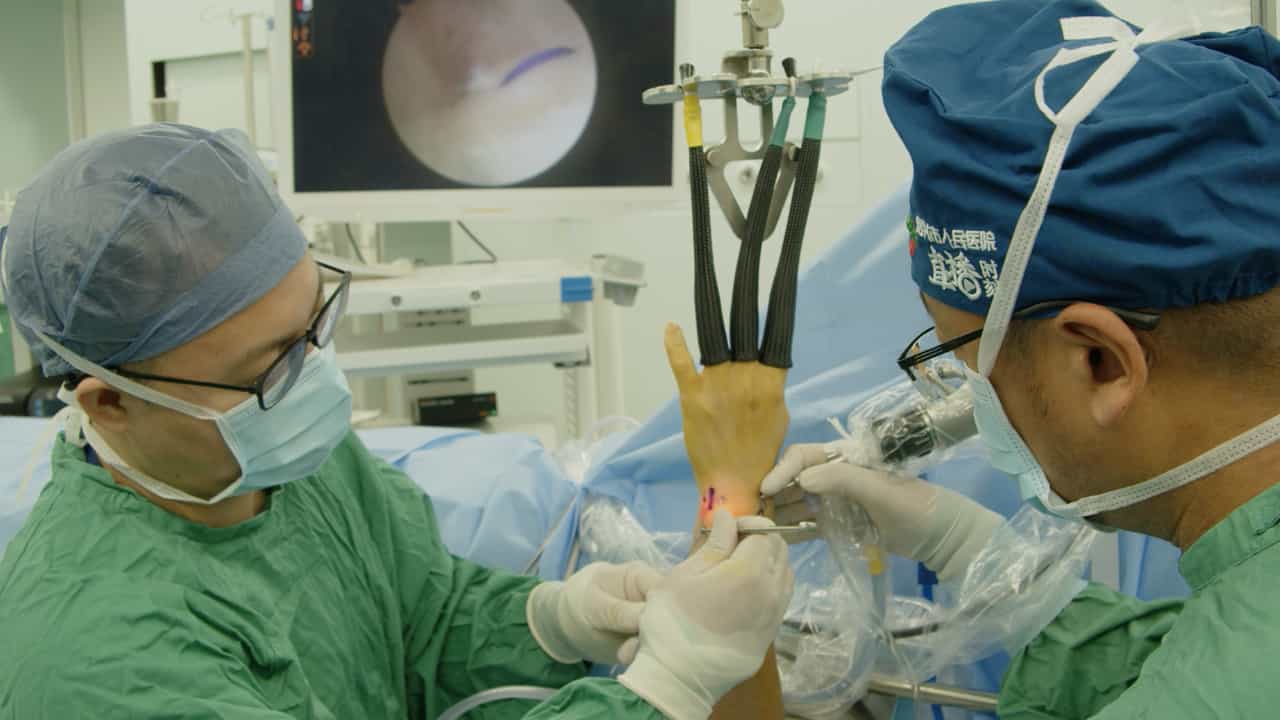

Novel Triple-Loop Technique for Suturing TFCC Injuries without Transosseous Tunnel
Published on: May 23, 2025
Double bundle revision of a malplaced single bundle vertical ACL reconstruction: ACL revision surgery using a two
1Department of Trauma, Hand and Reconstructive Surgery, University of Münster, Münster, Germany. thore.zantop@ukmuenster.de

Background:
Several factors influence the outcome after ACL reconstruction. One of the most important factors influencing the resulting knee kinematics and subjective instability is femoral tunnel placement. Revision can be necessary if the femoral tunnel is drilled transtibial in the roof of femoral notch (mismatch).
Hypothesis:
Double bundle reconstruction using two femoral tunnels and one tibial tunnel technique can be used in revision of a primary vertical ACL reconstruction.
Study Design:
Case series (level of evidence III).
Methods:
ACL revision was performed in five patients complaining instability after primary transtibial ACL reconstruction. Clinical examination, X-ray and CT analysis were performed to evaluate objective knee laxity, tunnel placement and widening. In all patients a technique using two femoral tunnels in a two medial portal technique and one tibial tunnel was used. Patients were reevaluated at a follow up of 24 months.
Results:
Preoperatively, pivot shift tests were 2+ in three and 1+ in the remaining two patients. Lachman test was found to be positive in all patients (4 patients, 2+ firm endpoint; 1 patient, 2+ soft endpoint). X-rays showed a femoral tunnel position at 11.30 (1 patient) and 12.00 o'clock (4 patients). In one patient significant tibial tunnel enlargement was to be found. At a follow up of 24 months, KT 1000 was <2 mm side to side difference and the pivot shift test was negative in all patients.
Conclusion:
Revision of a primary vertical ACL reconstruction can be safely performed using a double bundle reconstruction with two femoral tunnels in a two medial portal technique and one tibial tunnel technique. The femoral tunnel need to be located in the anatomic origin of the AM and PL bundle.
Clinical Relevance:
Femoral tunnel placement in the notch of the intercondylar notch should be avoided. In these cases without significant tunnel enlargement, a primary double bundle revision with two femoral and one tibial tunnel can be performed.