Related Experiment Video
Updated: Jul 10, 2026

Colon Ascendens Stent Peritonitis (CASP) - a Standardized Model for Polymicrobial Abdominal Sepsis
Published on: December 18, 2010
Vernix caseosa peritonitis
1Women and Children's Division, Barnet and Chase Farm Hospitals NHS Trust, Chase Farm Hospital, Enfield, UK. Dseloojeme@aol.com

Vernix caseosa peritonitis (VCP) is a rare and serious complication of caesarean section. It is thought to occur as a result of spillage of amniotic fluid and or meconium into the maternal peritoneal cavity at caesarean section. It manifests as an acute abdomen days to weeks after a seemingly uncomplicated caesarean section. Only 18 cases have been reported in the literature and all but one are from the USA. The pathophysiology is incompletely understood. In the past, the management of VCP included a laparotomy and removal of suspected abdominal organs which were invariably found to be normal on histopathological examination. However, the characteristic intraoperative finding was a cheesy white exudate that coats the visceral organs. The organs themselves were not inflamed. Histological examination of biopsy specimen of the cheesy exudates is the only way to make a diagnosis of VCP. This would reveal anucleate squamous cells along with lanugo hair and foreign body giant cell reaction. From recent case reports, peritoneal lavage appears to be the mainstay of treatment of VCP. Increased awareness of this condition is crucial so that it is considered in the differential diagnosis of post-caesarean acute abdomen thereby avoiding the unnecessary removal of healthy intra-abdominal organs. This review article summarises the current state of knowledge on VCP.
Vernix caseosa peritonitis (VCP) is a rare and serious complication of caesarean section. It is thought to occur as a result of spillage of amniotic fluid and or meconium into the maternal peritoneal cavity at caesarean section. It manifests as an acute abdomen days to weeks after a seemingly uncomplicated caesarean section. Only 18 cases have been reported in the literature and all but one are from the USA. The pathophysiology is incompletely understood. In the past, the management of VCP included a laparotomy and removal of suspected abdominal organs which were invariably found to be normal on histopathological examination. However, the characteristic intraoperative finding was a cheesy white exudate that coats the visceral organs. The organs themselves were not inflamed. Histological examination of biopsy specimen of the cheesy exudates is the only way to make a diagnosis of VCP. This would reveal anucleate squamous cells along with lanugo hair and foreign body giant cell reaction. From recent case reports, peritoneal lavage appears to be the mainstay of treatment of VCP. Increased awareness of this condition is crucial so that it is considered in the differential diagnosis of post-caesarean acute abdomen thereby avoiding the unnecessary removal of healthy intra-abdominal organs. This review article summarises the current state of knowledge on VCP.
Related Concept Videos
 01:07
Intestinal Obstruction II: Pathophysiology
 01:21
Acute Pancreatitis II: Pathophysiology
 01:21
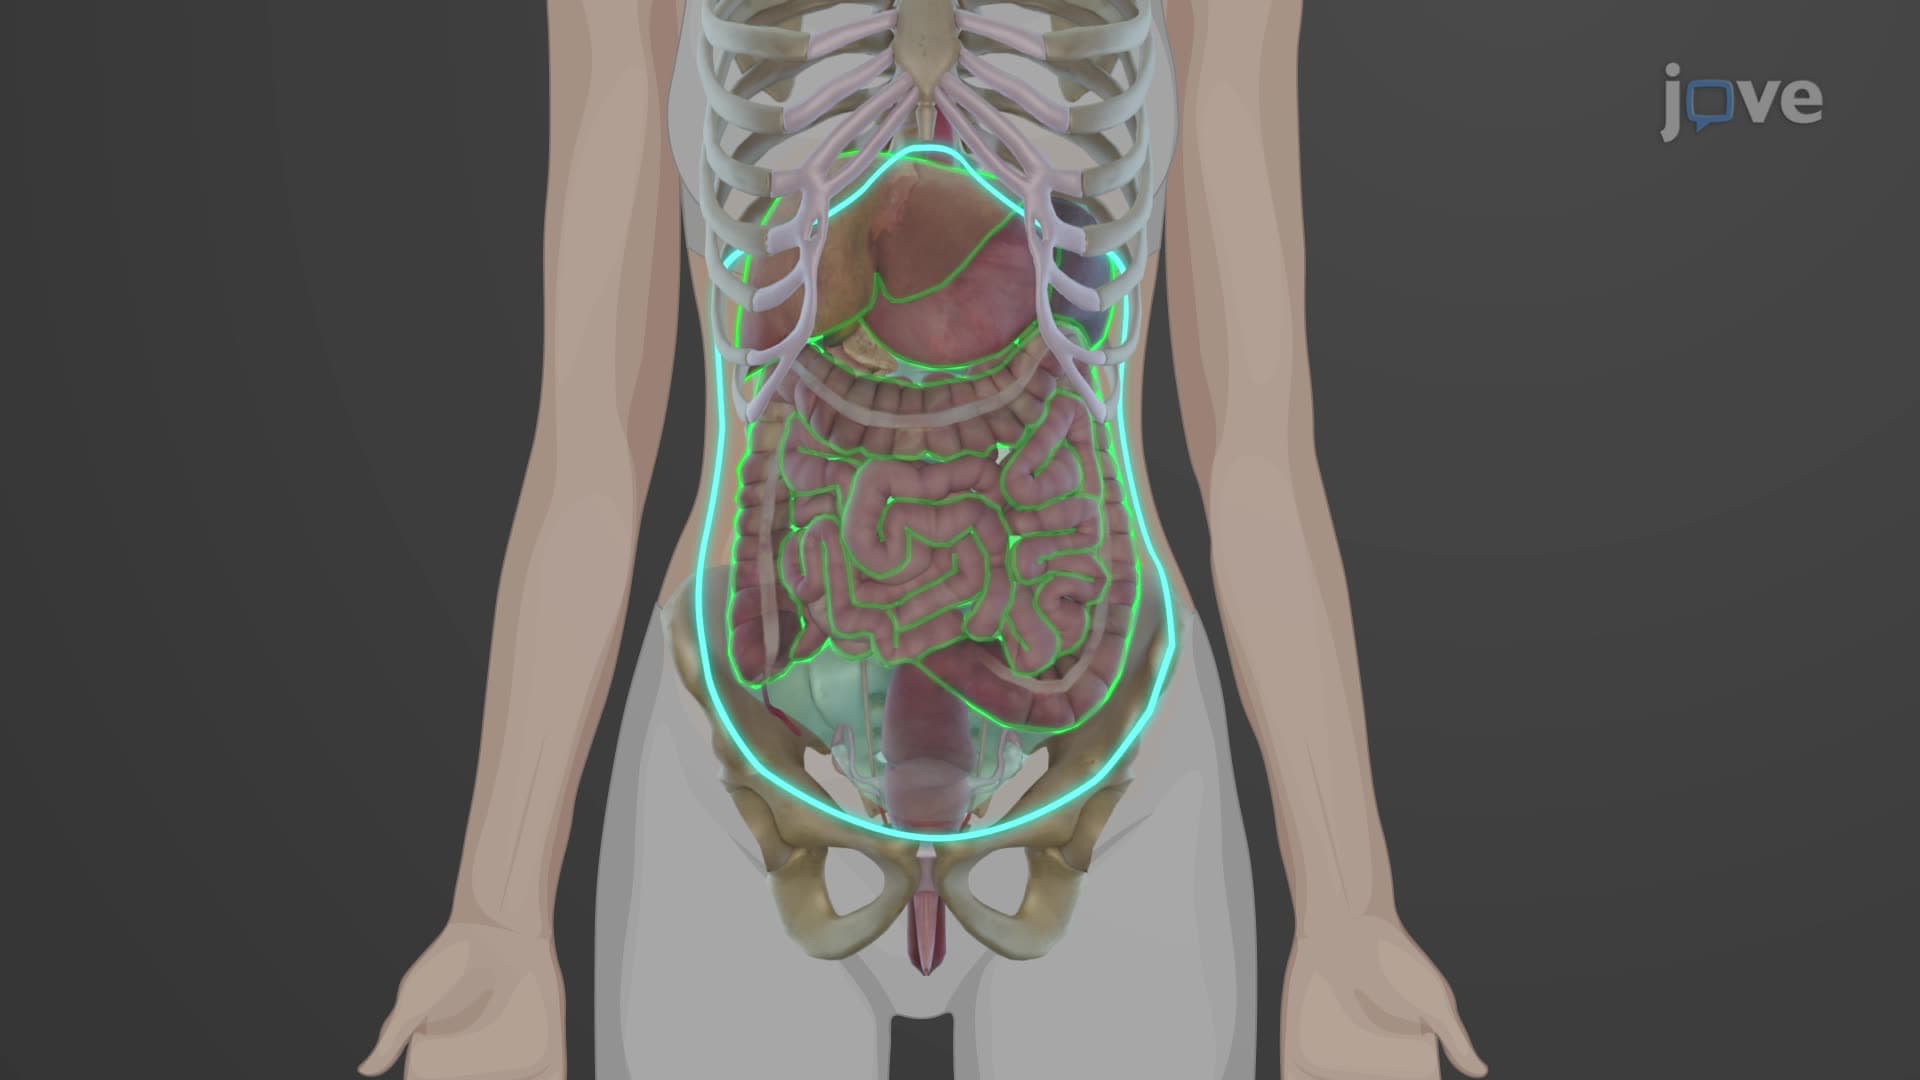
Peritoneum
Anatomy of the Peritoneum
The peritoneum is divided into two layers: the parietal peritoneum and the visceral...
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:25
Acute Pancreatitis I: Introduction
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management