Related Experiment Video
Updated: Jul 10, 2026
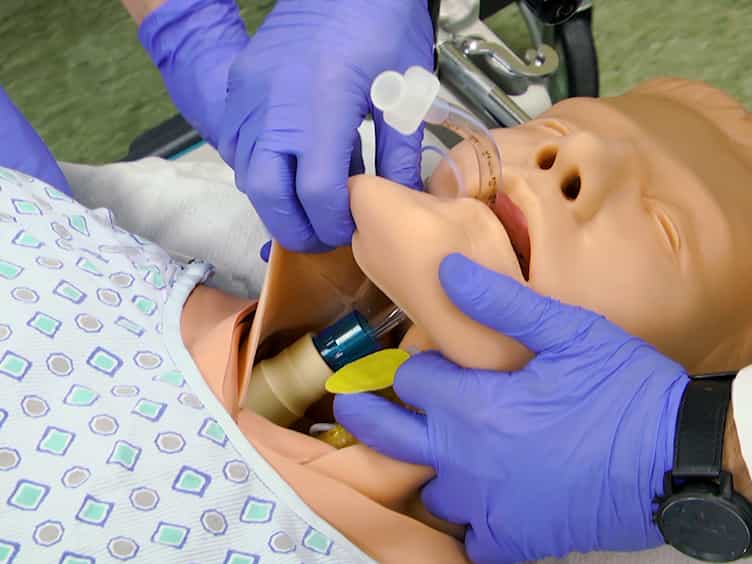
Mechanical Ventilation Boot Camp Curriculum
Published on: March 12, 2018
Home mechanical ventilation patients: a retrospective survey to identify level of burden in real life
M Vitacca1, J Escarrabill, G Galavotti
1Pulmonary Division, Fondazione S. Maugeri IRCCS, Gussago/Lumezzane, Italy. mvitacca@fsm.it

Background And Aim:
Home care for patients under home mechanical ventilation (HMV) may cause dramatic physical and economic burden in addition to the burden of time on family/caregivers and health care service (HCS) with difficult resource allocation decision-making. Our aims were: 1. To identify conditions causing major care burden in managing HMV patients according to family and payer's perspectives related to characteristics of the disease, dependency and accessibility; and 2. To find, if any, differences among diseases.
Methods:
A questionnaire was sent to eight pulmonary centres to identify factors connected with the greater care burden. Retrospective data of 792 patients still alive and in HMV was reviewed.
Results:
Compared to neuromuscular disorders (NM) and chest wall deformities, the COPD group have presented a statistically greater number of hospitalisations/yr (1.37 +/- 0.77), greater length of stay (13 +/- 10 days), higher number of outpatient visits/yr (2.55 +/- 1.73) or emergency room accesses/yr (0.74 +/- 1.08). Patients with NM diseases need more home care. The prevalence of one, two and three among five selected burden criteria (needs of MV > 12 hrs/day, tracheotomy, high dependency, distance from hospital, frequent hospitalisations) was respectively 19%, 30% and 33% of the cases; the NM was the group most represented.
Conclusions:
In HMV patients: 1. underlying disease, level of their dependency, hours spent under MV, presence of tracheotomy, home distance from hospital, hospital accesses are the causes of major care burden; and 2. as a novelty we have demonstrated that more than fifty percent of them present two or three contemporaneous criteria selected as care burden, being NM and COPD patients the most representative group necessitating of family's and HCS's care respectively.
Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...