Related Experiment Video
Updated: Jul 10, 2026


Imaging Features of Systemic Sclerosis-Associated Interstitial Lung Disease
Published on: June 16, 2020
Sarcoidosis
Hilario Nunes1, Diane Bouvry, Paul Soler
1Service de Pneumologie, Hôpital Avicenne, Assistance Publique Hôpitaux de Paris et Faculté de Médecine, Université Paris-Nord, 93009 Bobigny, France. hilario.nunes@avc.aphp.fr

Abstract:
Sarcoidosis is a multisystemic disorder of unknown cause characterized by the formation of immune granulomas in involved organs. It is an ubiquitous disease with incidence (varying according to age, sex, race and geographic origin) estimated at around 16.5/100,000 in men and 19/100,000 in women. The lung and the lymphatic system are predominantly affected but virtually every organ may be involved. Other severe manifestations result from cardiac, neurological, ocular, kidney or laryngeal localizations. In most cases, sarcoidosis is revealed by persistent dry cough, eye or skin manifestations, peripheral lymph nodes, fatigue, weight loss, fever or night sweats, and erythema nodosum. Abnormal metabolism of vitamin D3 within granulomatous lesions and hypercalcemia are possible. Chest radiography is abnormal in about 90% of cases and shows lymphadenopathy and/or pulmonary infiltrates (without or with fibrosis), defining sarcoidosis stages from I to IV. The etiology remains unknown but the prevailing hypothesis is that various unidentified, likely poorly degradable antigens of either infectious or environmental origin could trigger an exaggerated immune reaction in genetically susceptible hosts. Diagnosis relies on compatible clinical and radiographic manifestations, evidence of non-caseating granulomas obtained by biopsy through tracheobronchial endoscopy or at other sites, and exclusion of all other granulomatous diseases. The evolution and severity of sarcoidosis are highly variable. Mortality is estimated at between 0.5-5%. In most benign cases (spontaneous resolution within 24-36 months), no treatment is required but a regular follow-up until recovery is necessary. In more serious cases, a medical treatment has to be prescribed either initially or at some point during follow-up according to clinical manifestations and their evolution. Systemic corticosteroids are the mainstay of treatment of sarcoidosis. The minimal duration of treatment is 12 months. Some patients experience repeated relapses and may require long-term low-dose corticosteroid therapy during years. Other treatments (immunosuppressive drugs and aminoquinolins) may be useful in case of unsatisfactory response to corticosteroids, poor tolerance and as sparing agents when high doses of corticosteroids are needed for a long time. In some strictly selected cases refractory to standard therapy, specific antiTNF-alpha agents may offer precious improvement. Some patients benefit from topical corticosteroids.
Related Concept Videos
 01:26
Rocky Mountain Spotted Fever
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:30
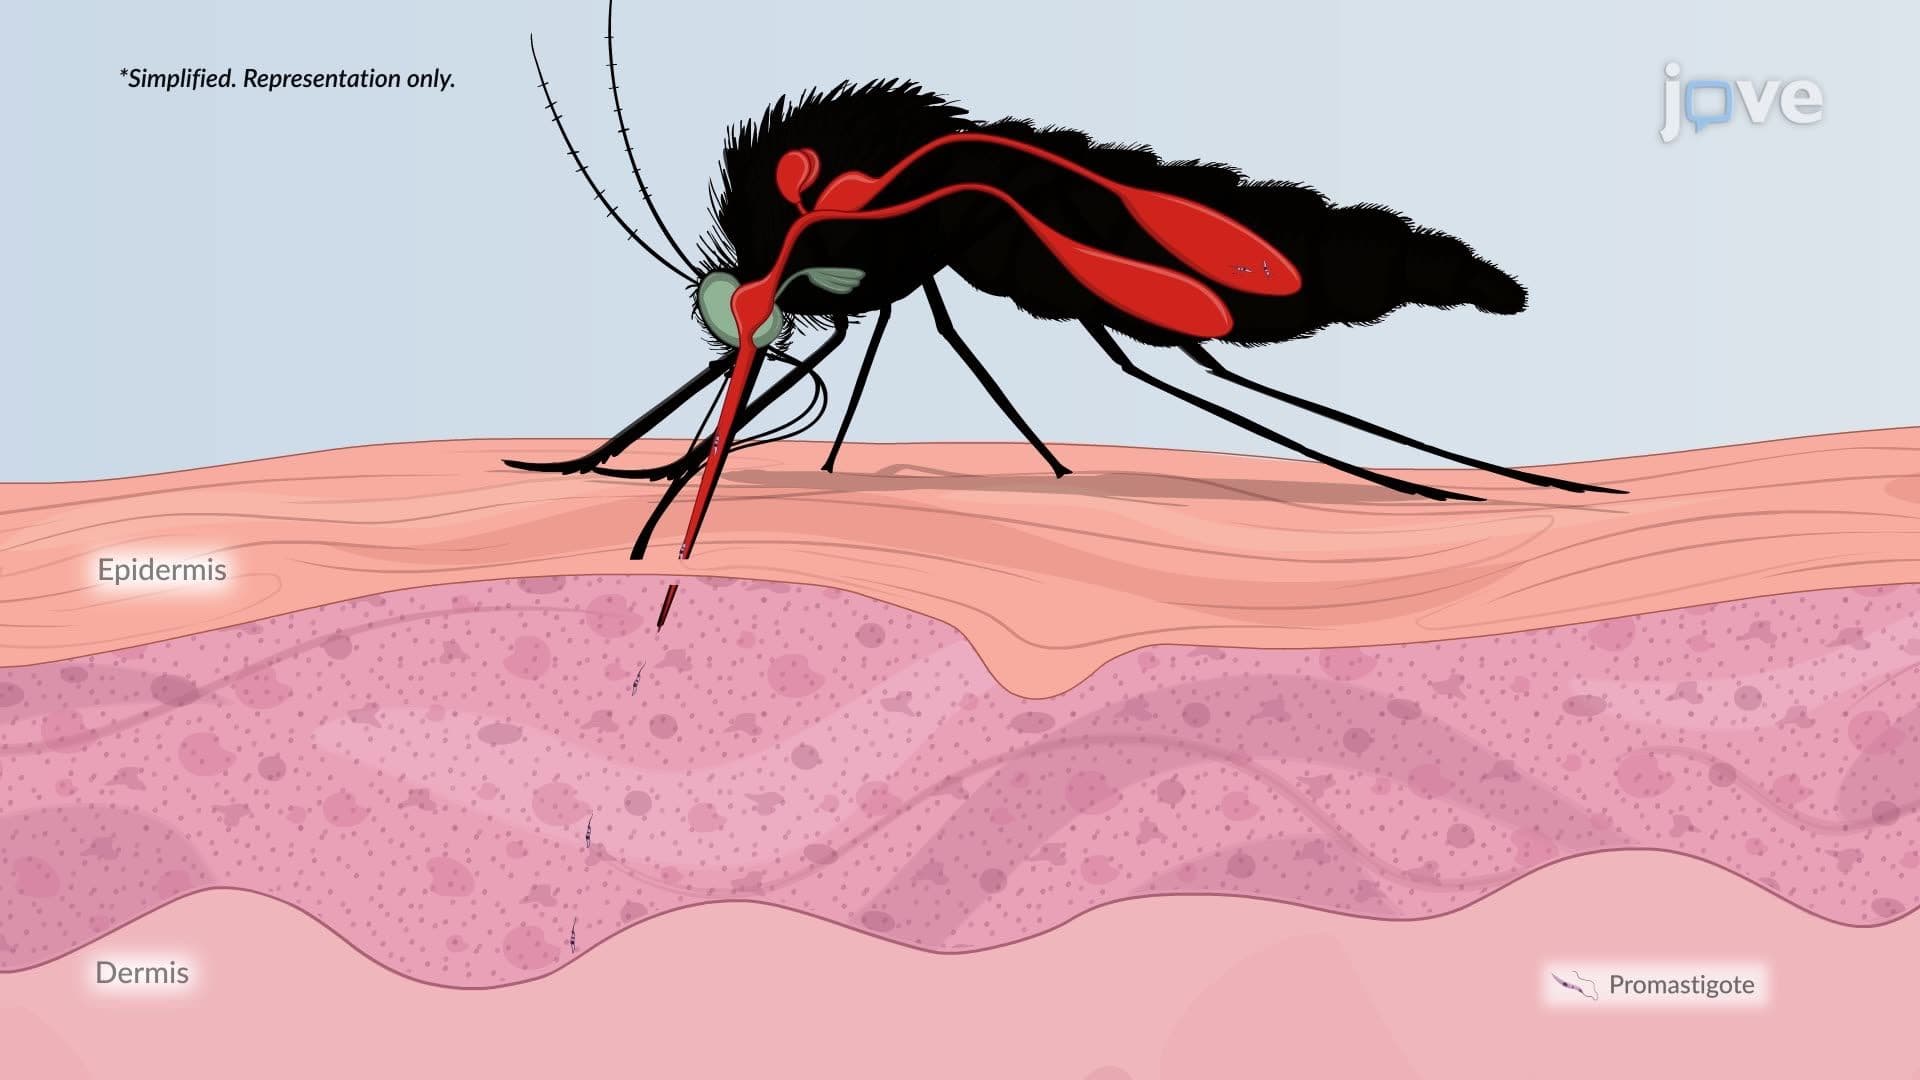
Leishmaniasis
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Toxoplasmosis
 01:17
Other Pulmonary Disorders