Related Experiment Video
Updated: Jul 10, 2026


A Modified Sonographic Algorithm for Image Acquisition in Life-Threatening Emergencies in the Critically Ill Newborn
Published on: April 7, 2023
Comparing different patterns for managing febrile children in the ED between emergency and pediatric physicians:
Vei-Ken Seow1, Aming Chor-Ming Lin, I-Yin Lin
1Emergency Department, Shin-Kong Wu Ho-Su Memorial Hospital, Taipei 111, Taiwan.

Insights
Pediatric physicians (PPs) showed higher guideline compliance for children with fever of unknown origin than emergency physicians (EPs), leading to fewer revisits but similar admission rates. This impacts pediatric fever management in emergency departments.
Area of Science:
- Pediatric Emergency Medicine
- Clinical Practice Guidelines
- Fever Management
Background:
- Management of pediatric fever of unknown origin in emergency departments (EDs) lacks standardized practice.
- Variations exist in how pediatric physicians (PPs) and emergency physicians (EPs) manage these cases.
- Existing practice guidelines aim to standardize care and improve patient outcomes.
Purpose of the Study:
- To compare practice patterns of PPs and EPs in managing pediatric fever of unknown origin in the ED.
- To correlate these practices with existing clinical guidelines.
- To evaluate the impact of different management strategies on patient outcomes.
Main Methods:
- Retrospective review of medical records for children (3-36 months) with fever of unknown origin.
- Telephone follow-up to assess subsequent healthcare utilization.
- Comparison of laboratory tests, ED length of stay (LOS), admission rates, and unscheduled revisits between PPs and EPs.
- Evaluation of guideline compliance based on patient presentation (toxic appearance, fever severity).
Main Results:
- Pediatric physicians admitted more toxic-appearing children and had fewer unscheduled revisits compared to EPs.
- For febrile children, PPs ordered more lab tests and had longer ED LOS but similar revisit rates.
- PPs admitted more non-toxic febrile children and ordered more tests, with longer ED LOS but no difference in revisit rates.
- Subsequent admission rates were similar across all groups and between physician types.
Conclusions:
- Pediatric physicians demonstrated higher adherence to practice guidelines for pediatric fever management.
- Higher guideline compliance by PPs correlated with a reduced rate of unscheduled revisits.
- No significant difference in subsequent admission rates was observed between PPs and EPs.
Objective:
The management of children with fever of indefinite source still remains controversial. This study aimed to compare different practice patterns between pediatric physicians (PPs) and emergency physicians (EPs) in the management of pediatric fever in the emergency department (ED) and correlate them to existing practice guidelines. Their impact on patient outcomes was also discussed.
Methods:
Medical records of patients 3 to 36 months of age who presented to the ED with fever of indefinite source from June 1 to December 31, 2006, were retrospectively reviewed on day 5 after the patient's first visit. At the same time, telephone follow-up was carried out to determine whether the patient had been visiting or being admitted to another clinic or hospital after discharge. Variation in practice patterns were compared for the number of laboratory tests, ED length of stay (LOS), and the rate of immediate admission. Patient outcomes were measured as the rate of unscheduled revisit within 72 hours and the rate of subsequent admission. Compliance with existing practice guidelines between PPs and EPs were evaluated by dividing all eligible patients into 3 groups: (1) toxic appearing patients (group A), (2) nontoxic patients with body temperature (BT) > or = 39 degrees C (group B), and (3) nontoxic patients with BT below 39 degrees C (group C).
Results:
A total of 345 patients who met the inclusion and exclusion criteria were enrolled into this study. Pediatric physicians and EPs treated 163 and 182 febrile children, respectively. In group A, PPs admitted more patients than EPs (41% vs 12 %), whereas more unscheduled revisits were seen in EP-treated patients (44% vs 10%). In group B, PPs ordered more laboratory tests than EPs (2.3 vs 0.7 tests per patient), and their patients also had a longer ED LOS (3.4 +/- 3.2 vs 1.5 +/- 1.1 hours). However, no difference was found in their rates of immediate admission and unscheduled revisit. In group C, PPs admitted more patients (15% vs 0%) and ordered more laboratory tests (2.0 vs 0.5 tests/patient) than EPs. Longer ED LOS (3.3 +/- 3.9 vs 1.0 +/- 1.4 hours) was also noted among PP-treated patients. However, no difference was noted in their rates of unscheduled revisit. In all groups, the rates of subsequent admission were similar.
Conclusion:
Compliance with existing practice guidelines (admit the toxic cases and work up those with BT > or = 39 degrees C) was higher among PPs, which resulted in a lower rate of unscheduled revisit, but no significant difference was found in the rate of subsequent admission.
Related Concept Videos
 01:26
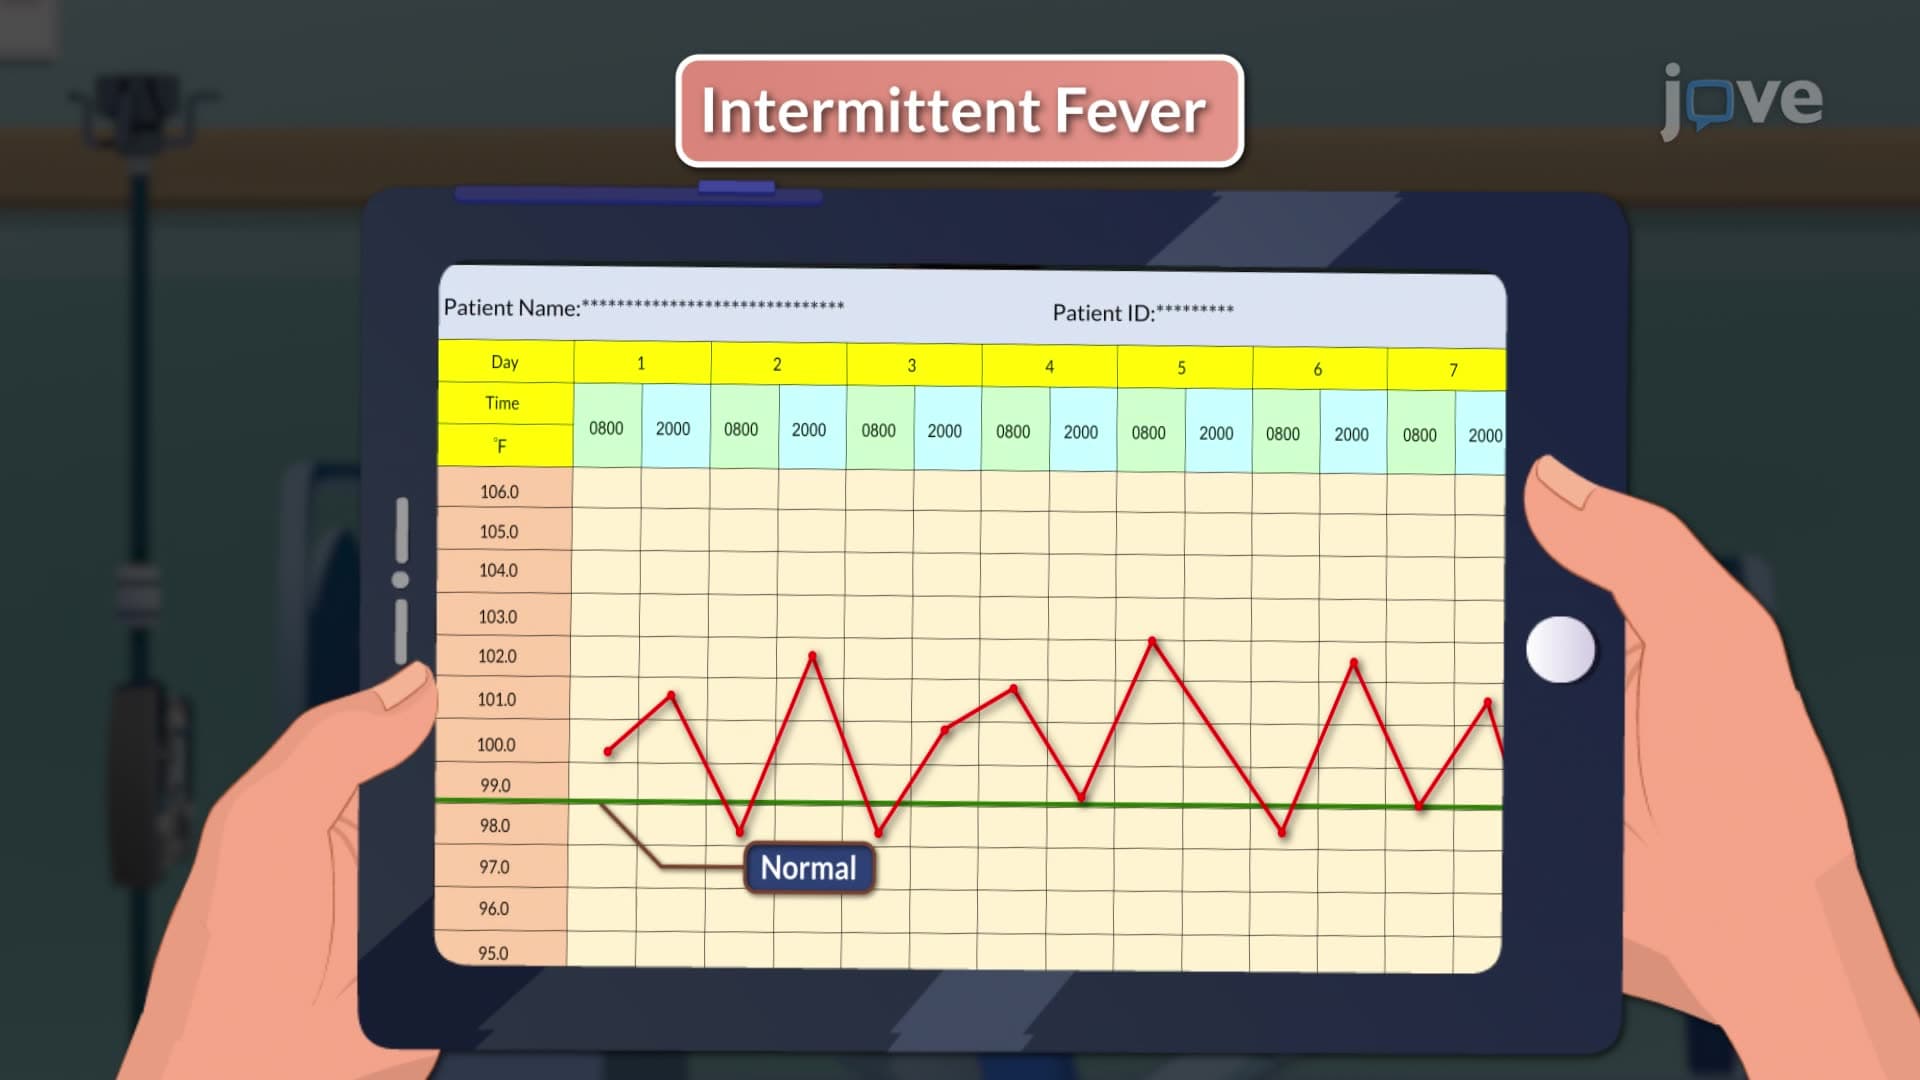
Patterns of Fever
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:29
Drug Dosing: Infants and Children
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism