Related Experiment Video
Updated: Jul 10, 2026
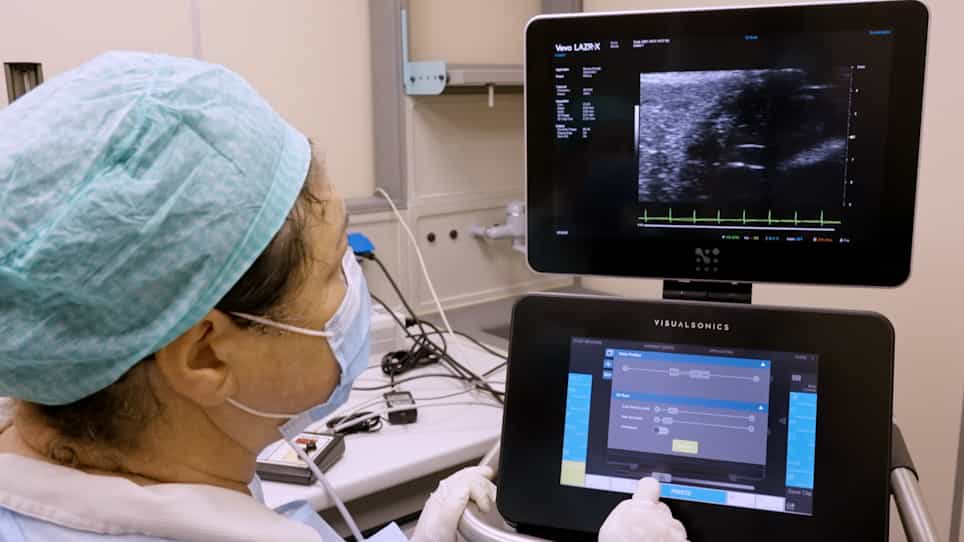
Analysis of Lymph Node Volume by Ultra-High-Frequency Ultrasound Imaging in the Braf/Pten Genetically Engineered Mouse Model of Melanoma
Published on: September 8, 2021
Staged excision for lentigo maligna and lentigo maligna melanoma: A retrospective analysis of 117 cases
Carole Hazan1, Stephen W Dusza, Ruby Delgado
1Department of Dermatology, Memorial Sloan-Kettering Cancer Center, New York, New York 10022, USA.

Background:
Complete surgical excision for lentigo maligna (LM) and LM melanoma (LMM) in the head and neck region may be challenging because of potential significant subclinical extension.
Objective:
We sought to review clinical and histologic features of LM and LMM and determine surgical margin necessary for complete excision.
Methods:
We conducted a retrospective study of 117 LM and LMM cases treated with a staged margin-controlled excision technique with rush paraffin-embedded sections.
Results:
The mean total surgical margin required for excision of LM was 7.1 mm and was 10.3 mm for LMM. Of the tumors diagnosed as LM on initial biopsy specimen, 16% were found to have unsuspected invasion. Total surgical margin was associated with initial clinical lesion diameter.
Limitations:
Retrospective and single-institution experience are limitations.
Conclusion:
This study corroborates that the standard excision margins for LM and LMM are often inadequate and occult invasive melanoma occurs in LM. An excision technique with permanent sections using a team of dermatopathology and surgery that carefully examines the central tumor and the surgical margins is reliable for the treatment of LM and LMM.

