Related Experiment Video
Updated: Jul 10, 2026
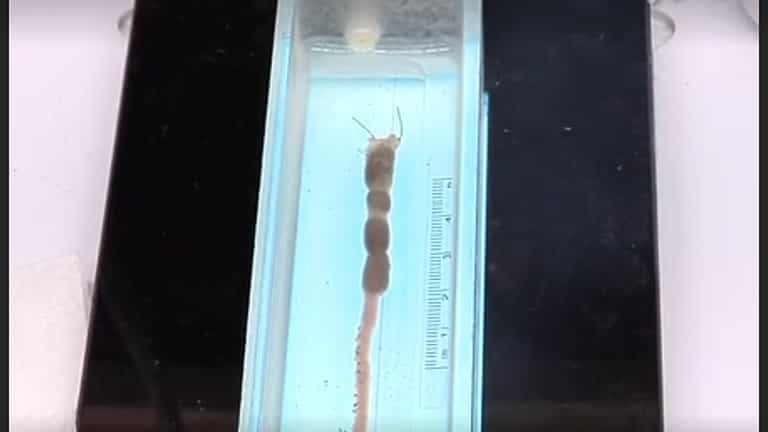

Gastrointestinal Motility Monitor (GIMM)
Published on: December 1, 2010
Gastrointestinal motility after digestive surgery
Erito Mochiki1, Takayuki Asao, Hiroyuki Kuwano
1Department of General Surgical Science, Gunma University Graduate School of Medicine, 3-39-22 Showa-machi, Maebashi, Gunma, Japan.

Gastrointestinal (GI) motility dysfunction is a common complication of any abdominal surgical procedure. During fasting, the upper GI tract undergoes a cyclic change in motor activity, called the interdigestive migrating motor contraction (IMC). The IMC is divided into four phases, with phase III having the most characteristic activity. After digestive surgery, GI motility dysfunction shows a lack of a fed response, less phase II activity, more frequent phase III activity of the IMC, and some phase III activity migrating orally. Postoperative symptoms have been related to motor disturbances, such as interrupted or retrograde phase III or low postprandial activity. The causes of GI disorder are autonomic nervous dysfunction and GI hormone disruptions. The administration of a motilin agonist can induce earlier phase III contractions in the stomach after pancreatoduodenectomy. For nervous dysfunction, an inhibitory sympathetic reflux is likely to be important in postoperative motility disorders. Until recently, treatment for gut dysmotility has consisted of nasogastric suction, intravenous fluids, and observation; however, more effective treatment methods are being reported. Recent discoveries have the potential to decrease postoperative gut dysmotility remarkably after surgery.
Gastrointestinal (GI) motility dysfunction is a common complication of any abdominal surgical procedure. During fasting, the upper GI tract undergoes a cyclic change in motor activity, called the interdigestive migrating motor contraction (IMC). The IMC is divided into four phases, with phase III having the most characteristic activity. After digestive surgery, GI motility dysfunction shows a lack of a fed response, less phase II activity, more frequent phase III activity of the IMC, and some phase III activity migrating orally. Postoperative symptoms have been related to motor disturbances, such as interrupted or retrograde phase III or low postprandial activity. The causes of GI disorder are autonomic nervous dysfunction and GI hormone disruptions. The administration of a motilin agonist can induce earlier phase III contractions in the stomach after pancreatoduodenectomy. For nervous dysfunction, an inhibitory sympathetic reflux is likely to be important in postoperative motility disorders. Until recently, treatment for gut dysmotility has consisted of nasogastric suction, intravenous fluids, and observation; however, more effective treatment methods are being reported. Recent discoveries have the potential to decrease postoperative gut dysmotility remarkably after surgery.
More Related Videos

Related Concept Videos
 01:20
Gastrointestinal Motility Disorders
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:23
Drugs Affecting GI Tract Motility: Serotonin Receptor Agonists
 01:26
Imaging Studies III: Gastrointestinal Motility Studies and Virtual Colonoscopy
Radionuclide Testing
Radionuclide testing is a sophisticated medical technique for assessing gastrointestinal motility. It focuses on gastric emptying and colonic transit time. Radioactive markers track the movement of food through the digestive system, providing insights into gastrointestinal disorders.
In gastric emptying studies, a meal's liquid and solid...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:28
Drugs Affecting GI Tract Motility: Dopamine Receptor Antagonists