Related Experiment Video
Updated: Jul 10, 2026

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Persistent left-sided superior vena cava--a pacing challenge
A L Innasimuthu1, G K Rao, P Wong
1Aintree Cardiac Centre, University Hospital Aintree, Liverpool, UK. antonyleslie@yahoo.co.in

Insights
This study details successful dual chamber pacemaker implantation in patients with a rare left sided superior vena cava (LSVC). Techniques for lead placement via subclavian veins are described for this anatomical variation.
Area of Science:
- Cardiology
- Medical Devices
- Anatomy
Background:
- Left sided superior vena cava (LSVC) is a rare congenital anomaly occurring in 0.3% of the population.
- LSVC typically drains into the right atrium via the coronary sinus.
- Pacemaker implantation requires careful consideration of venous anatomy.
Observation:
- Two cases of dual chamber permanent pacemaker implantation are presented.
- Access was gained via the left or right subclavian vein.
- Pacing leads were advanced through the LSVC into the right atrium and ventricle.
Findings:
- Successful lead placement was achieved in both patients with LSVC.
- Specific techniques involving stylet shaping and fluoroscopy guided lead positioning.
- Active fixation atrial leads ensured satisfactory atrial lead placement.
Implications:
- Recognizing LSVC is crucial for safe transvenous lead placement, especially in emergencies.
- Modified lead manipulation techniques are effective for pacemaker implantation in patients with LSVC.
- Awareness of LSVC can prevent complications like cardiac perforation and tamponade.
Abstract:
A left sided superior vena cava (LSVC) occurs in 0.3% of the population. LSVC normally drains into the right atrium through a dilated coronary sinus. We illustrate two cases of dual chamber permanent pacemaker implantation by using (1) left subclavian vein in a 35-year-old woman with symptomatic Mobitz type II atrioventricular block; and (2) right subclavian vein in a 64-year-old man who was hospitalized with bradycardia, complete heart block, and alternating bundle branch block. After accessing the subclavian vein, the pacing leads were advanced into the LSVC, which was situated to the left of the vertebral column in the mediastinum. The leads followed the course of the LSVC medially before entering into the right atrium. Once inside the right atrium, the ventricular lead made a U-turn towards the tricuspid valve and into the right ventricle by shaping the stylet, and it was helped by right atrial contraction. An active fixation atrial lead was used in both cases to secure a satisfactory location within the right atrium. A small volume of contrast can be injected into the pacing sheath to visualize the coronary sinus opening into the right atrium, and the right ventricle. Fluoroscopy in oblique views can be helpful in guiding the atrial lead into the anteriorly positioned atrial appendage. In emergency transvenous ventricular temporary pacing where the subclavian or internal jugular vein is used, it is important to recognize the presence of a LSVC. The lead should first be directed into the right atrium and then looped back into the right ventricle. Excessive force must be avoided to prevent cardiac perforation and tamponade. If this is not successful, access through a femoral vein should be attempted.
More Related Videos
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
 06:04
Upper-extremity Approach for Secondary Access in Transfemoral Transcatheter Aortic Valve Implantation
Published on: August 8, 2025
Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:25
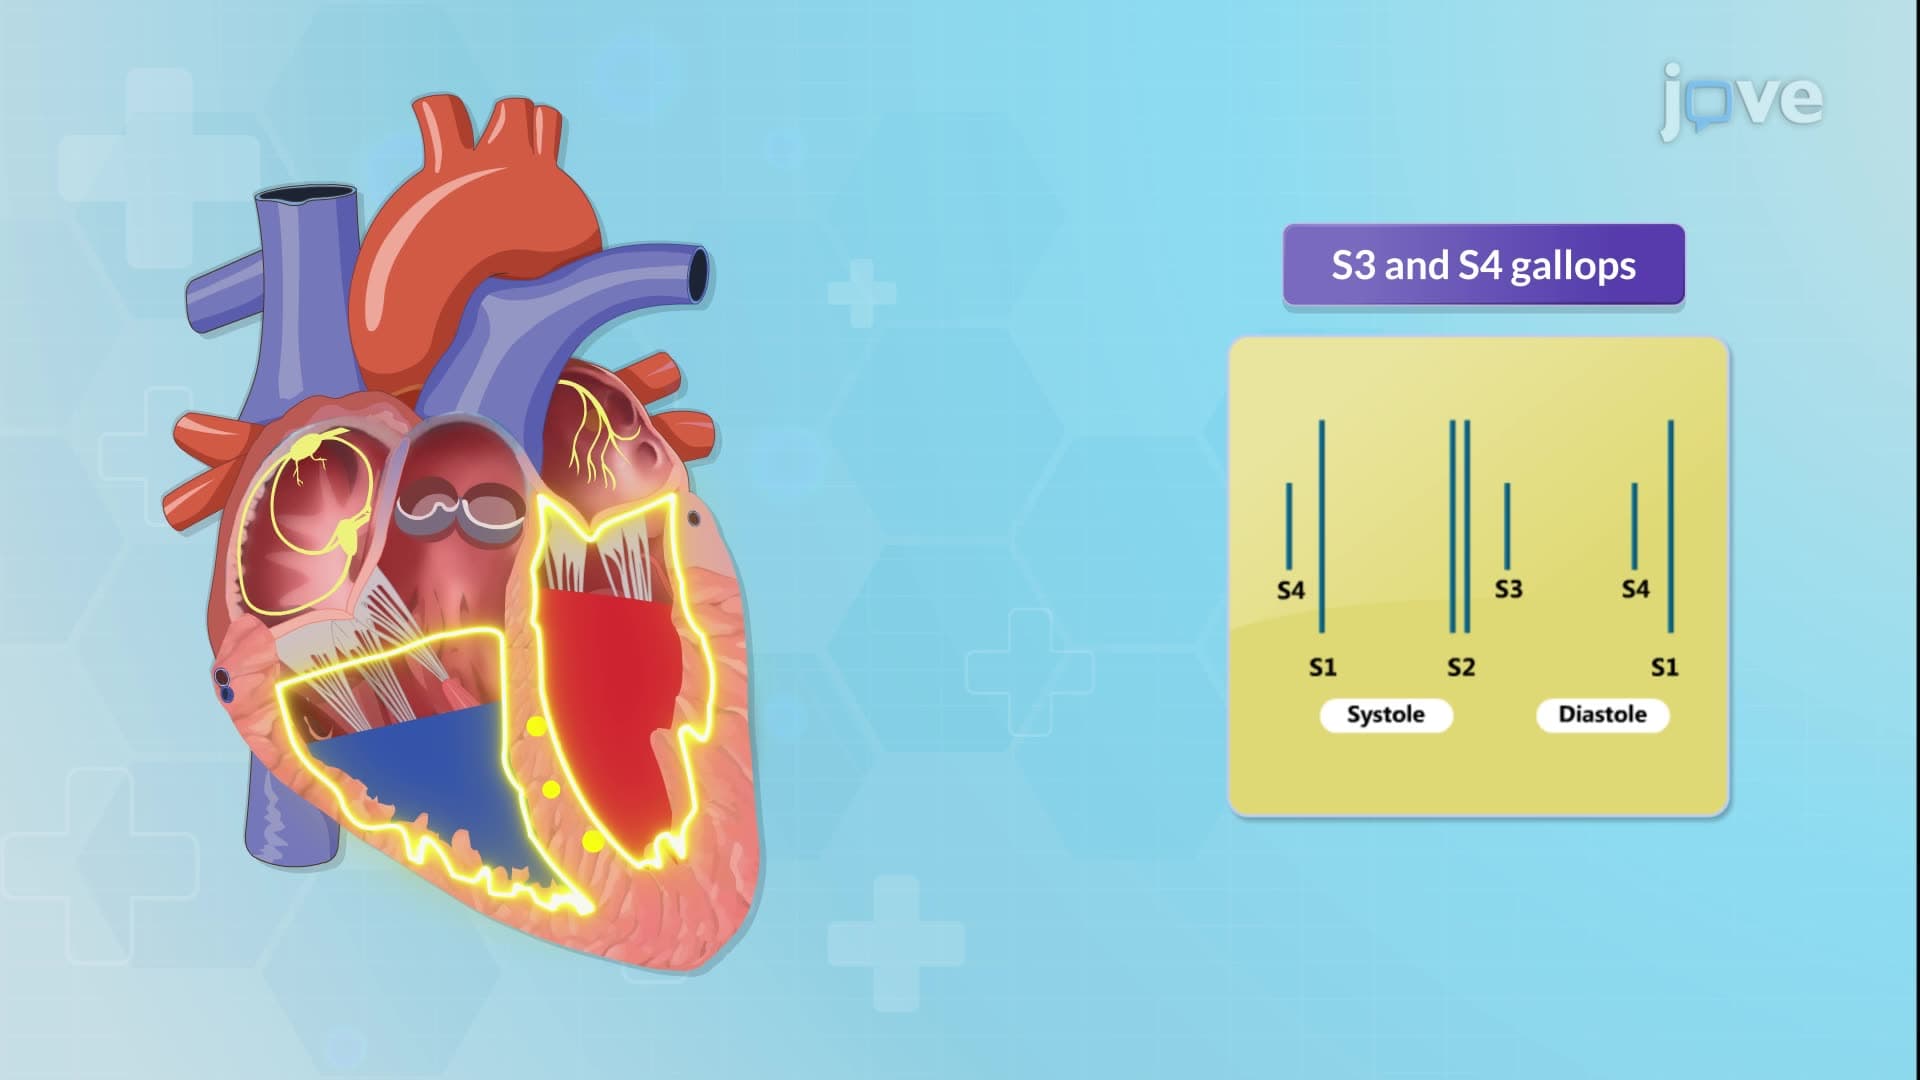
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy VI: Nursing Management