Related Experiment Video
Updated: Jul 9, 2026
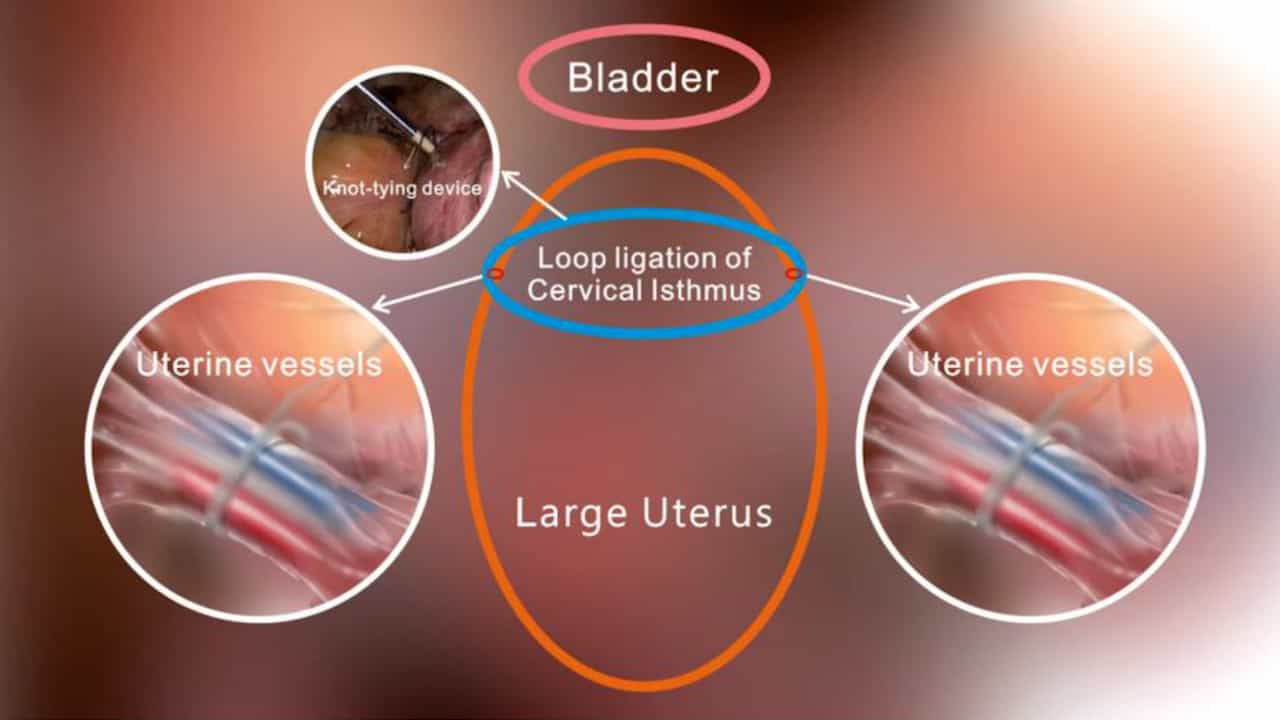

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
[Cesarean section for case with preoperatively-suspected placenta accrete followed by hysterectomy due to
Yasuo Kono1, Maiko Sawada, Tatsuhiko Kano
1Department of Anesthesiology, Kurume University School of Medicine, Kurume 830-0011.

A 42-yr-old pregnant woman highly suspicious of the placenta accreta was scheduled for cesarean section (c-section) under general anesthesia. She had received emergency c-section for the placenta previa at 36 years of age and three episodes of intrauterine curettage for spontaneous abortion. While the possibility of placenta accreta was pointed out and the risks accompanying with it were explained at the 7th week of pregnancy, she insisted on having a baby. C-section was intended at around the 30th week of pregnancy and 1,200 ml of autologus blood was stored for the predictable massive bleeding. Bilateral embolization of the internal iliac artery was also planned. The baby was delivered uneventfully. However, the adherence of the placenta was so tight that the placenta could not be separated from the uterine wall. The arterial embolization immediately after the delivery did not work as effectively as to control massive bleeding. It took about 1 hour to control the massive bleeding of up to 9000 ml by difficult hysterectomy. Since we had prepared for such a situation, we could well catch up with the massive bleeding. The mother and baby were discharged well from the hospital 29th day after the c-section.
A 42-yr-old pregnant woman highly suspicious of the placenta accreta was scheduled for cesarean section (c-section) under general anesthesia. She had received emergency c-section for the placenta previa at 36 years of age and three episodes of intrauterine curettage for spontaneous abortion. While the possibility of placenta accreta was pointed out and the risks accompanying with it were explained at the 7th week of pregnancy, she insisted on having a baby. C-section was intended at around the 30th week of pregnancy and 1,200 ml of autologus blood was stored for the predictable massive bleeding. Bilateral embolization of the internal iliac artery was also planned. The baby was delivered uneventfully. However, the adherence of the placenta was so tight that the placenta could not be separated from the uterine wall. The arterial embolization immediately after the delivery did not work as effectively as to control massive bleeding. It took about 1 hour to control the massive bleeding of up to 9000 ml by difficult hysterectomy. Since we had prepared for such a situation, we could well catch up with the massive bleeding. The mother and baby were discharged well from the hospital 29th day after the c-section.
