Related Experiment Video
Updated: Sep 12, 2026
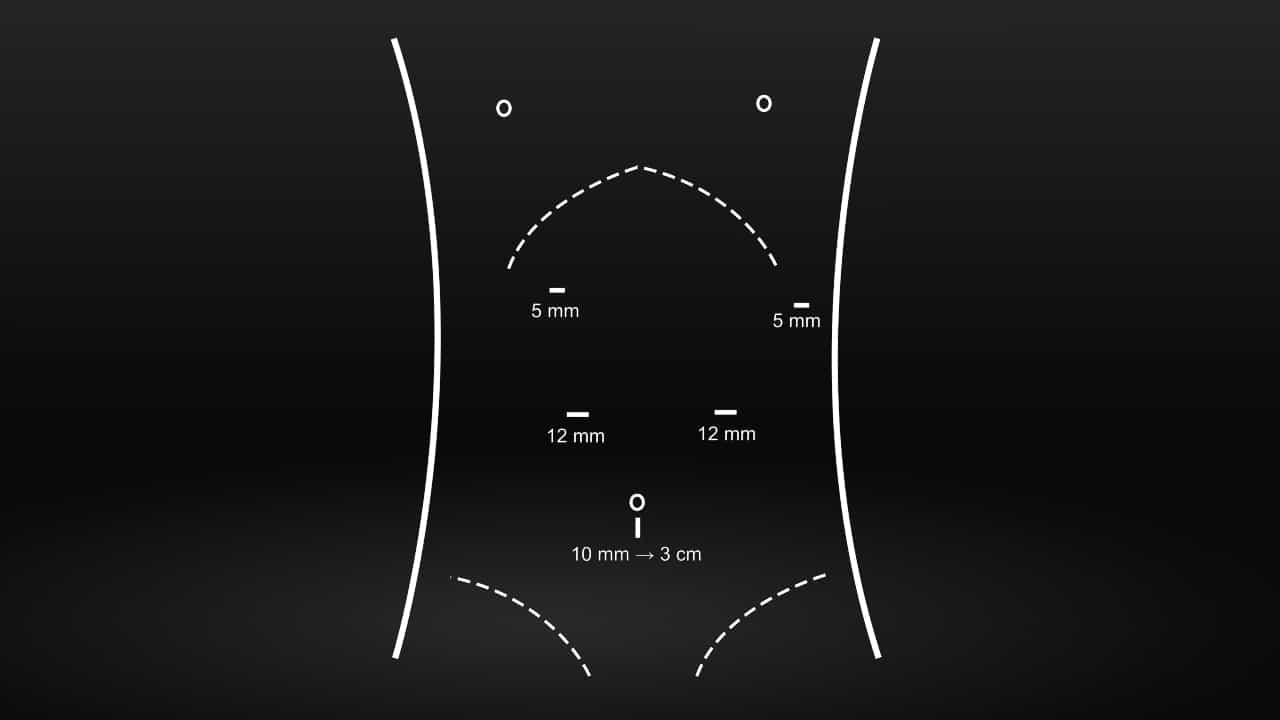
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Endoscopic sclerotherapy in the management of gastric variceal haemorrhage
A E Gimson1, D Westaby, R Williams
1Liver Unit, King's College Hospital and School of Medicine and Dentistry, London, United Kingdom.

The value of injection sclerotherapy in the management of active gastric variceal bleeding is unclear. A retrospective study was therefore performed of 46 episodes of acute variceal haemorrhage in 41 patients who were treated by endoscopic sclerotherapy. The site of gastric variceal haemorrhage was the lesser curve (Group 1) in 13, within a hiatus hernia (Group 2) in six, and fundal with or without associated oesophageal varices (Type 3) in 22 cases. Haemostasis was achieved by sclerotherapy in 54%, 71.4% and 26%, respectively. After additional measures including balloon tamponade or surgery 85% of the Group 1 cases had stopped bleeding significantly more frequently than was observed in Group 3 (44.4%). More patients in Group 3 died due to uncontrolled bleeding (41%) than in Group I (7.7%). Hospital mortality depended on the severity of the liver disease with 15% of Child's grade A and 56% of grade C cases dying. It is concluded that endoscopic sclerotherapy of gastric varices should be reserved only for lesser curve or hiatal varices and that early surgery (or sclerotherapy using tissue adhesive) be considered for variceal haemorrhage originating from fundal varices.
The value of injection sclerotherapy in the management of active gastric variceal bleeding is unclear. A retrospective study was therefore performed of 46 episodes of acute variceal haemorrhage in 41 patients who were treated by endoscopic sclerotherapy. The site of gastric variceal haemorrhage was the lesser curve (Group 1) in 13, within a hiatus hernia (Group 2) in six, and fundal with or without associated oesophageal varices (Type 3) in 22 cases. Haemostasis was achieved by sclerotherapy in 54%, 71.4% and 26%, respectively. After additional measures including balloon tamponade or surgery 85% of the Group 1 cases had stopped bleeding significantly more frequently than was observed in Group 3 (44.4%). More patients in Group 3 died due to uncontrolled bleeding (41%) than in Group I (7.7%). Hospital mortality depended on the severity of the liver disease with 15% of Child's grade A and 56% of grade C cases dying. It is concluded that endoscopic sclerotherapy of gastric varices should be reserved only for lesser curve or hiatal varices and that early surgery (or sclerotherapy using tissue adhesive) be considered for variceal haemorrhage originating from fundal varices.
Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care