Related Experiment Video
Updated: Jul 8, 2026
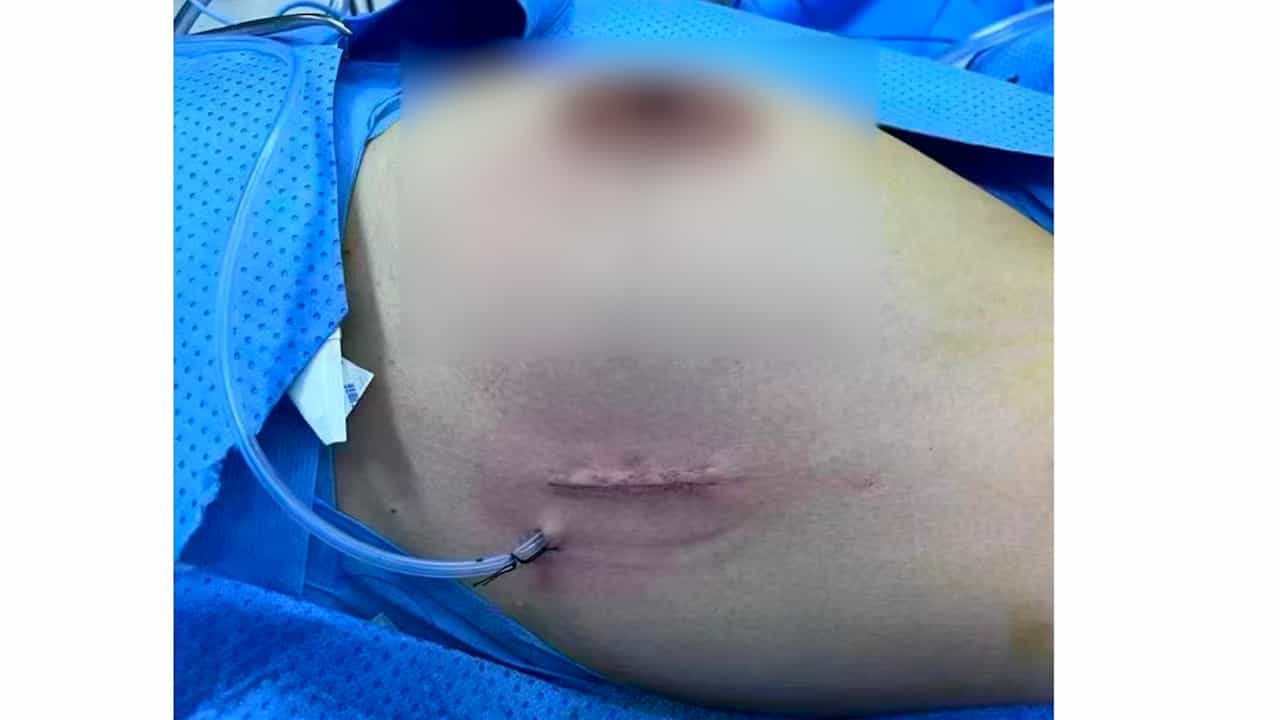

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Lymphatic mapping in patients with primary or recurrent breast cancer following previous axillary surgery

Aims:
To evaluate the feasibility of lymphatic mapping in breast cancer patients after previous axillary surgery and to identify parameters associated with mapping failure.
Methods:
Lymphatic mapping using peritumoural injection of blue dye and a radiocolloid was attempted in 30 patients with primary (n=7) or recurrent (n=23) breast cancer and a history of previous axillary lymph node dissection or sentinel node biopsy.
Results:
Lymphatic mapping identified a mean number of 1.6 (range 1-3) lymph nodes in 19 of 30 patients (identification rate 63%). The lymph nodes were removed from the ipsilateral axilla (n=13), the internal mammary chain (n=2), both the internal mammary nodes and the axilla (n=2), the interpectoral space (n=1) and the contralateral axilla (n=1). Four of 19 patients revealed a positive lymph node. Fifteen of 19 patients had a negative lymph node. Axillary lymph node dissection was done in 13 of 15 patients but found no positive nodes (false negative rate=0). A negative lymphoscintigram (p<0.001) and a number of more than 10 lymph nodes removed at the time of initial surgery (p=0.02) were significantly associated with a mapping failure.
Conclusion:
Lymphatic mapping following prior axillary surgery was accurate but associated with a low identification rate. The lymphatic drainage pattern was unpredictable and the use of a radionuclide was necessary for a successful mapping procedure.
