Related Experiment Videos
Comparison of acid-base models for prediction of hospital mortality after trauma
Lewis J Kaplan1, John A Kellum
1Department of Surgery, Section of Trauma, Critical Care, and Surgical Emergencies, Yale University School of Medicine, New Haven, CT 06520, USA. Lewis.Kaplan@yale.edu

Abstract:
This study determines whether mortality after major trauma is predicted by the strong ion gap (SIG) and whether recent refinements in the calculation of SIG improve its predictive value. The design was an observational, retrospective review of trauma patients admitted on a single service at a level 1 facility. The setting was an urban level 1 trauma facility. An unselected cohort of patients sustaining blunt and/or penetrating injury requiring intensive care unit care was chosen. There were no interventions. Age, injury mechanism, survival, arterial blood gases, hemoglobin, albumin, electrolytes, lactate, standard base deficit, strong ion difference (SID), buffer base, and SIG were analyzed. Patients were grouped into survivors and nonsurvivors according to in-hospital survival truncated to 28 days. Multivariate logistic regression was used for further analysis of univariate predictors of mortality, and receiver-operator characteristic curves were generated for mortality. Both nonsurvivors (n = 26) and survivors (n = 52) were similar with respect to age (31.9 +/- 11.5 vs. 33.5 +/- 11.6 years) and injury mechanism (blunt 61% vs. 58%) Nonsurvivors were more likely to have multicavity injury (54% vs. 26%; P < 0.01) than survivors. Nonsurvivor and survivor pH (7.36 +/- 0.15 vs. 7.38 +/- 0.09), HCO3(-) (20.4 +/- 3.9 vs. 21.7 +/- 2.5 mEq/L; P = 0.11), albumin (3.6 +/- 0.7 vs. 3.5 +/- 0.5 gm/dL), lactate (2.9 +/- 2.5 vs. 2.3 +/- 1.3 mmol/L; P = 0.24), and phosphate (3.1 +/- 0.9 vs. 3.4 +/- 0.8 mEq/L; P = 0.26) were similar. Forty-two percent of nonsurvivors had normal lactate levels, whereas 33% of survivors had lactic acidosis. However, the apparent SID (41.0 +/- 4.2 vs. 36.7 +/- 5.5 mEq/L; P < 0.001), effective SID (32.7 +/- 4.2 vs. 35.4 +/- 4.9 mEq/L; P = 0.019), and SIG (8.3 +/- 4.4 vs. 1.3 +/- 3.6 mEq/L; P < 0.001) were all significantly different between nonsurvivors and survivors. Only one (2%) survivor had an SIG greater than 5 mEq/L, and only two (7%) nonsurvivors had an SIG less than 5 mEq/L. Admission pH, HCO3-, and lactate were poor predictors of hospital mortality after trauma. An elevated SIG presaged mortality after injury and should be assessed on admission.
Related Concept Videos
 01:26
Pharmacokinetic Models: Comparison and Selection Criterion
Physiological models take a detailed approach by considering specific molecular processes. They can predict drug distribution, metabolism, and elimination changes, providing a comprehensive understanding of how drugs interact with the body.
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and HCO3− values are examined to...
 02:58
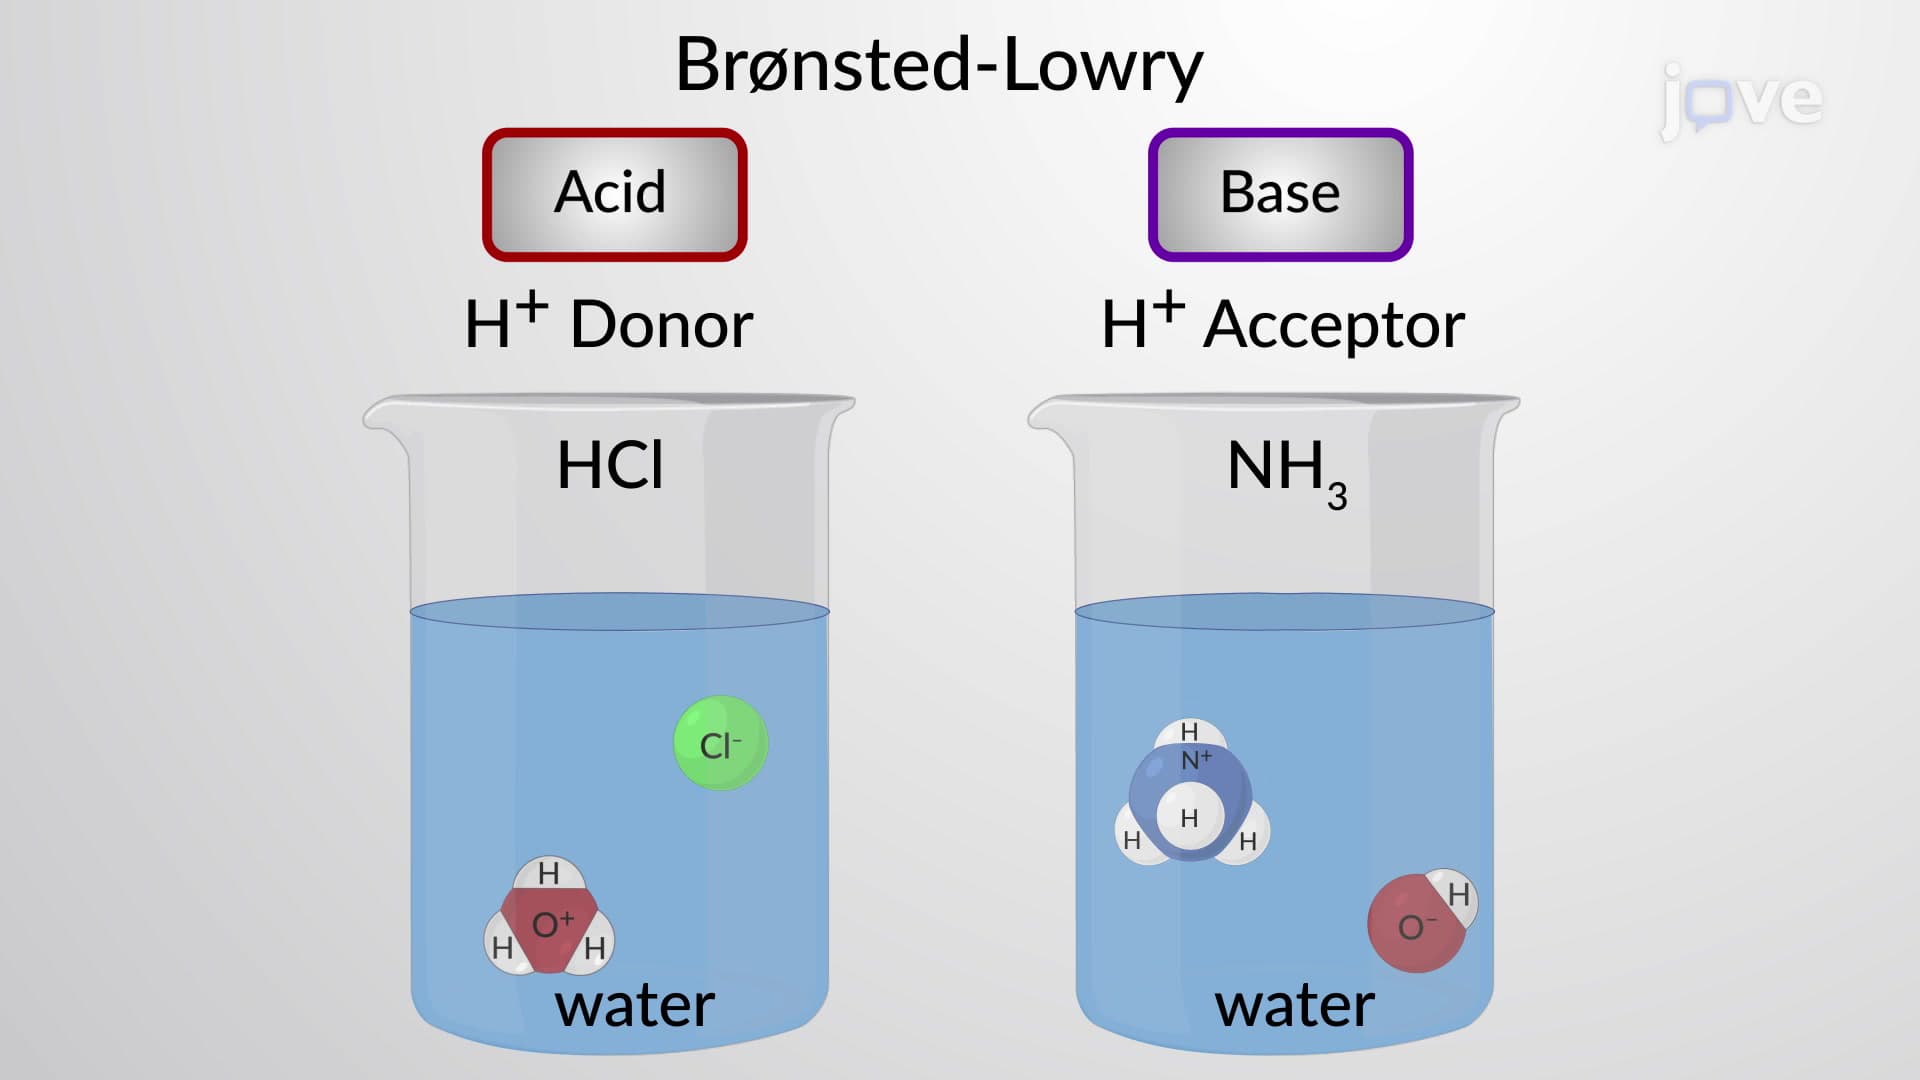
Bronsted-Lowry Acids and Bases
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...