Related Experiment Video
Updated: Jul 8, 2026


Invasive Hemodynamic Characterization of the Portal-hypertensive Syndrome in Cirrhotic Rats
Published on: August 1, 2018
Fluid retention in cirrhosis: pathophysiology and management
A Kashani1, C Landaverde, V Medici
1Department of Internal Medicine, Division of Gastronterology and Hepatology, University of California, Davis Medical Center, 4150 V Street - PSSB 3500, Sacramento, CA 95817, USA.

Insights
Ascites, a common cirrhosis complication, involves fluid buildup due to circulatory changes. Management focuses on sodium balance, with interventions for severe cases and related infections like spontaneous bacterial peritonitis.
Area of Science:
- Hepatology
- Gastroenterology
- Internal Medicine
Background:
- Ascites is the most frequent complication of cirrhosis, affecting approximately 50% of patients within 10 years.
- It serves as a critical prognostic indicator, with 1- and 5-year survival rates of 85% and 56%, respectively.
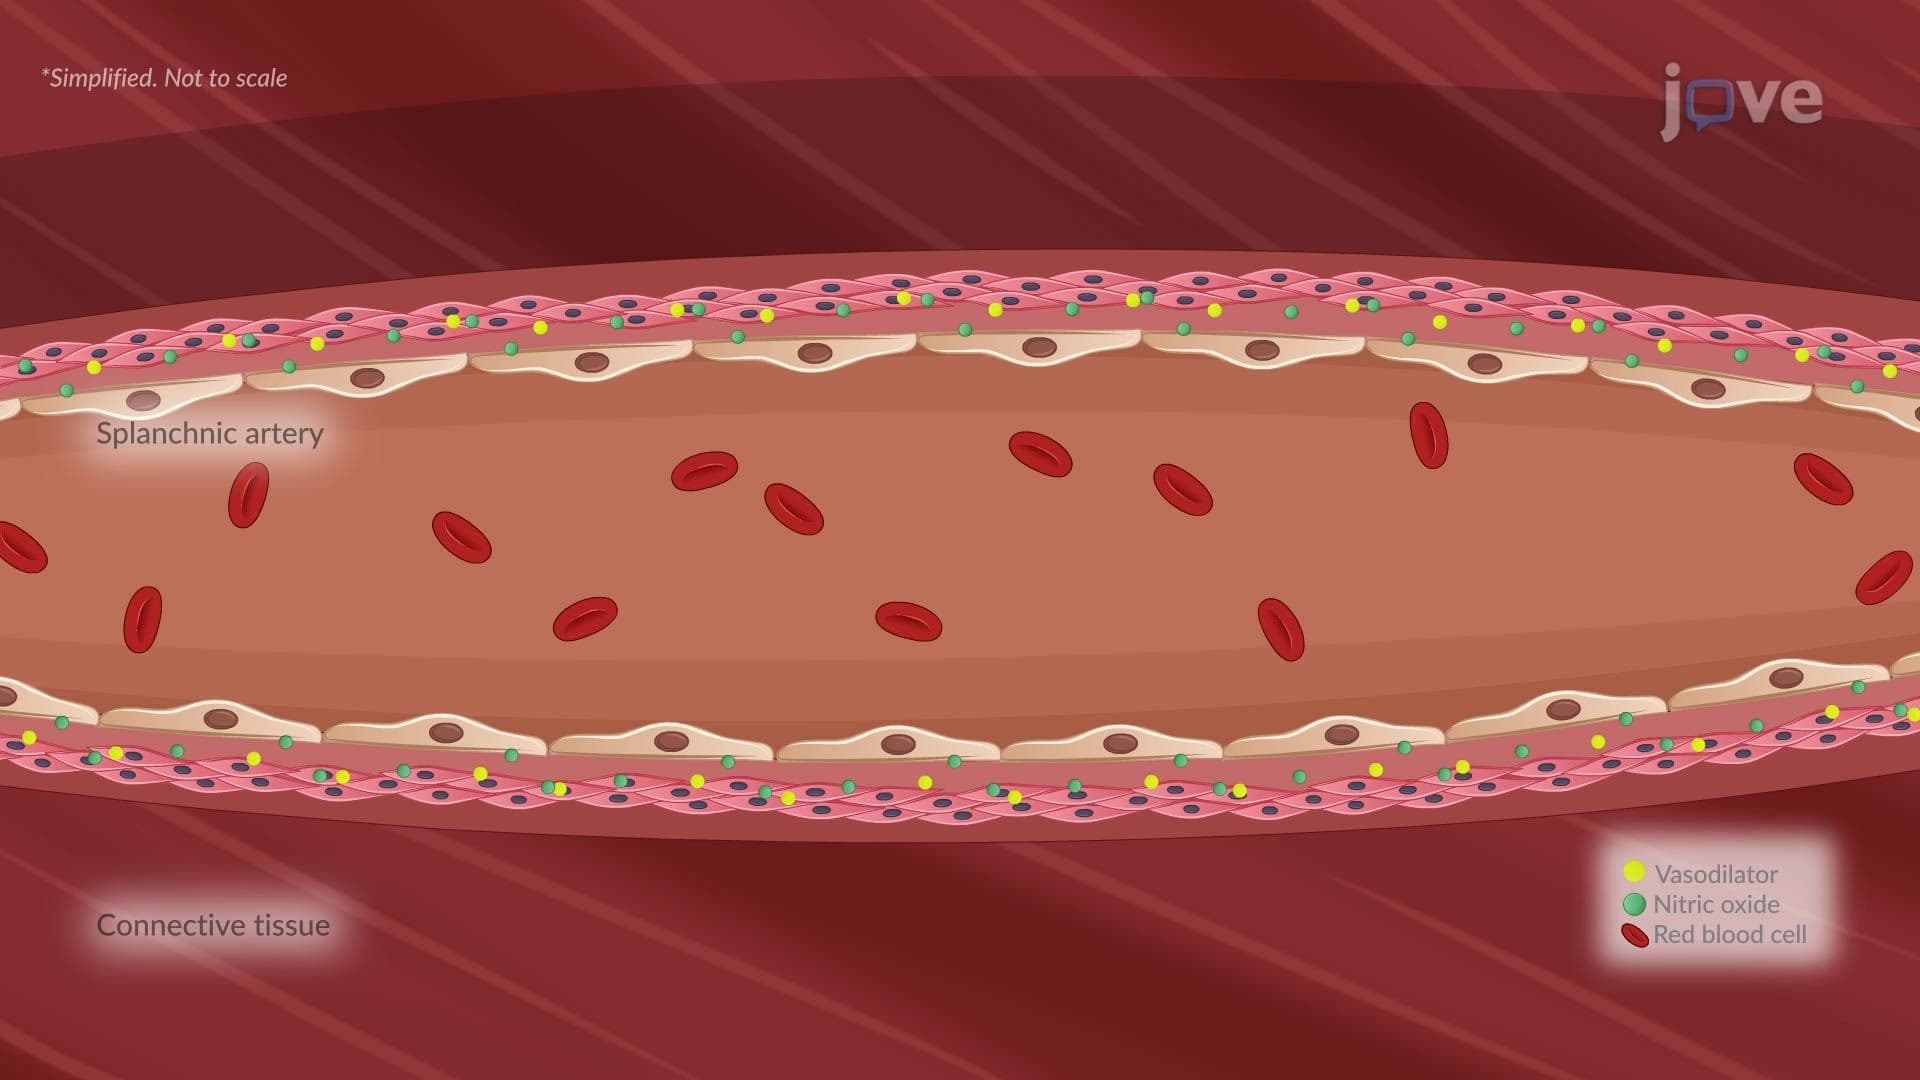
- The leading theory implicates peripheral arterial vasodilation, leading to circulatory underfilling and subsequent sodium/water retention.
Purpose of the Study:
- To review the pathophysiology of ascites formation in cirrhosis.
- To outline current therapeutic strategies for managing ascites and its complications.
- To discuss the role of liver transplantation in end-stage liver disease.
Main Methods:
- Review of current medical literature on cirrhosis and ascites.
- Analysis of pathophysiological mechanisms.
- Summary of established and emerging treatment modalities.
Main Results:
- Ascites develops from a complex interplay of circulatory dysfunction and hormonal activation.
- Therapeutic approaches include dietary modifications, diuretics, paracentesis, and shunting procedures.
- Associated complications like spontaneous bacterial peritonitis and hepatorenal syndrome require specific management.
Conclusions:
- Ascites management is multifaceted, aiming to reduce fluid overload and address complications.
- Early diagnosis and appropriate treatment are crucial for improving patient outcomes.
- Liver transplantation remains the definitive treatment for end-stage liver disease with refractory ascites.
Abstract:
Accumulation of fluid as ascites is the most common complication of cirrhosis. This is occurring in about 50% of patients within 10 years of the diagnosis of cirrhosis. It is a prognostic sign with 1-year and 5-year survival of 85% and 56%, respectively. The most acceptable theory for ascites formation is peripheral arterial vasodilation leading to underfilling of circulatory volume. This triggers the baroreceptor-mediated activation of renin-angiotensin-aldosterone system, sympathetic nervous system and nonosmotic release of vasopressin to restore circulatory integrity. The result is an avid sodium and water retention, identified as a preascitic state. This condition will evolve in overt fluid retention and ascites, as the liver disease progresses. Once ascites is present, most therapeutic modalities are directed on maintaining negative sodium balance, including salt restriction, bed rest and diuretics. Paracentesis and albumin infusion is applied to tense ascites. Transjugular intrahepatic portosystemic shunt is considered for refractory ascites. With worsening of liver disease, fluid retention is associated with other complications; such as spontaneous bacterial peritonitis. This is a primary infection of ascitic fluid caused by organisms originating from large intestinal normal flora. Diagnostic paracentesis and antibiotic therapy plus prophylactic regimen are mandatory. Hepatorenal syndrome is a state of functional renal failure in the setting of low cardiac output and impaired renal perfusion. Its management is based on drugs that restore normal renal blood flow through peripheral arterial and splanchnic vasoconstriction, renal vasodilation and/or plasma volume expansion. However, the definitive treatment is liver transplantation.

Related Concept Videos
 01:24
Cirrhosis II: Pathophysiology
 01:23
Cirrhosis I: Introduction
 01:19
Ascites
 01:22
Portal Hypertension
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...