Related Experiment Video
Updated: Jul 8, 2026


Diagnosis of Hirschsprung's Disease by Immunostaining Rectal Suction Biopsies for Calretinin, S100 Protein and Protein Gene Product 9.5
Published on: April 26, 2019
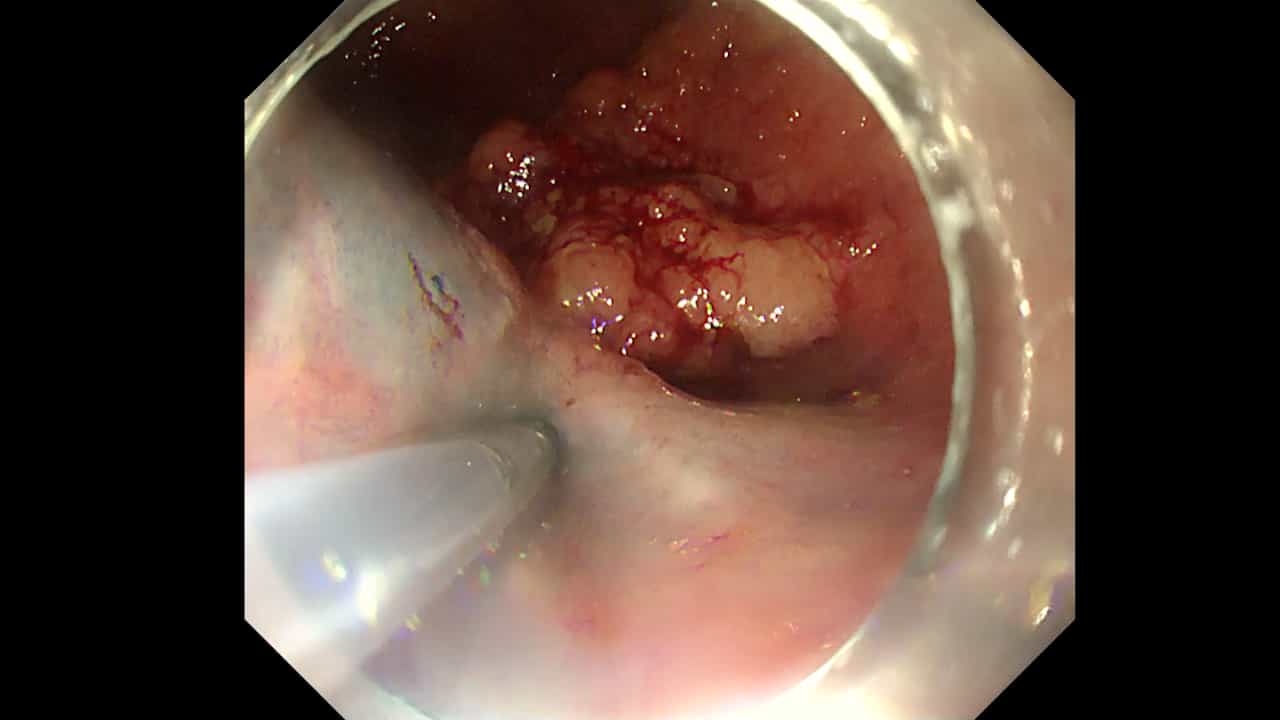
Solitary rectal ulcer syndrome in children
1University Hospital Lewisham, National Health Service Trust, London, UK. ali.keshtgar@uhl.nhs.uk

Insights
Solitary rectal ulcer syndrome (SRUS) in children causes rectal bleeding and pain. Treatment includes conservative measures, but surgery or botulinum toxin may be needed for severe cases.
Area of Science:
- Pediatric Gastroenterology
- Colorectal Surgery
Background:
- Solitary rectal ulcer syndrome (SRUS) is a rare pediatric condition.
- Symptoms include rectal bleeding, mucus passage, straining, tenesmus, pain, and rectal prolapse.
- Etiology is unclear, likely involving rectal ischemia and pelvic floor dysfunction.
Purpose of the Study:
- To review the presentation, etiology, and management of SRUS in children.
- To explore potential therapeutic roles for interventions like botulinum toxin injection.
Main Methods:
- Review of clinical presentation and diagnostic findings.
- Analysis of treatment outcomes for conservative and surgical interventions.
- Exploration of the pathophysiology involving paradoxical muscle contractions.
Main Results:
- Conservative treatments (diet, laxatives, biofeedback) are often effective for constipation.
- Refractory cases may require rectal ulcer excision or surgery for prolapse.
- Botulinum toxin injection is a potential treatment for associated muscle dysfunction.
Conclusions:
- SRUS management requires a multi-faceted approach.
- Conservative measures are first-line treatments.
- Further research into novel therapies like botulinum toxin is warranted for pediatric SRUS.
Abstract:
SRUS is a rare condition in children, which usually presents with a symptom complex of rectal bleeding, passage of mucus and straining on defecation, tenesmus, perineal and abdominal pain, sensation of incomplete defecation, constipation and rectal prolapse. The underlying etiology of SRUS is not fully understood but it is likely to be secondary to ischemic changes in the rectum associated with paradoxical contraction of pelvic floor and external anal sphincter muscles and rectal prolapse. Conservative measures like high intake of fluids and fibers, laxatives, biofeedback and behavior modification therapy may be beneficial for treatment of constipation. Excision of rectal ulcer and surgery of overt rectal prolapse, however, may be required in refractory cases not responding to conservative treatments. A therapeutic role for botulinum toxin injection into the external anal sphincter for treatment of SRUS associated with constipation and paradoxical contraction of pelvic floor and external anal sphincter muscles in children, may exist.
Related Concept Videos
 01:20
Inflammatory Bowel Disease II: Ulcerative Colitis
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:26
Inflammatory Bowel Disease I: Introduction
 01:27
Peptic Ulcer