Related Experiment Video
Updated: Jul 8, 2026
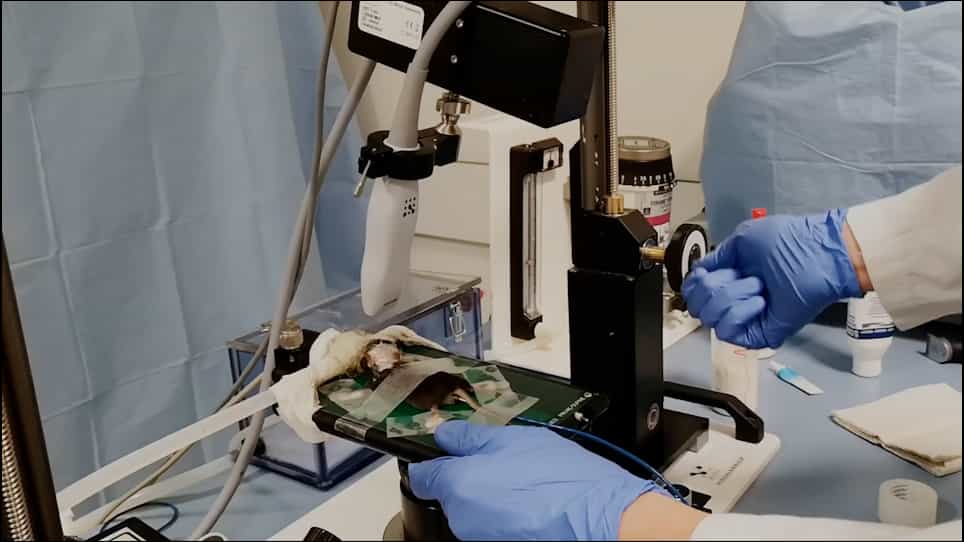

Analysis of Cerebral Vasospasm in a Murine Model of Subarachnoid Hemorrhage with High Frequency Transcranial Duplex Ultrasound
Published on: June 3, 2021
The burden of the systemic inflammatory response predicts vasospasm and outcome after subarachnoid hemorrhage
Rajat Dhar1, Michael N Diringer
1Neurology/Neurosurgery Intensive Care Unit, Department of Neurology and Neurological Surgery, Washington University School of Medicine, 660 S. Euclid Ave, Campus Box 8111, Saint Louis, MO 63110, USA. dharr@neuro.wustl.edu

Introduction:
Subarachnoid hemorrhage (SAH) can trigger immune activation sufficient to induce the systemic inflammatory response syndrome (SIRS). This may promote both extra-cerebral organ dysfunction and delayed cerebral ischemia, contributing to worse outcome. We ascertained the frequency and predictors of SIRS after spontaneous SAH, and determined whether degree of early systemic inflammation predicted the occurrence of vasospasm and clinical outcome.
Methods:
Retrospective analysis of prospectively collected data on 276 consecutive patients admitted to a neurosciences intensive care unit with acute, non-traumatic SAH between 2002 and 2005. A daily SIRS score was derived by summing the number of variables meeting standard criteria (HR >90, RR >20, Temperature >38 degrees C, or <36 degrees C, WBC count <4,000 or >12,000). SIRS was considered present if two or more criteria were met, while SIRS burden over the first four days was calculated by averaging daily scores. Regression modeling was used to determine the relationship among SIRS burden (after controlling for confounders including infection, surgery, and corticosteroid use), symptomatic vasospasm, and outcome, determined by hospital disposition.
Results:
SIRS was present in over half the patients on admission and developed in 85% within the first four days. Factors associated with SIRS included poor clinical grade, thick cisternal blood, larger aneurysm size, higher admission blood pressure, and surgery for aneurysm clipping. Higher SIRS burden was independently associated with death or discharge to nursing home (OR 2.20/point, 95% CI 1.27-3.81). All of those developing clinical vasospasm had evidence of SIRS, with greater SIRS burden predicting increased risk for delayed ischemic neurological deficits (OR 1.77/point, 95% CI 1.12-2.80).
Conclusions:
Systemic inflammatory activation is common after SAH even in the absence of infection; it is more frequent in those with more severe hemorrhage and in those who undergo surgical clipping. Higher burden of SIRS in the initial four days independently predicts symptomatic vasospasm and is associated with worse outcome.

Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:25
Acute Inflammation III: Local and Systemic Effects
 01:22
Cerebral Edema ll: Pathophysiology
 01:26
Bacterial Meningitis II: Pathophysiology
 01:16
Vascular Spasm
 01:17
Hemorrhagic Stroke l: Introduction