Related Experiment Video
Updated: Jul 8, 2026


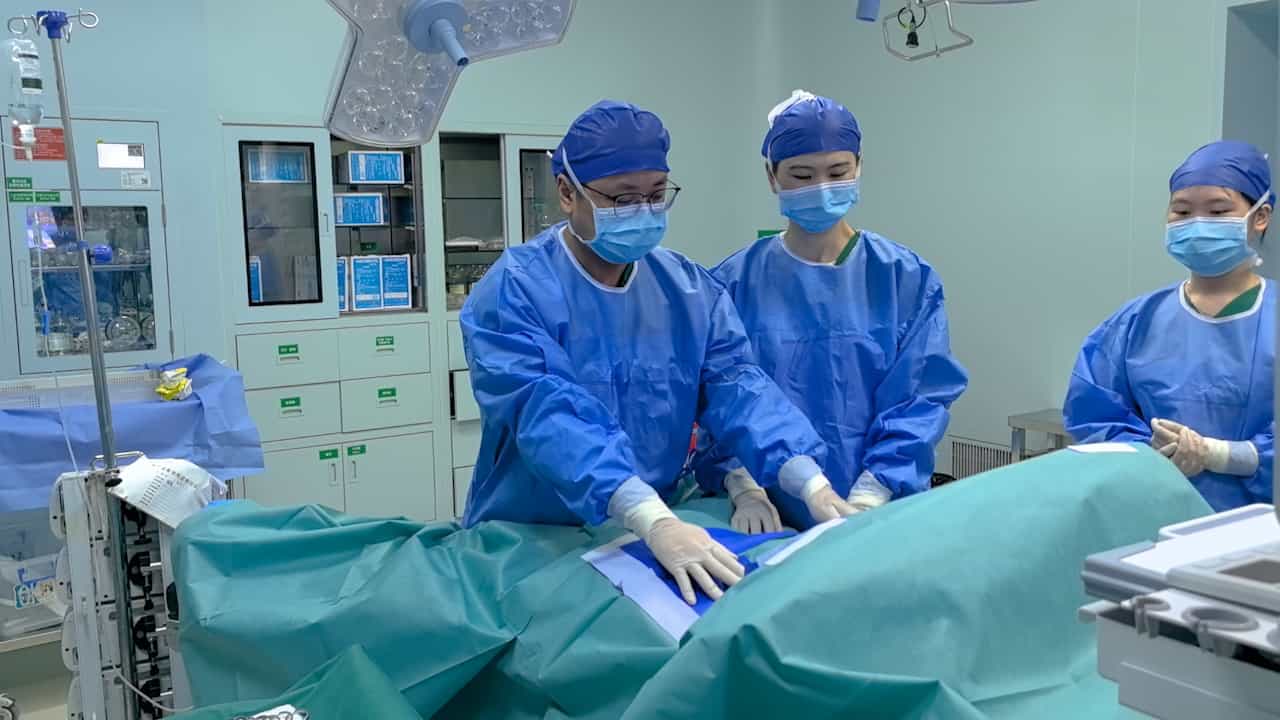
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Long-term results of laryngotracheal resection for benign stenosis
Antonio D'Andrilli1, Anna Maria Ciccone, Federico Venuta
1Department of Thoracic Surgery, University of Rome La Sapienza, Sant'Andrea Hospital, Rome, Italy. adandrilli@hotmail.com

Objective:
We report the long-term results of our 16-year experience with laryngotracheal resection for benign stenosis.
Methods:
Between 1991 and 2006, 35 consecutive patients (19 males, 16 females) underwent laryngotracheal resection for subglottic postintubation (32) or idiopathic (3) stenosis. Mean age was 43 years (range 14-71). At the time of surgery 13 patients presented with tracheostomy and 7 with a Dumon stent. The upper limit of the stenosis was from 0.6 to 1.5 cm below the vocal cords. The length of airway resection ranged between 1.5 and 6 cm. Suprahyoid release was performed in two patients and pericardial release in one. Nine patients had psychiatric and/or neurological post-coma disorders. Mean follow-up is over 5 years (61 months; range 3-194).
Results:
There was no perioperative mortality. Thirty patients (85.7%) had excellent or good anatomic and functional results. Four patients (11.4%) presented restenosis at a distance of 25-110 days from the operation. Restenosis was successfully treated by endoscopic procedures in all four patients. One patient (2.9%) presented anastomotic dehiscence that required temporary tracheostomy closed after 1 year with no sequelae. Three patients (8.4%) had wound infection. Long-term follow-up was uneventful also in patients who had early complications.
Conclusions:
Long-term follow-up confirms that laryngotracheal resection is the definitive curative treatment for benign subglottic stenosis. Surgical complications can be successfully managed by non-operative procedures. Despite the occurrence of early complications, excellent and stable results can still be obtained at long term.

Related Concept Videos
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes: