Related Experiment Video
Updated: Jul 8, 2026

An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Ultra-low-dose continuous combined estradiol and norethisterone acetate: improved bleeding profile in postmenopausal
D W Sturdee1, D F Archer, V Rakov
1Department of Obstetrics and Gynecology, Solihull Hospital, Solihull, West Midlands, UK.

Objective:
To evaluate the effect of two ultra-low-dose hormone treatments containing estradiol (E2) 0.5 mg and norethisterone acetate (NETA) 0.1 or 0.25 mg on the endometrium and bleeding.
Methods:
A prospective, randomized, placebo-controlled trial of 6 months. Local Ethics Committee approval and informed consent were obtained prior to initiation and enrollment. Out of 577 postmenopausal women randomized, 575 took E2/NETA 0.1 (n = 194), or E2/NETA 0.25 (n = 181) or placebo (n = 200). Endometrial bleeding was monitored by daily diary cards and endometrial thickness by transvaginal ultrasound at baseline and on completion. An endometrial biopsy was obtained when indicated clinically.
Results:
In months 1-6, the amenorrhea rates with E2/NETA 0.1 were 89%, 89%, 86%, 85%, 89% and 89%, respectively and the no-bleeding rates were correspondingly high: 95%, 94%, 93%, 90%, 95% and 95%. The amenorrhea and spotting-only rates were similar with both ultra-low-dose combinations. The withdrawal rates due to bleeding were very low and the same in all three treatment arms (n = 1; 1%). There was a slight increase in the mean endometrial thickness in all three groups, which remained less than 5 mm.
Conclusions:
The ultra-low-dose combination of E2/NETA 0.1 or E2/NETA 0.25 resulted in a high incidence of amenorrhea and no bleeding in postmenopausal women, and a corresponding high level of compliance. Overall, there was no significant change in mean endometrial thickness during 6 months of active treatment or placebo.

Related Concept Videos
 01:21
Intrauterine Drug Delivery Systems
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:26
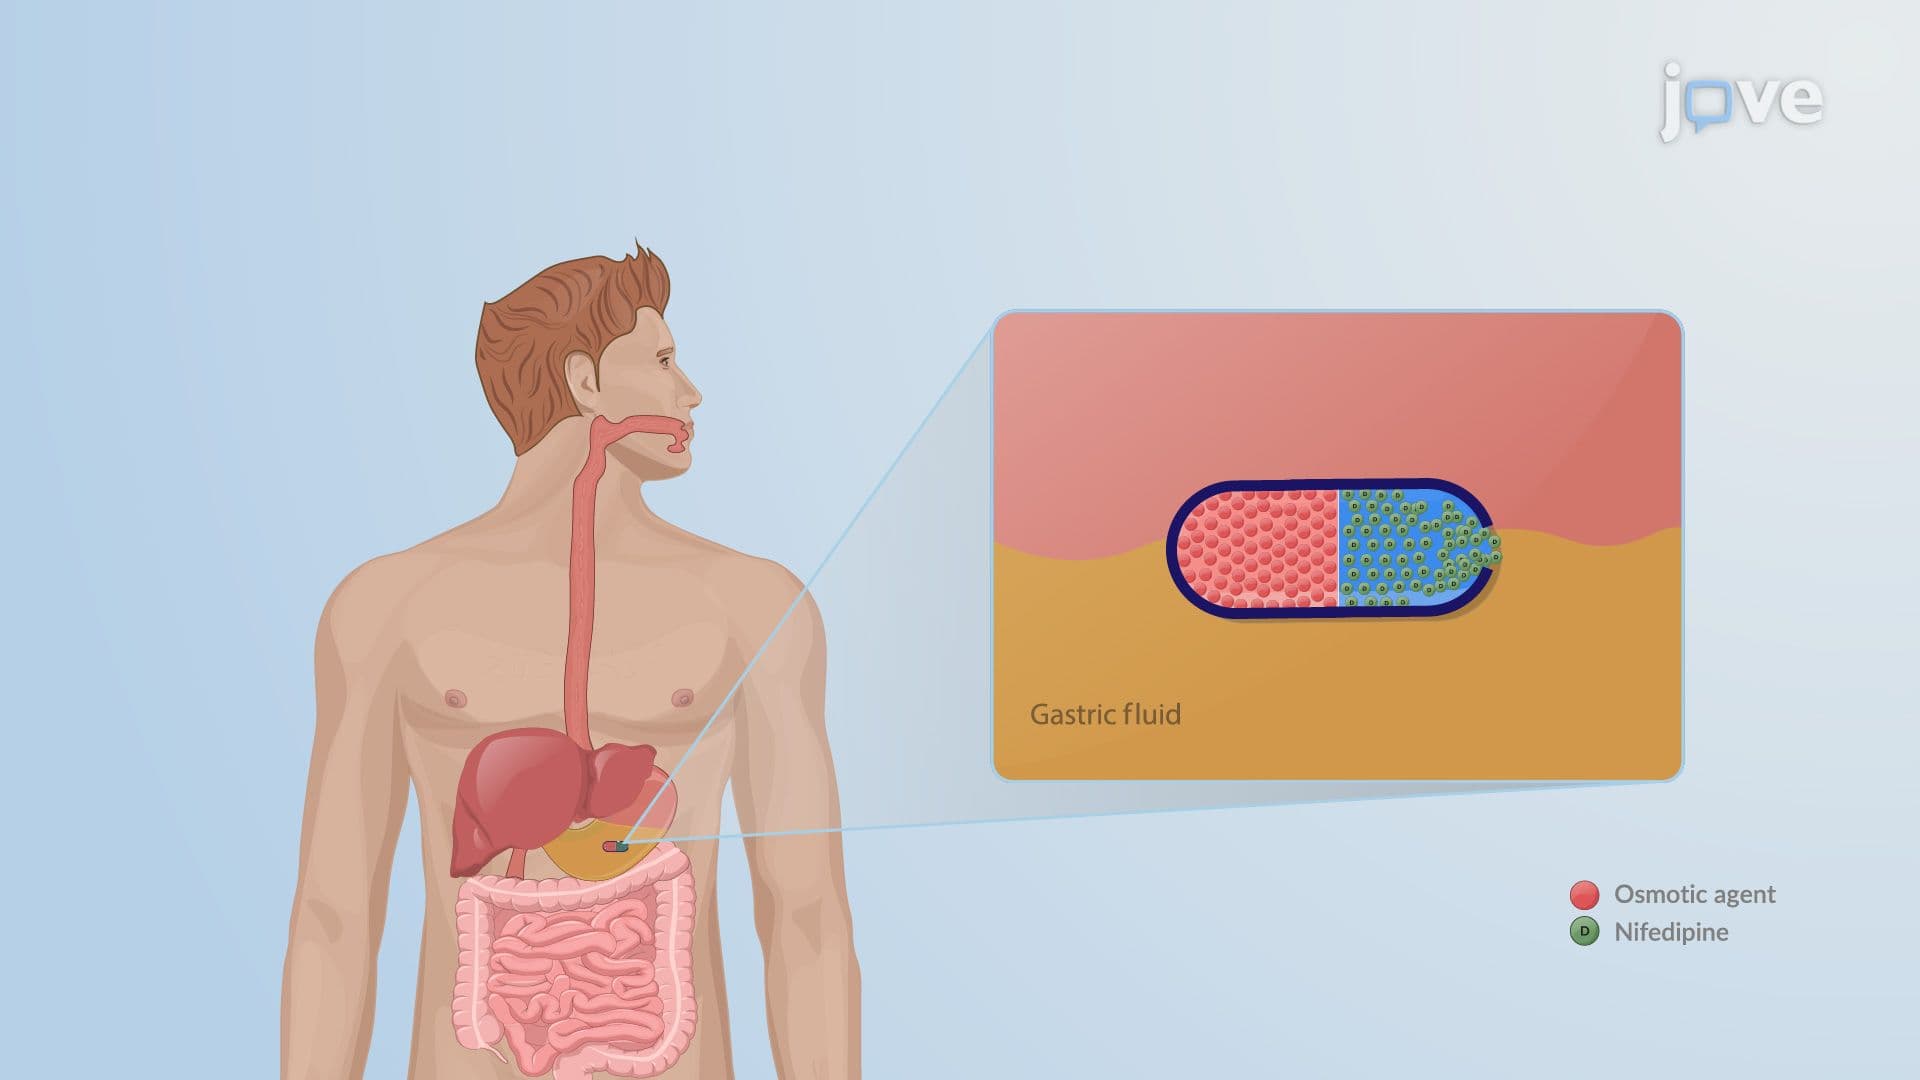
Oral Drug Delivery Systems: Continuous-Release Systems