Related Experiment Video
Updated: Jul 8, 2026
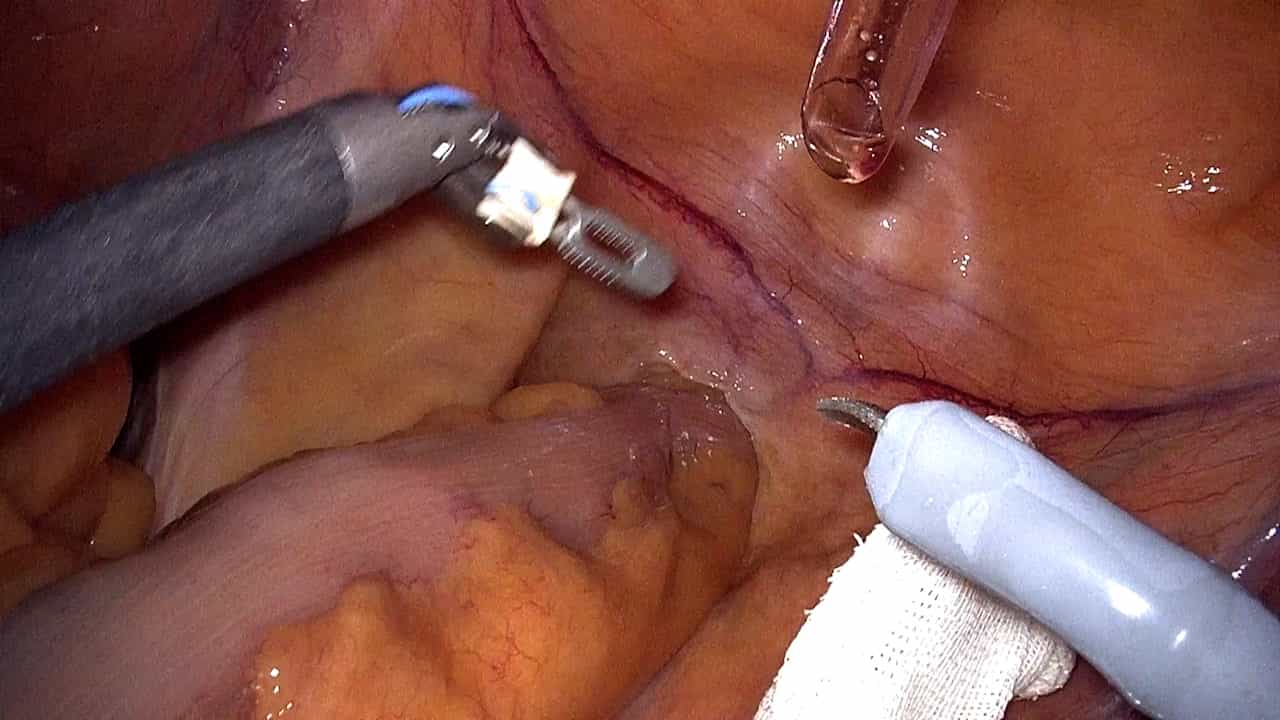

Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
Midterm postoperative clinicoradiologic analysis of surgery for high/intermediate-type imperforate anus: prospective
Chizue Ichijo1, Kazuhiro Kaneyama, Yutaka Hayashi
1Department of Pediatric General and Urogenital Surgery, Juntendo University School of Medicine, Tokyo 113-8421, Japan.

Purpose:
The objective of this study is to analyze the outcome of surgery for high/intermediate-type imperforate anus using anal endosonography (AES), magnetic resonance imaging (MRI), and a continence evaluation questionnaire (CEQ).
Methods:
In this study, 24 cases of high/intermediate-type imperforate anus were studied. Fifteen of 24 had Georgeson's laparoscopy-assisted anorectoplasty (GLA), and 9 of 24 had Pena's posterior sagittal anorectoplasty (PPA). All subjects had AES and MRI postoperatively. On AES, differences in thickness of the external sphincter (ES) and puborectalis (PR) at 3 and 9 o'clock were compared, and if pull-through colon was central, AES was 0. On MRI, differences in thickness were analyzed semiquantitatively and scored; if muscles were of even thickness, the score was 0; slight difference was 1, and marked difference was 2. A 5-parameter CEQ questionnaire (maximum score, 10) was administered to 16 of 24 subjects followed up for more than 3 years (9 GLA, 7 PPA). Surgical stress was assessed using mean febrile period, duration of raised white blood cell count, and peak C-reactive protein level.
Results:
Mean age at surgery and mean postoperative period for both groups were not statistically different. There were no differences in mean muscle thickness for ES or PR on AES according to procedure (ES: GLA = 0.19 +/- 0.15 mm, PPA = 0.16 +/- 0.09 mm, P = .59; PR: GLA = 0.19 +/- 0.19 mm, PPA = 0.22 +/- 0.15 mm, P = .69). Magnetic resonance imaging scores were also not significantly different according to procedure (GLA: 0.77 +/- 0.83; PPA: 0.75 +/- 0.50, P = .97). When CEQ were compared annually, scores for GLA were generally higher throughout the study but only statistically significant at 3 and 4 years (P < .05). Differences in parameters of surgical stress were not significant.
Conclusion:
Although there were no differences in muscle thickness and parameters of surgical stress observed according to technique, GLA would appear to provide better outcome based on CEQ scores.

Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: