Related Experiment Video
Updated: Jul 8, 2026
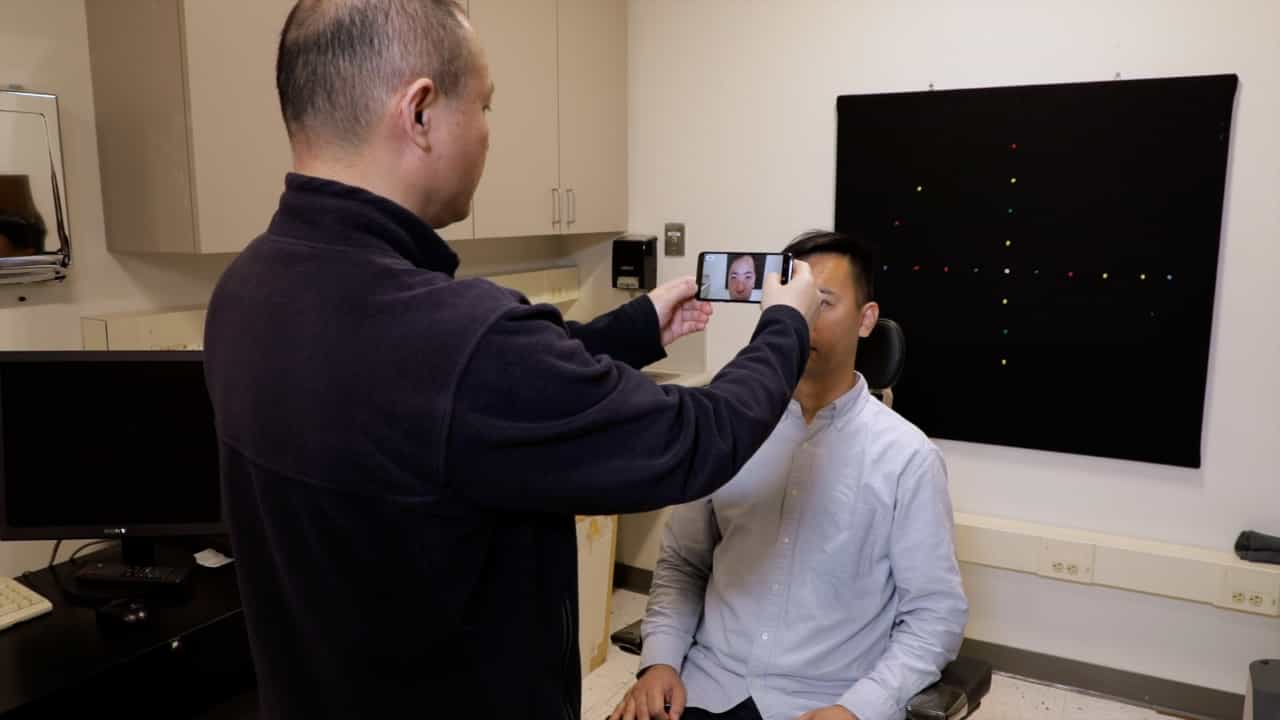
Subjective Refraction Test Using a Smartphone for Vision Screening
Published on: October 18, 2024
Spectacle prescribing in childhood: a survey of hospital optometrists
1Optometry Department, Oxford Eye Hospital, West Wing, John Radcliffe Hospital, Headley Way, Oxford OX3 9DU, UK. janefarbrother@btinternet.com

Insights
Hospital optometrists prescribe lower levels of myopia and hyperopia correction for young children compared to other guidelines. However, there is agreement on managing astigmatism and prescribing partial corrections for hyperopia.
Area of Science:
- Pediatric Optometry
- Ophthalmology
- Vision Science
Background:
- Spectacle prescribing practices for infants and young children are crucial for visual development.
- Understanding current hospital optometrists' approaches is essential for evidence-based care.
Purpose of the Study:
- To determine the spectacle prescribing practices of hospital optometrists for infants and young children.
- To compare these practices with established guidelines.
Main Methods:
- A two-part survey was distributed to hospital optometrists at the 2006 Annual Hospital Optometrists Conference.
- The survey focused on prescribing spectacles for non-strabismic children aged one to five years.
Main Results:
- 93 optometrists responded, indicating thresholds for spectacle prescription.
- Prescribing thresholds for hyperopia, myopia, anisohyperopia, and astigmatism varied by age.
- Partial correction was common for hyperopic children (3-4 years) without strabismus.
Conclusions:
- Hospital optometrists' recommendations for myopia and hyperopia correction in young children were generally lower than those from the American Association of Pediatric Ophthalmology and Strabismus and the American Academy of Ophthalmology.
- There was consensus on managing astigmatism and anisometropia.
- Agreement existed on providing partial corrections for hyperopic children without strabismus.
Background/Aims:
To determine the spectacle prescribing practices of hospital optometrists for infants and young children.
Methods:
A two-part survey relating to the prescribing of spectacles for non-strabismic children aged one to five years was distributed to all delegates at the 2006 Annual Hospital Optometrists Conference.
Results:
A total of 93 of the 149 optometrists returned the survey. The threshold level at which 50% of the respondents would consider prescribing spectacles in non-strabismic children at ages one, three and five years were for hyperopia 4.50 DS, 3.00 DS and 2.50 DS, for myopia -3.00 DS, -1.50 DS and -1.00 DS, for anisohyperopia 2.00 DS, 1.00 DS and 1.00 DS and for non-oblique astigmatism 2.50 DC, 1.50 DC and 1.00 DC. For hyperopic children in the three to four-year age group at least two thirds of those recommending spectacles would give a partial correction, with an average reduction of 1.69 DS from the cycloplegic refraction.
Conclusions:
Delegates of the Hospital Optometrists Annual Conference recommend spectacles to correct lower levels, on average, of myopia and hyperopia in young children than members of the American Association of Pediatric Ophthalmology and Strabismus or those suggested in the American Academy of Ophthalmology preferred practice patterns guidelines. There is, however, broad agreement for the management of astigmatism and anisometropia and the prescription of partial corrections in hyperopic children in the absence of strabismus.
Related Concept Videos
 01:17
Accessory Structures of the Eye
 01:22
Photoreceptors and Visual Pathways
 01:25
Glaucoma: Overview