Related Experiment Video
Updated: Jul 8, 2026
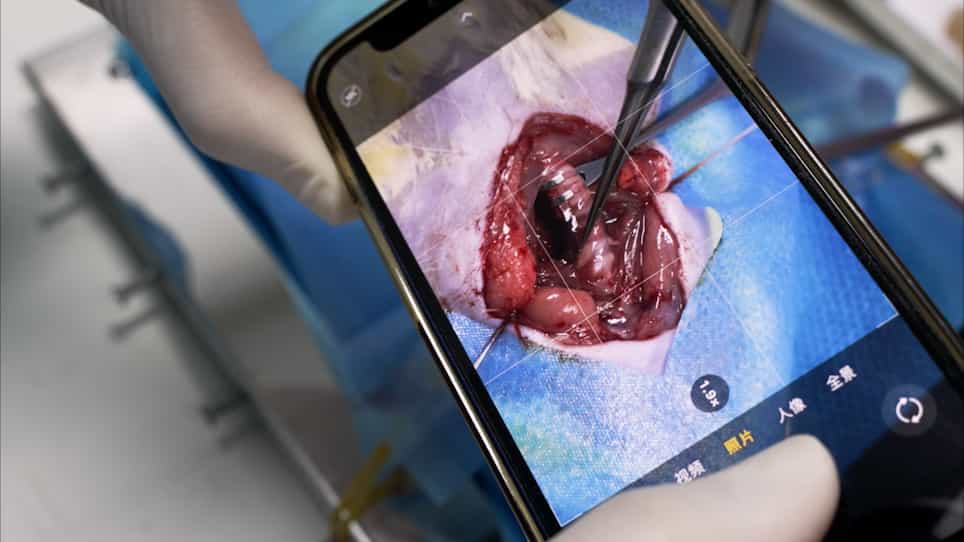

Establishment of a Simple and Effective Rat Model for Intraoperative Parathyroid Gland Imaging
Published on: August 17, 2022
Primary hyperparathyroidism in neonates and childhood. The French experience (1984-2004)
1Department of Pediatrics and Reference Centre of Rare Calcium and Phosphorus Diseases, University Hospital Charles Nicolle, Rouen, France. eric.mallet@chu-rouen.fr

Insights
Primary hyperparathyroidism (HP1) in children is rare but severe, often presenting with symptoms and kidney stones. Early diagnosis and molecular testing, especially for neonatal cases and potential Multiple Endocrine Neoplasias, are crucial for effective management.
Area of Science:
- Pediatric Endocrinology
- Calcium Metabolism Disorders
- Surgical Endocrinology
Background:
- Primary hyperparathyroidism (HP1) in childhood is considered rare, with limited data on its incidence and characteristics.
- The availability of intact parathormone (iPTH) assays has improved diagnostic capabilities.
Purpose of the Study:
- To determine the incidence and characteristics of childhood HP1.
- To evaluate diagnostic and management strategies for pediatric HP1.
Main Methods:
- A retrospective study collected 55 cases of HP1 in children and adolescents over 20 years (1984-2004) across France.
- Utilized intact parathormone (iPTH) radioimmunoassay, ultrasonography, scintigraphy, and molecular biology tests.
Main Results:
- 55 cases were identified, with 83% symptomatic and 43% having nephrolithiasis, linked to high calcium and iPTH levels.
- Surgery was performed on 44 children/adolescents, revealing 29 adenomas and 11 hyperplasias; two cases of Multiple Endocrine Neoplasias (MENs) were found.
- Neonatal management shifted towards medical treatment (e.g., diphosphonates) following CaSR mutation identification.
Conclusions:
- Childhood HP1 is a rare but severe condition requiring careful management.
- Molecular biology tests are valuable for identifying neonatal CaSR mutations and pre-surgical screening for MEN mutations in children.
Objectives:
Primary hyperparathyroidism (HP1) in childhood is thought to be extremely rare. Its exact incidence remains unknown, as do the characteristics of HP1. A retrospective study collection was conducted on cases supplied by members of the Working Group on Calcium Metabolism throughout France over a 20-year period (1984-2004), since the availability of the intact parathormone (iPTH) radioimmunoassay.
Results:
55 cases were collected of which 11 were neonates. Among the 44 children and adolescents, there were 18 male and 26 female patients, ranging in age from 6 to 18 (mean 13) years. 83% were symptomatic and 43% had nephrolithiasis. Symptoms were associated with high serum calcium and inappropriate iPTH levels. Ultrasonography and technetium-labelled methoxyisobutylisonitrile scintigraphy are useful tools for the preoperative localization of adenomas, particularly in adolescents. Intraoperative iPTH assays are effective in minimizing invasive parathyroidectomy. All patients, except neonates, underwent surgery: 29 adenomas and 11 hyperplasias were found. Two multiple endocrine neoplasias (MENs) were subsequently discovered. Since the calcium-sensing receptor (CaSR) mutation was reported, the form of management in neonates has become more medical (intravenous diphosphonates) than surgical. On follow-up no recurrence was observed except for MEN.
Conclusion:
These national results reflect HP1 epidemiology. HP1 is a rare entity and appears to be a severe disease in terms of symptoms with regard to management. The use of molecular biology tests could be useful not only in neonatal cases (CaSR mutation) but also prior to surgery in children (MEN mutation).

Related Concept Videos
 00:59
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:27
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:24
Graves Disease II: Pathophysiology