Related Experiment Videos
Congenital osseous anomalies of the upper cervical spine
Harish S Hosalkar1, Wudbhav N Sankar, Brian P D Wills
1Division of Orthopaedic Surgery, 2nd Floor Wood Building, The Children's Hospital of Philadelphia, Philadelphia, PA 19104, USA.

Insights
Congenital upper cervical spine anomalies in children can lead to instability and neurological issues. Early evaluation and advanced imaging are crucial for identifying risks and potential compromise.
Area of Science:
- Pediatric Orthopedics
- Neurosurgery
- Developmental Anatomy
Background:
- The upper cervical spine's unique developmental anatomy and biomechanics in children predispose them to risks.
- Congenital osseous anomalies in this region may increase the likelihood of neurological compromise due to instability or spinal cord encroachment.
Purpose of the Study:
- To evaluate congenital osseous anomalies of the upper cervical spine in children.
- To outline the risk of potential neurological compromise associated with these anomalies.
Main Methods:
- A double-cohort study reviewed medical records and imaging of children treated for upper cervical spine osseous anomalies (1988-2003).
- Patients were stratified by the presence or absence of associated syndromes.
- Anomalies involving the central nervous system, occipitocervical junction, and upper cervical osseous canal were assessed for sequelae like stenosis and instability.
Main Results:
- Sixty-eight children were identified, with 21 having syndromes and an average of 3.4 anomalies per patient.
- Clinical presentations included neck pain, neurological changes, and torticollis.
- Spinal instability and/or spinal cord encroachment were present in 40 patients, with 65% undergoing surgical intervention.
Conclusions:
- Thorough evaluation and advanced imaging of the upper cervical spine are recommended for children with related symptoms.
- Identifying associated anomalies and defining canal encroachment are key to managing potential neurological compromise.
Background:
The developmental anatomy and biomechanics of the upper cervical spine are unique in children. Congenital osseous anomalies in this region may be associated with an increased risk for subsequent neurological compromise from instability and/or spinal cord encroachment. We performed a double-cohort study evaluating congenital osseous anomalies of the upper cervical spine in children who presented with one or more clinical problems, and we attempted to outline the risk of possible neurological compromise.
Methods:
We reviewed the medical records and imaging studies of all children seen and treated for osseous anomalies of the upper cervical spine at our institution between 1988 and 2003. Patients were divided into two cohorts on the basis of the presence or absence of associated syndromes. Parameters reviewed included demographic data, clinical presentation, and imaging features. All anomalies involving the central nervous system, the occipitocervical junction, and the upper cervical osseous canal were included. Complicating sequelae such as canal stenosis, segmental instability, and other anomalies of the central nervous system and spine were identified.
Results:
Sixty-eight consecutive children were identified. Twenty-one patients had an underlying described syndrome. There were 234 osseous anomalies (average, 3.4 per patient). Three or more anomalies were noted in 79% of the patients. There was no significant difference in the mean number of anomalies (p = 0.80) or in the frequency of any specific anomaly (p > 0.20 for all) between syndromic and nonsyndromic patients. The variety of clinical presentations included neck pain (twenty-six patients), neurological changes (twenty-one patients), and torticollis and/or stiffness (twenty-one patients). Twenty-three patients had more than one complaint. Six patients had isolated spinal instability, twenty-eight had isolated spinal cord encroachment, and six had a combination of both. Forty-four (65%) of the sixty-eight patients underwent surgical decompression and/or arthrodesis principally focused from the foramen magnum to the second cervical vertebra.
Conclusions:
As a result of these findings, we recommend a thorough evaluation and advanced imaging of the upper cervical spine in all children who present with symptoms related to the upper cervical spine, to identify associated anomalies and further define the nature of canal encroachment including any potential for neurologic compromise.
Related Concept Videos
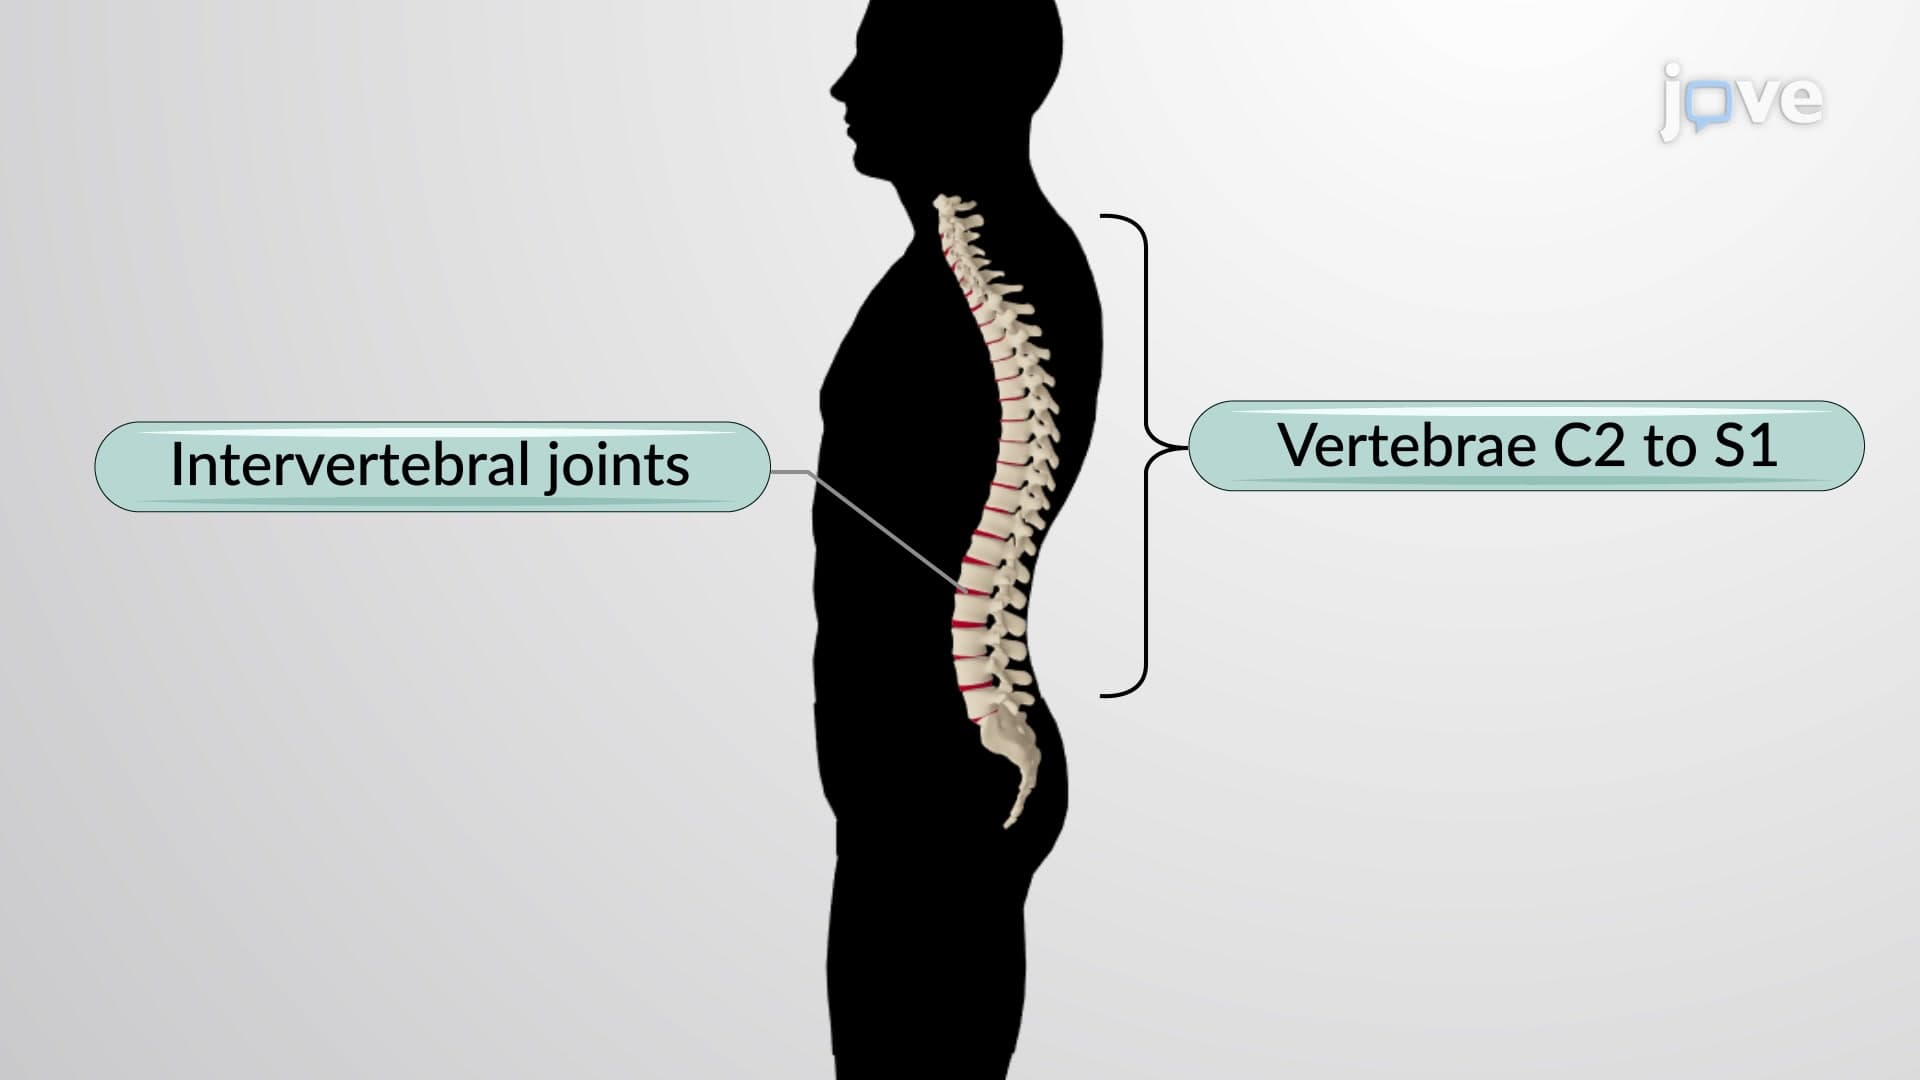 01:28
Articulations of the Vertebral Column
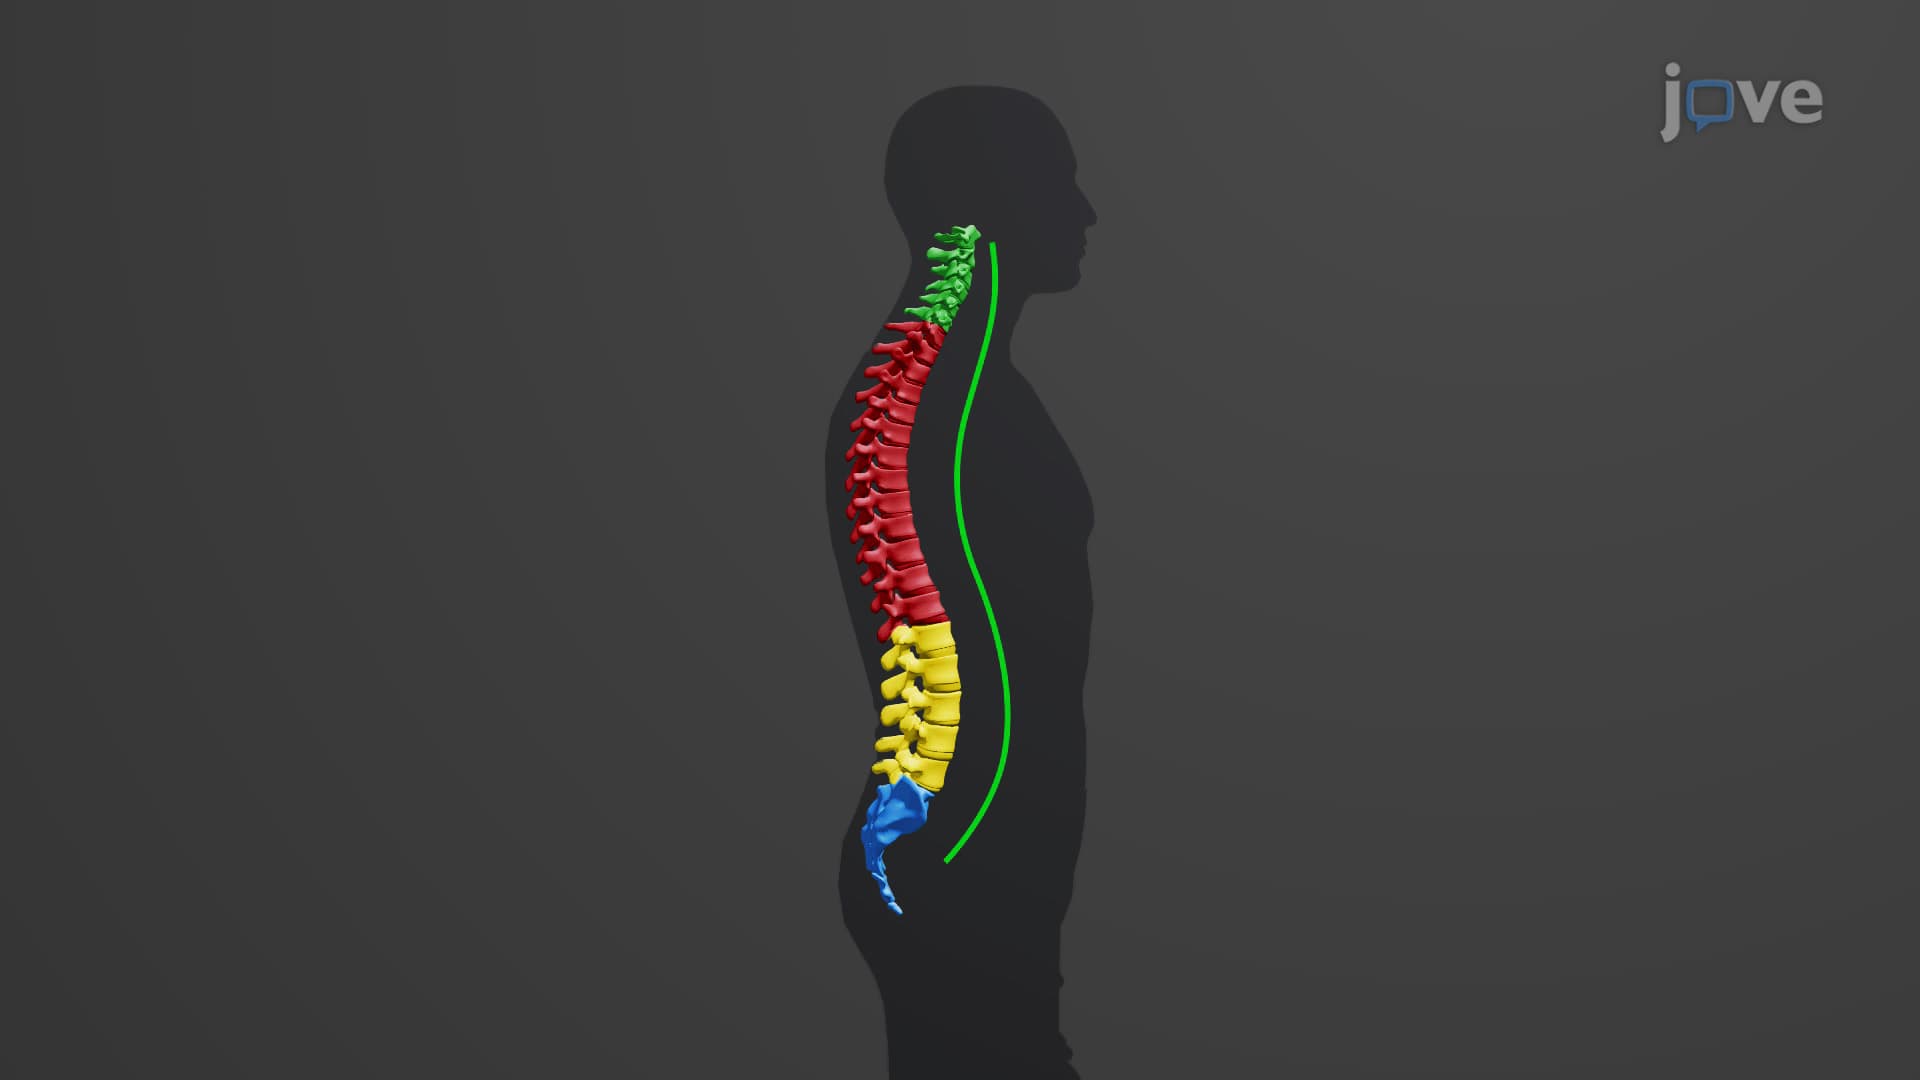 01:16
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:09
Overview of the Axial Skeleton
The axial skeleton of the adult...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:19
Bones of the Upper Limb: Humerus