Related Experiment Video
Updated: Jul 7, 2026
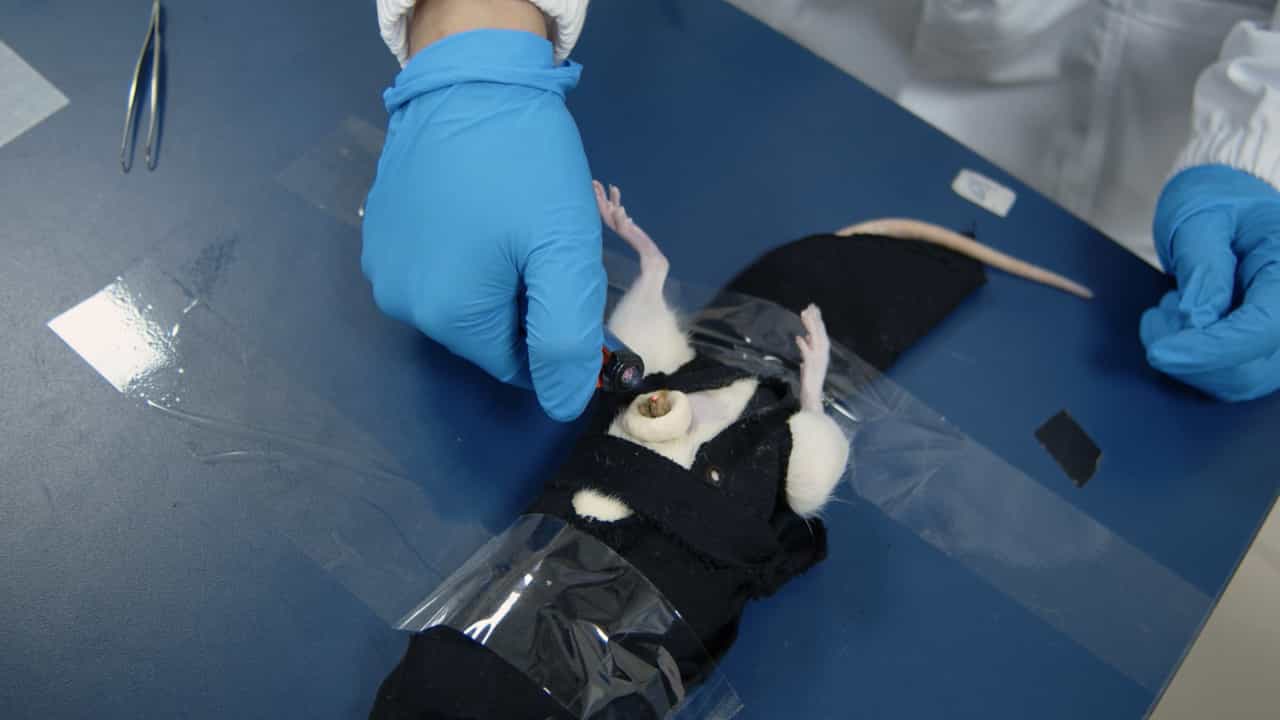

Herbs-Partitioned Moxibustion on the Navel in a Rat Model of Primary Dysmenorrhea with Cold Coagulation and Blood Stasis
Published on: October 4, 2024
Hormonal and volume dysregulation in women with premenstrual syndrome
Rimma Rosenfeld1, Dana Livne, Ori Nevo
1J. Recanati Autonomic Dysfunction Center, Medicine, Department of Obstetric and Gynecology, Rambam Medical Center and Faculty of Medicine, Technion-IIT, Haifa, Israel.

Premenstrual syndrome (PMS) presents with emotional and physical symptoms. Although the emotional symptoms have been extensively studied, the pathophysiology of the fluid-retention symptoms is not currently known. We tested the hypothesis that the fluid regulatory mechanisms are disturbed in PMS. Nine regularly menstruating women with PMS were compared with 9 healthy age-matched women. Hemodynamic parameters and upright plasma volume shift (extrapolated from changes in hematocrit), plasma renin activity (PRA), and plasma aldosterone and sex hormones were measured at different times during the menstrual cycle. During the early follicular and the midluteal phases, the plasma volume shift, supine and upright PRA, and plasma aldosterone were similar in both groups, and none of the participants had edema. However, during the late luteal phase, ankle edema was present only in women with PMS, and their maximal plasma volume shift was lower compared with controls (11.7+/-1.3 versus 15.6+/-0.6; P=0.004). The area under the curve (estimates the amount of the total plasma shift during 30 minutes standing) was 300+/-28 and 406+/-16 in PMS and controls, respectively (P=0.01). PRA and aldosterone levels were higher during the late luteal phase in women with PMS compared with controls (supine PRA: 1.4+/-0.3 [PMS] versus 1.1+/-0.4 [control; P value not significant], upright PRA: 3.9+/-0.08 versus 1.6+/-0.3 ng/mL per hour [P=0.015], supine plasma aldosterone: 131+/-30 versus 68+/-17 pg/mL [P=0.09], and upright plasma aldosterone: 208+/-40 versus 102+/-16 pg/mL [P=0.03]). We, therefore, conclude that women with PMS have increased plasma fluid-regulatory hormones and disturbed fluid distribution only during their late luteal menstrual phase.
Premenstrual syndrome (PMS) presents with emotional and physical symptoms. Although the emotional symptoms have been extensively studied, the pathophysiology of the fluid-retention symptoms is not currently known. We tested the hypothesis that the fluid regulatory mechanisms are disturbed in PMS. Nine regularly menstruating women with PMS were compared with 9 healthy age-matched women. Hemodynamic parameters and upright plasma volume shift (extrapolated from changes in hematocrit), plasma renin activity (PRA), and plasma aldosterone and sex hormones were measured at different times during the menstrual cycle. During the early follicular and the midluteal phases, the plasma volume shift, supine and upright PRA, and plasma aldosterone were similar in both groups, and none of the participants had edema. However, during the late luteal phase, ankle edema was present only in women with PMS, and their maximal plasma volume shift was lower compared with controls (11.7+/-1.3 versus 15.6+/-0.6; P=0.004). The area under the curve (estimates the amount of the total plasma shift during 30 minutes standing) was 300+/-28 and 406+/-16 in PMS and controls, respectively (P=0.01). PRA and aldosterone levels were higher during the late luteal phase in women with PMS compared with controls (supine PRA: 1.4+/-0.3 [PMS] versus 1.1+/-0.4 [control; P value not significant], upright PRA: 3.9+/-0.08 versus 1.6+/-0.3 ng/mL per hour [P=0.015], supine plasma aldosterone: 131+/-30 versus 68+/-17 pg/mL [P=0.09], and upright plasma aldosterone: 208+/-40 versus 102+/-16 pg/mL [P=0.03]). We, therefore, conclude that women with PMS have increased plasma fluid-regulatory hormones and disturbed fluid distribution only during their late luteal menstrual phase.
Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:24
Disorders of the Female Reproductive System
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:28
Menopause
 01:33
Hormonal Regulation
 01:40
Hormonal Regulation