
[Influence of minimum volumes on the structure of inpatient care]
W de Cruppé1, C Ohmann, K Blum
1Professur für Public Health, Klinikum der Heinrich-Heine-Universität Düsseldorf, Düsseldorf, Germany. werner.de-cruppe@uniduesseldorf.de

Objective:
In 2004 five minimum volumes were introduced for the first time into German hospitals. The structural effects of these minimum volumes are presented as the first part of a health service research to evaluate the minimum volume regulation. DESIGN/METHODOLOGY/METHODS: The investigation is based on the mandatory hospital quality reports for 2004. Data were extracted from 1710 quality reports, descriptively analysed and applied to the modified minimum volumes for 2006.
Results:
In 2004, 485 out of 1710 German hospitals providing acute care and approximately 23,128 cases, i.e., 0.14% of all hospital cases, were affected by at least one minimum volume regulation. The number of affected hospitals varies considerably between the German Federal Sates with 16% in Bavaria and 75% in Bremen. In 2004 (and presumably 2006) the following hospital numbers will comply with the minimum volume regulation: liver transplantation 100% (63%), kidney transplantation 91% (84%), stem cell transplantation 84% (65%), complex oesophageal interventions 71% (40%), complex pancreatic interventions 82% (51%). On a case level, 4% of kidney transplantation cases and up to 22% of complex oesophageal interventions were to be redistributed. Viewing the hospital size by number of beds, smaller (100-300 beds) and medium size hospitals (300-600 beds) are affected in complex oesophageal and pancreatic interventions, whereas in transplantations medium and large hospitals (>600 beds) are affected. Considering the regional distribution on a district level, the number of districts with at least one hospital providing the respective service will decrease from 2004 to 2006, with the strongest reduction in complex oesophageal interventions from 172 to 82 districts (-53%).
Conclusion:
In 2004 the minimum volume regulation has moderate structural effects on the care setting. In 2006 these effects will be stronger due to the doubled number of interventions required for most of the minimum volumes. The effects on transplantations have to be differentiated from those on oesophageal and pancreatic interventions since the former are already highly centralised whereas the latter are mainly provided on a medium hospital care level and will be shifted on to the maximum hospital care level. This process should stimulate a debate on geographically equal access to care within and among the Federal Sates.
Related Concept Videos
 00:59
Hospitals-II
Nurses that work in hospitals have...
 01:14
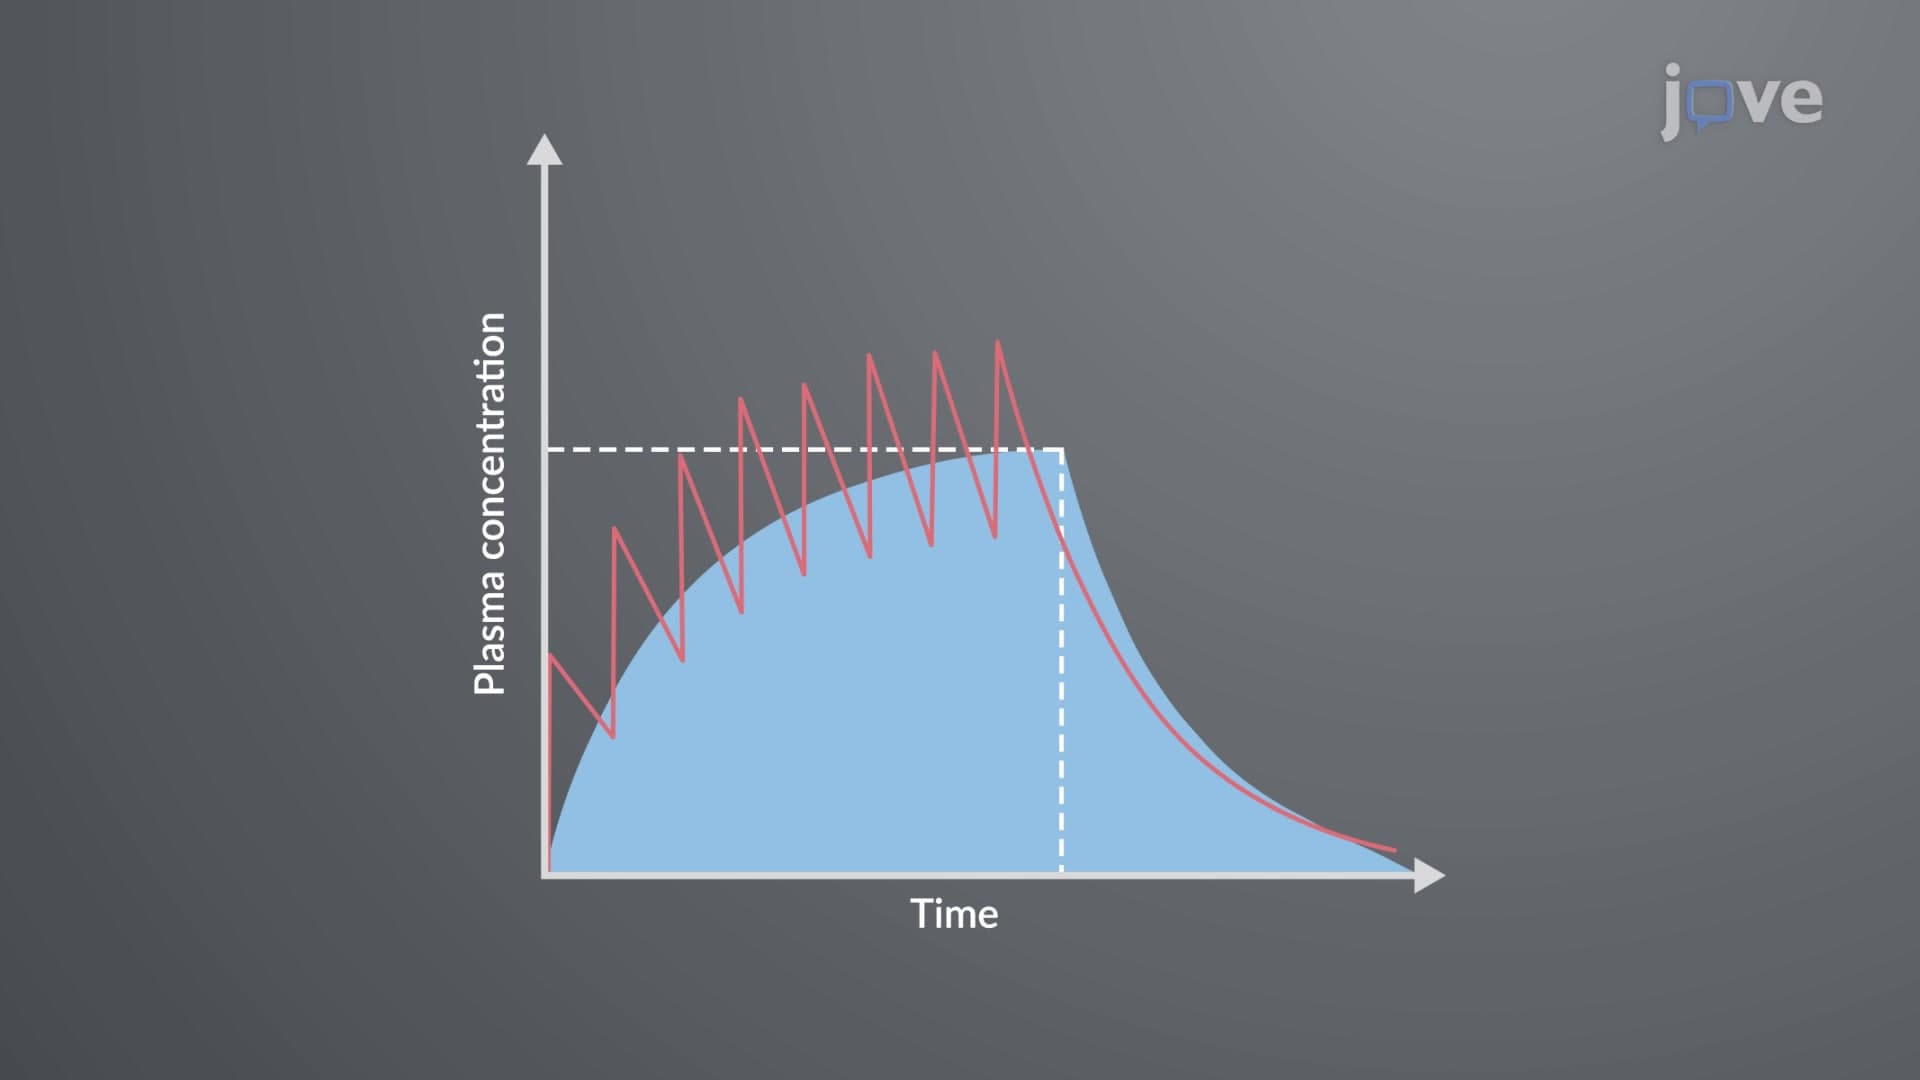
Compartment Models: Single-Compartment Model
 01:15
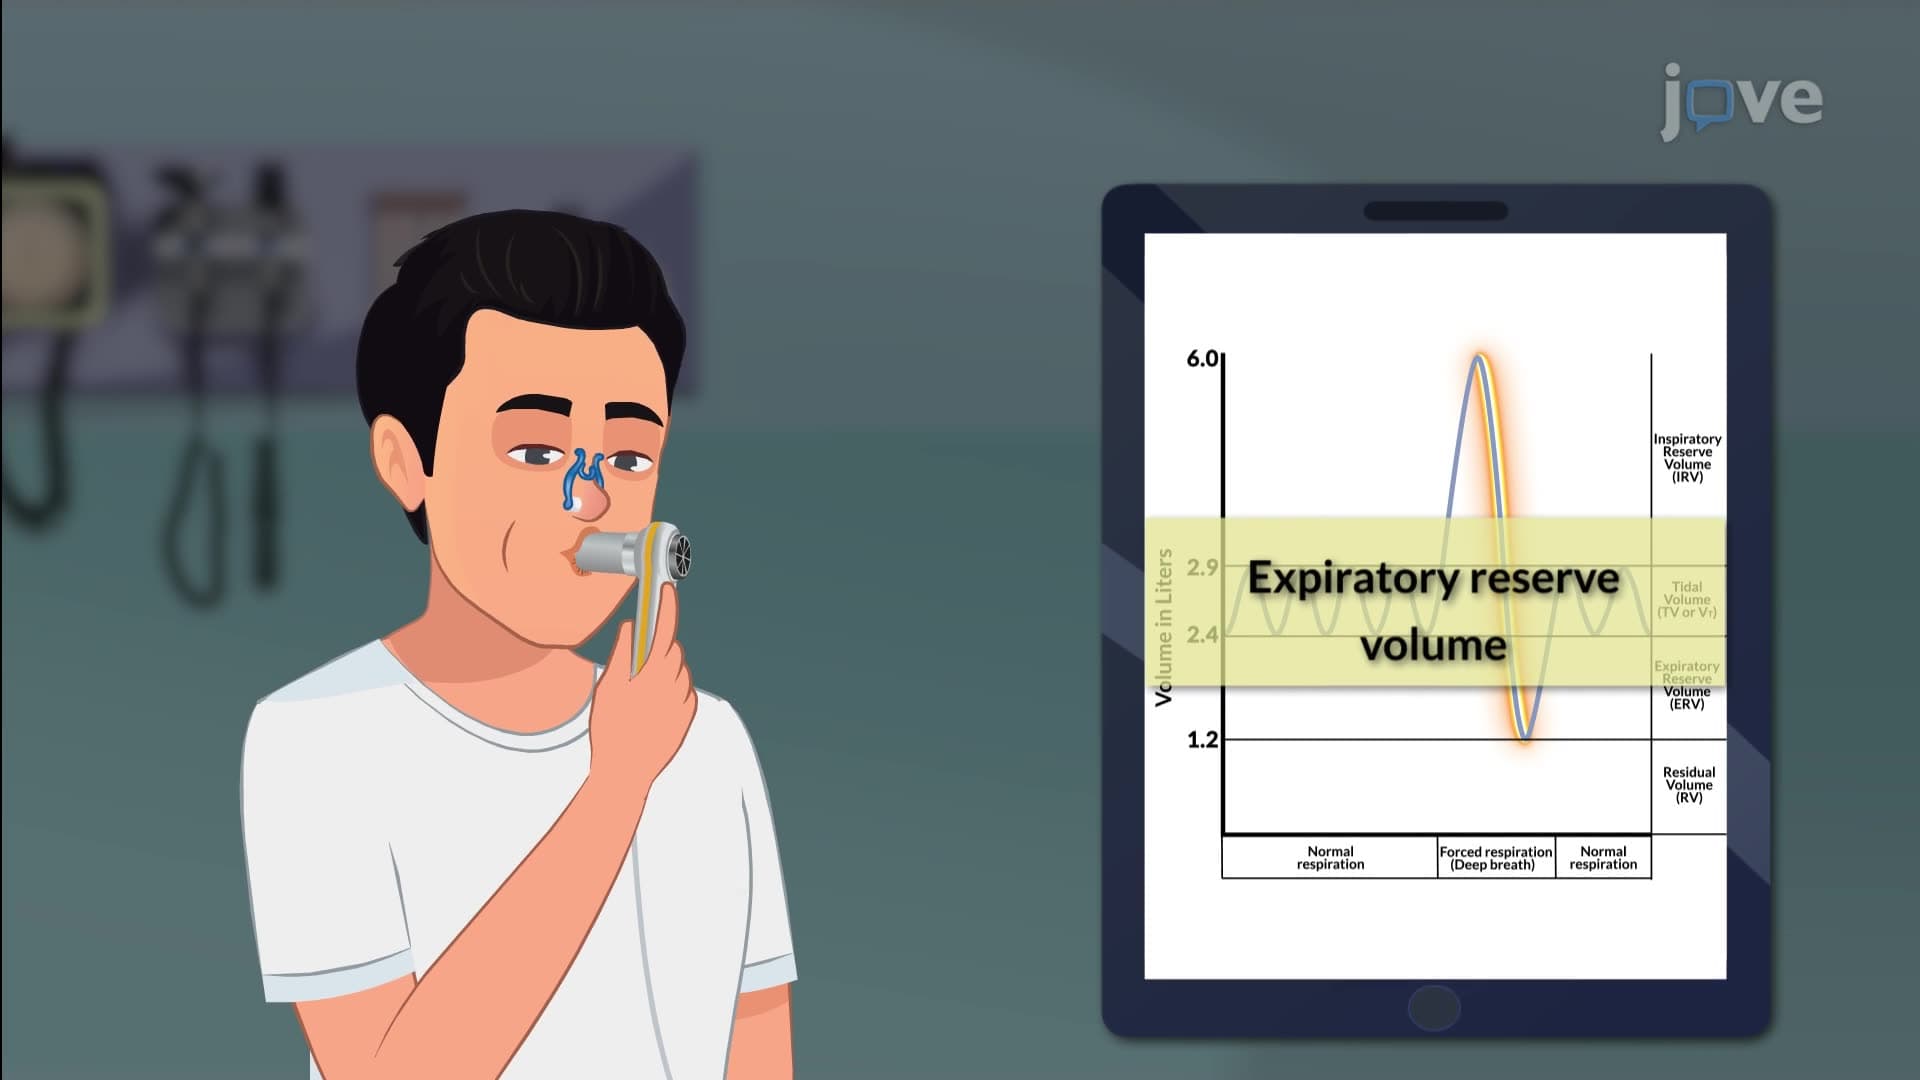
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:15
Methods of Documentation VI: Case Management Model
For example, a patient with a chronic illness...
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:15
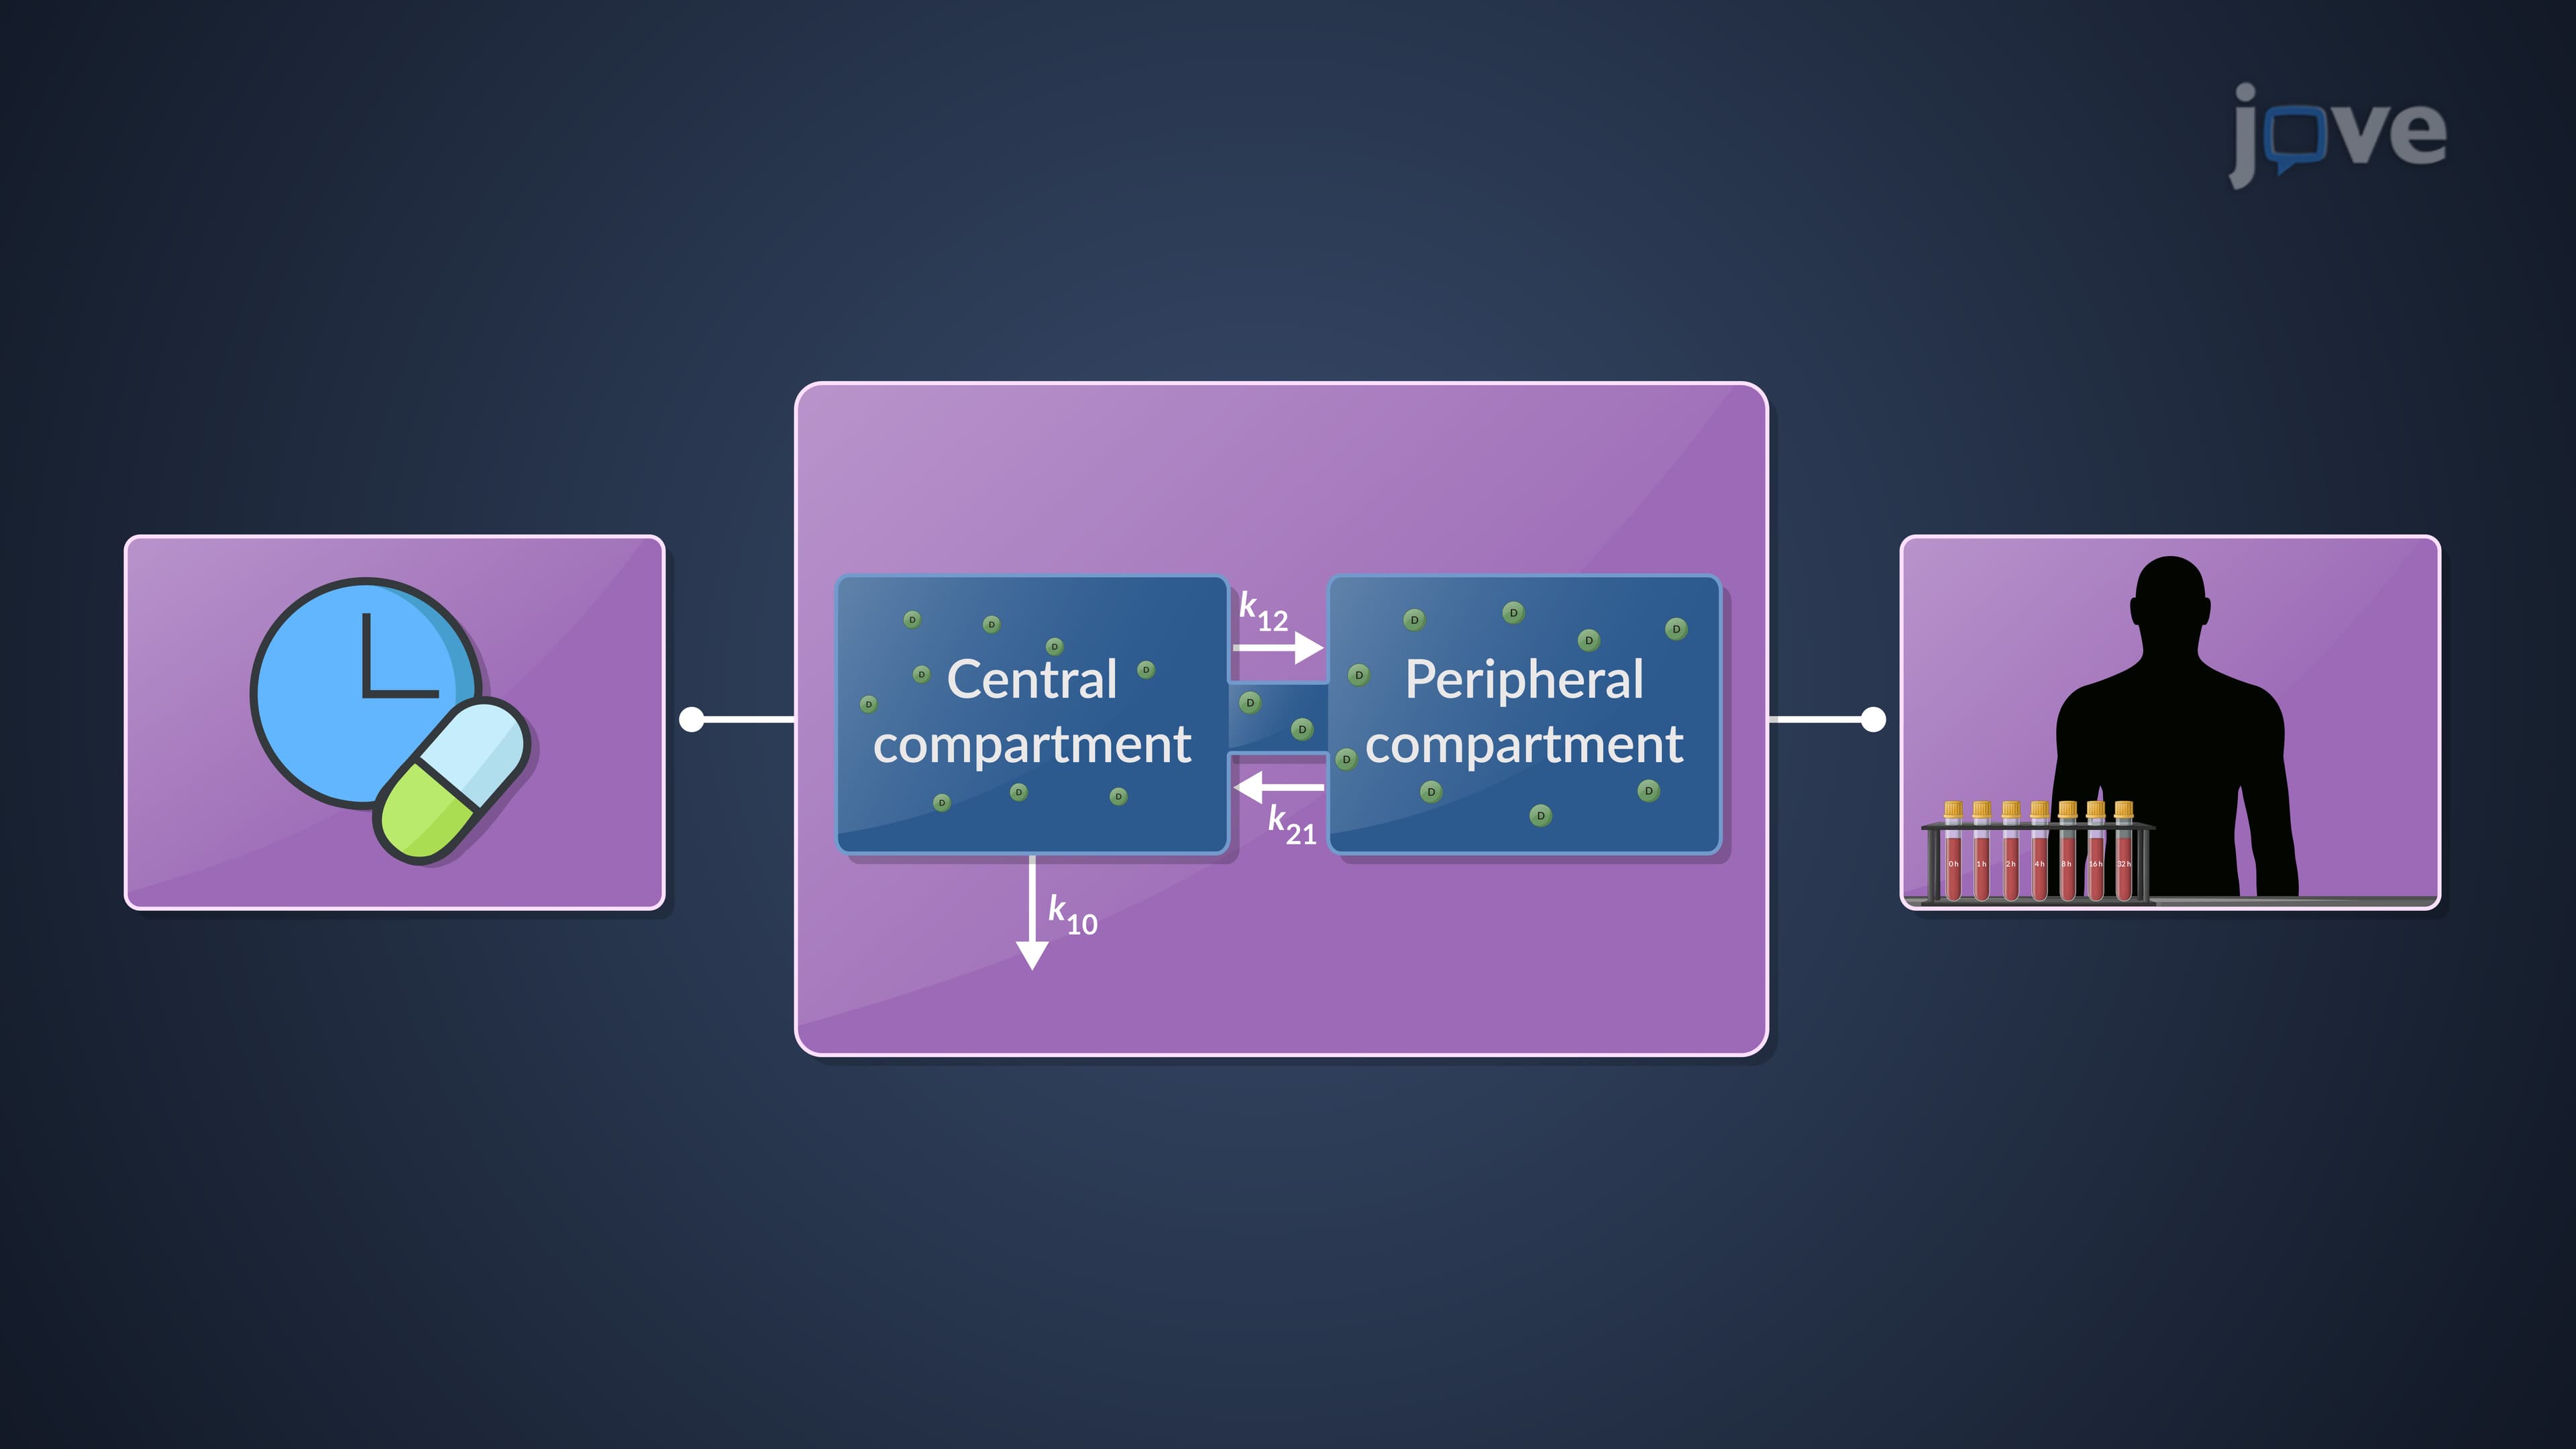
Two-Compartment Open Model: IV Infusion
The model illustrates the decrease in plasma drug concentration from the central compartment with a specific equation. It shows that under steady-state conditions, the drug's input rate...