Related Experiment Video
Updated: Jul 7, 2026

Detrusor Underactivity Model in Rats by Conus Medullaris Transection
Published on: August 28, 2020
The neurogenic bladder: introducing four contributions
1Department of Pediatrics Renal Unit, University of Leuven, Leuven, Belgium. willem.proesmans@med.kuleuven.be

Abstract:
Neurogenic bladder dysfunction in children is frequently seen in patients with meningomyelocele (MMC). The disorder carries a high risk for all kinds of complications, with renal damage being the most important. More than 95% of MMC patients have a neurogenic bladder, the paramount manifestation of which is a disturbed coordination between detrusor and sphincter muscles. This vesicourethral dysfunction leads to defective filling and emptying of the urinary bladder. Voiding at will is almost never possible. According to the location and extent of the neural tube lesion, patients have either an atonic or a hypertonic pelvic floor and either an atonic or a hypertonic detrusor, leading to four classic combinations. Hypertonic sphincter and detrusor hyperactivity lead to the most dangerous form of neurogenic bladder, referred to as the "unsafe" bladder. The presence of residual urine in a high-pressure container causes either decompensation of the detrusor with vesicoureteral reflux or deterioration of the bladder wall with hypertrophy and stiffness resulting in uterovesical obstruction. The subsequent insufficient drainage of the upper urinary tract leads to decompensation of the ureters and finally to chronic renal disease, the process being accelerated by urinary tract infections. The aim of treatment is to restore as much as possible both essential functions: urine storage and timely emptying of the reservoir. What should and can be achieved is a more or less adequate, low-pressure, functional capacity of the bladder that is emptied as completely as possible by clean intermittent catheterization (CIC). MMC leads to the prototype of neurogenic bladder in childhood. What we know and what we do for MMC patients can roughly be applied to all other forms of neurogenic bladder, either congenital or acquired.
Related Concept Videos
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating urine...
 01:23
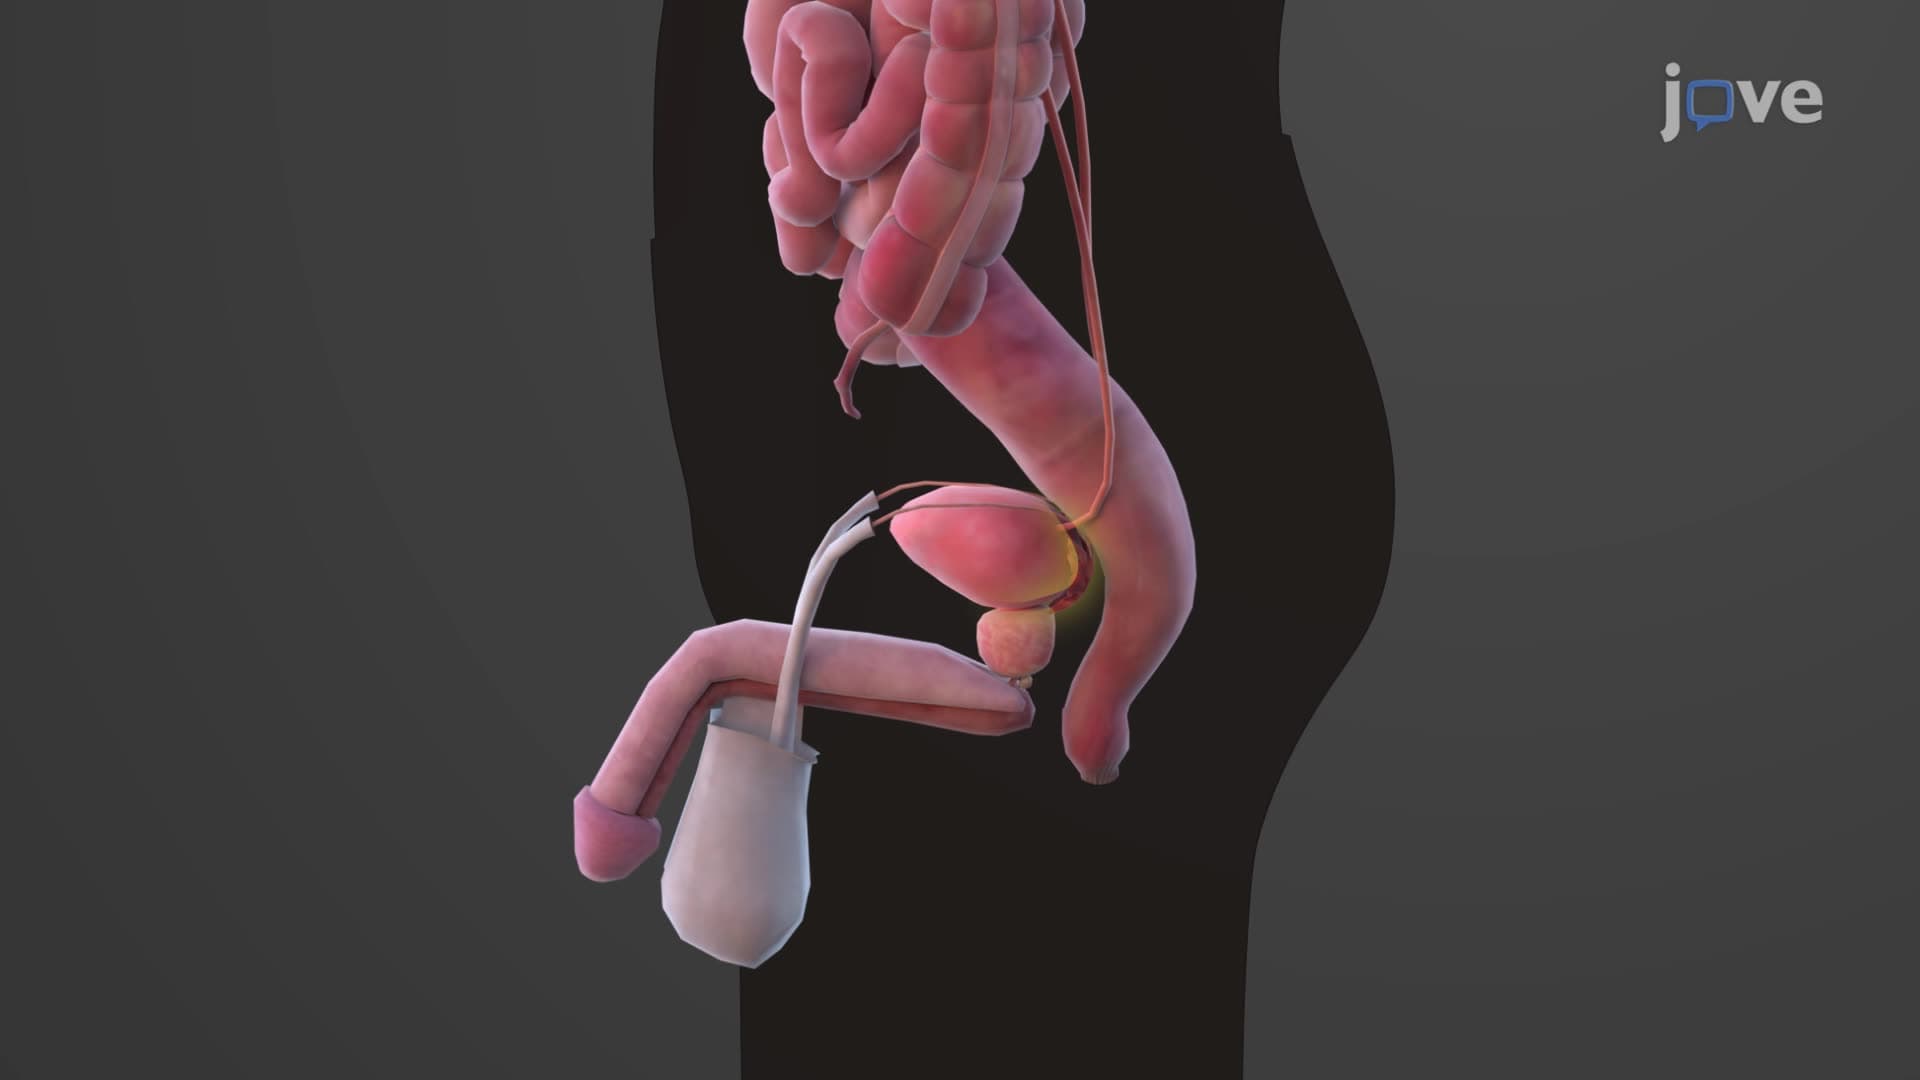
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:24
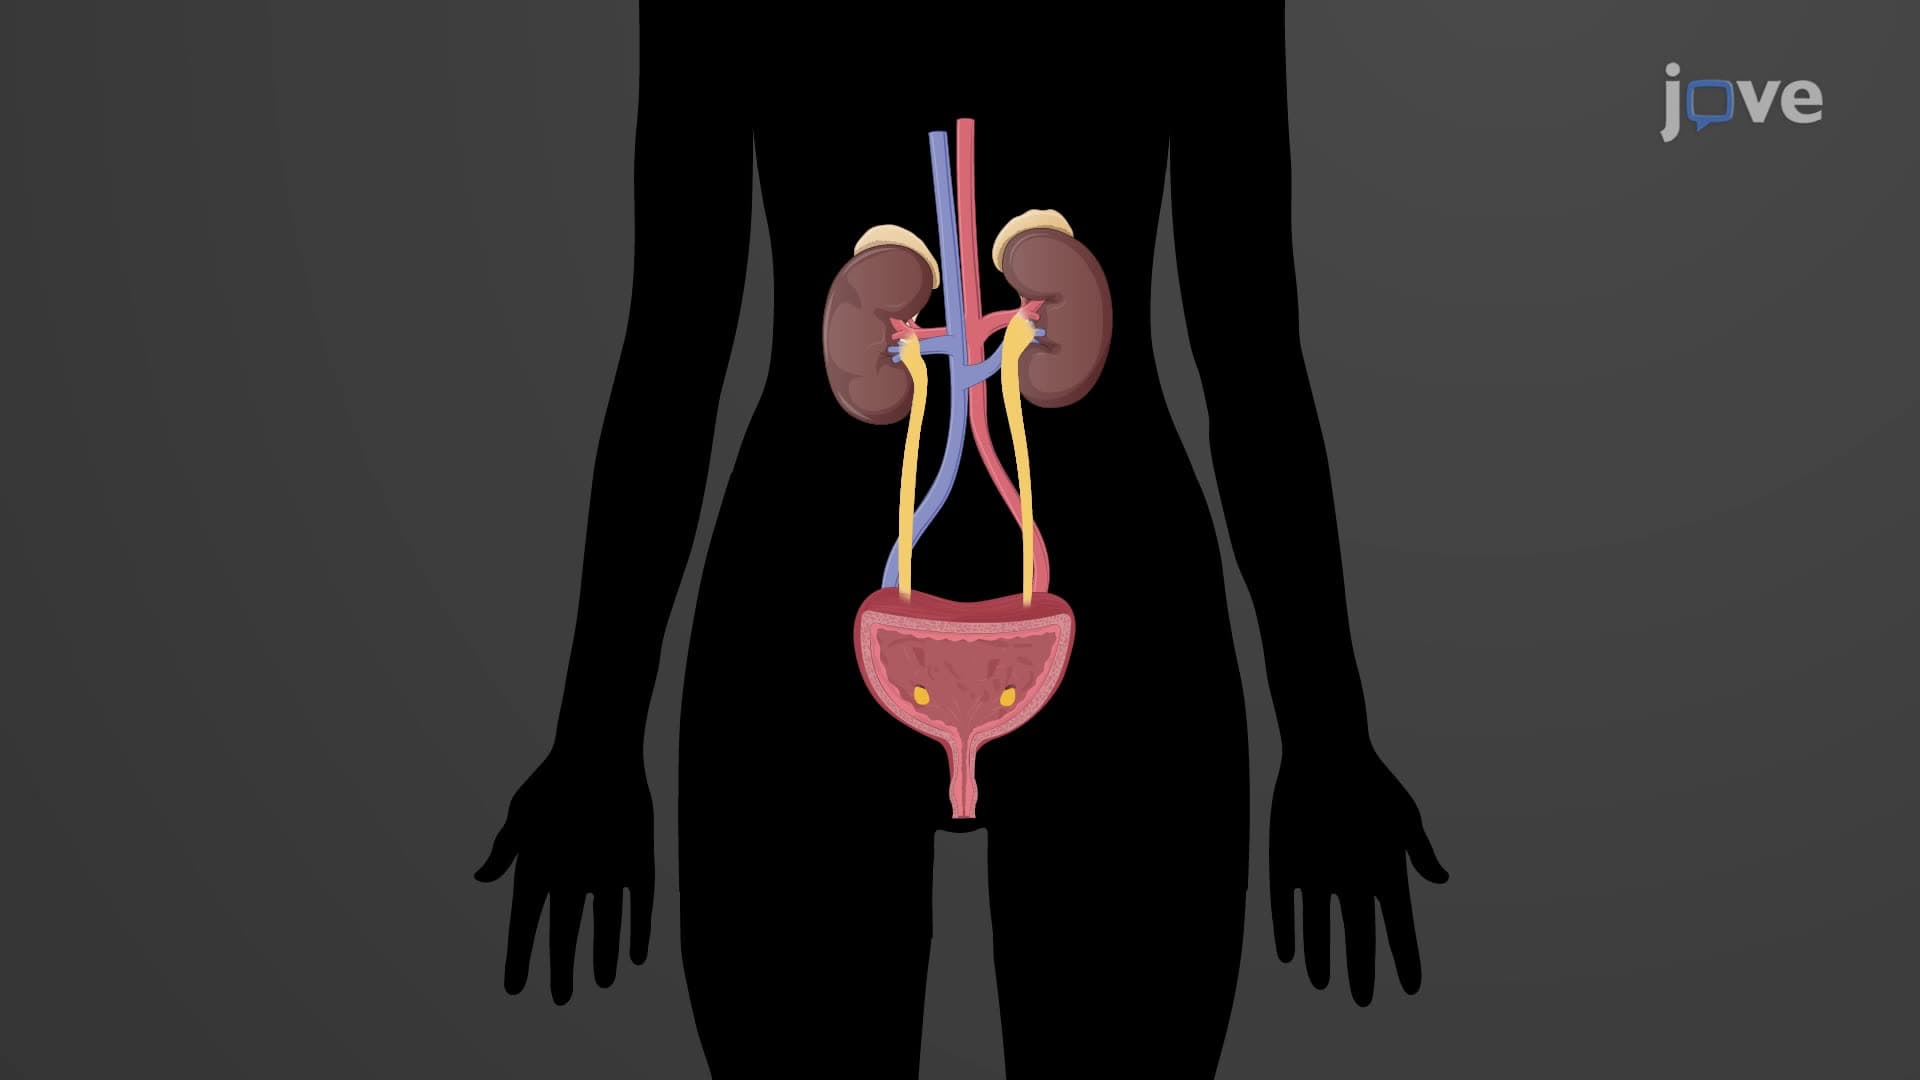
Physiology of Urine Formation
Glomerular Filtration
The first stage in urine formation is glomerular filtration. Each kidney contains approximately 1 million nephrons, the functional units of filtration, with a...
 01:13
Introduction to Urinary System
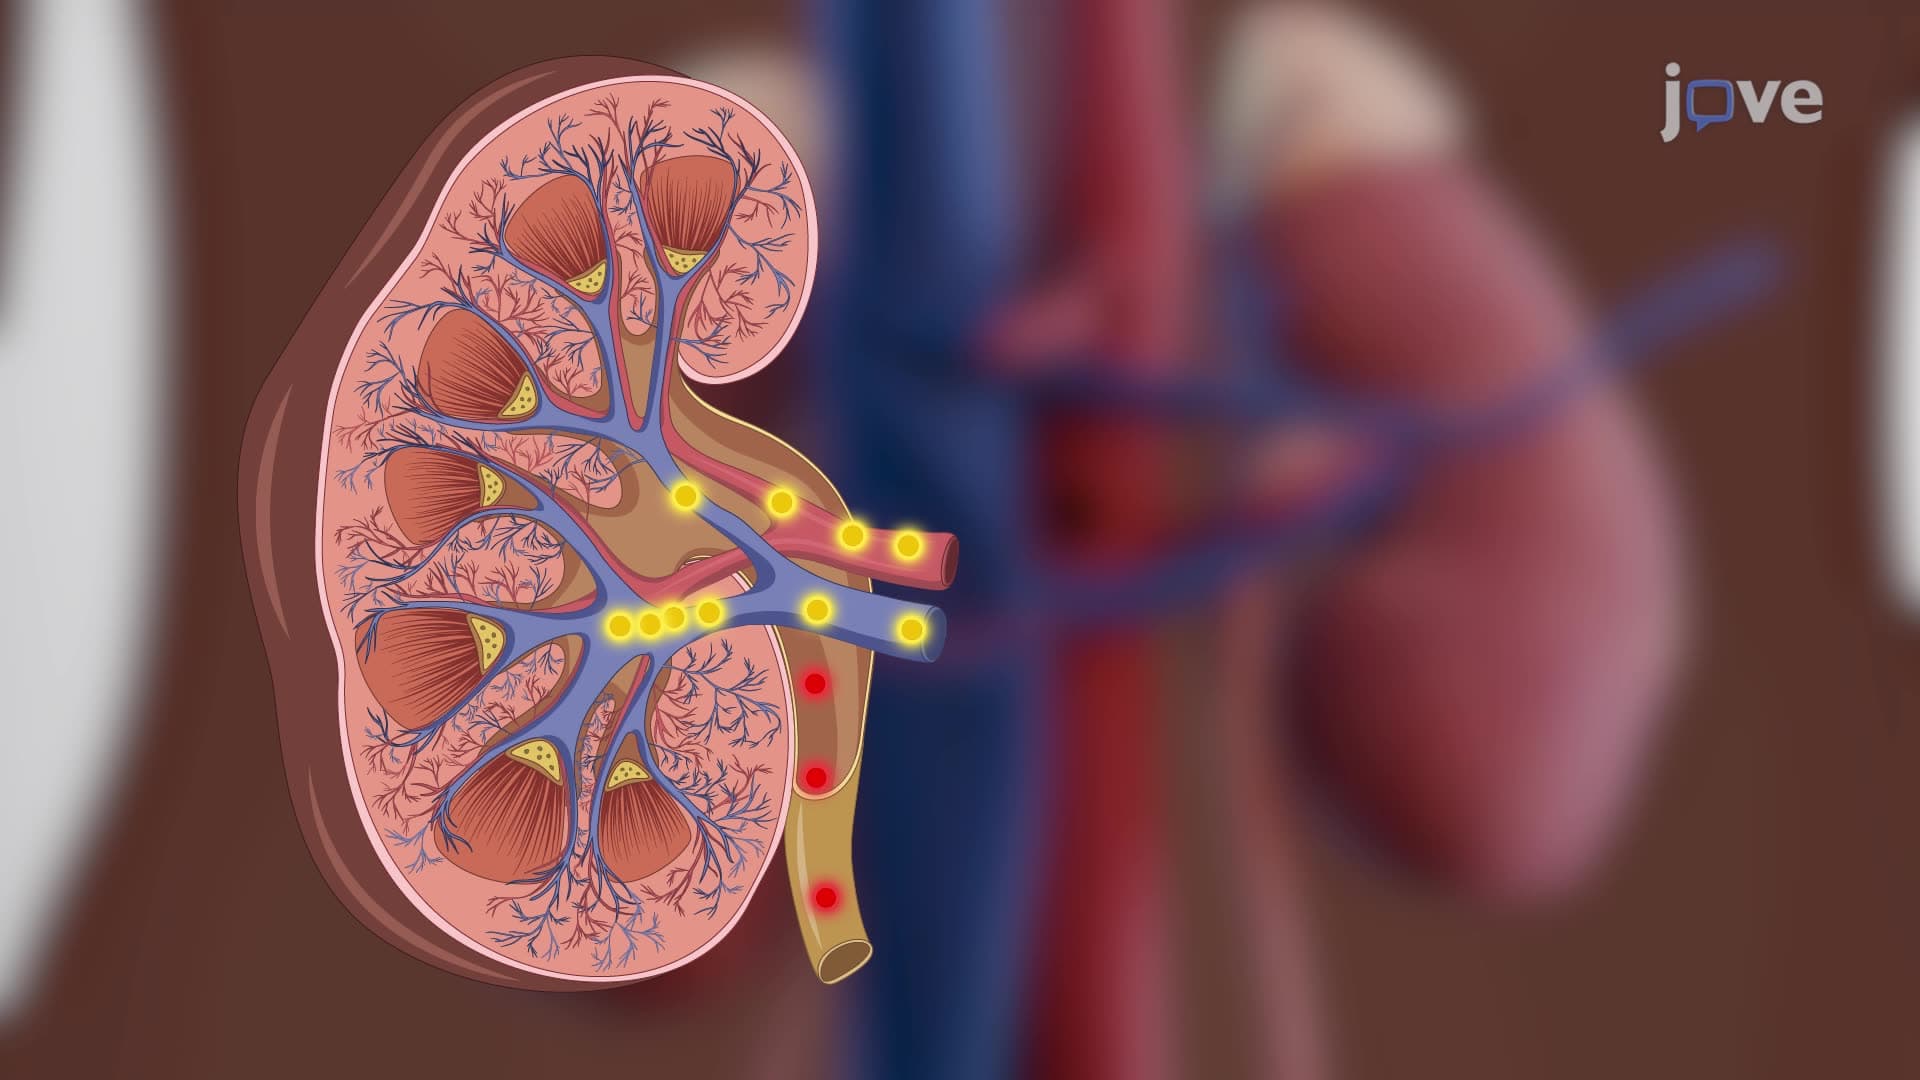
The kidneys are bean-shaped organs located in the retroperitoneal space, on either side of the vertebral column, between the T12 and L3 vertebrae. They are partially protected by the rib cage and surrounded by perirenal fat, which provides cushioning. They are responsible for urine formation and play critical roles in regulating blood pressure, electrolyte levels, and hormone production. The ureters...
 01:20
Physiology of the Genitourinary System III: Urine Concentration and Dilution