Laparoscopic anatrophic nephrolithotomy for managing large staghorn calculi
Related Experiment Video
Updated: Jul 7, 2026
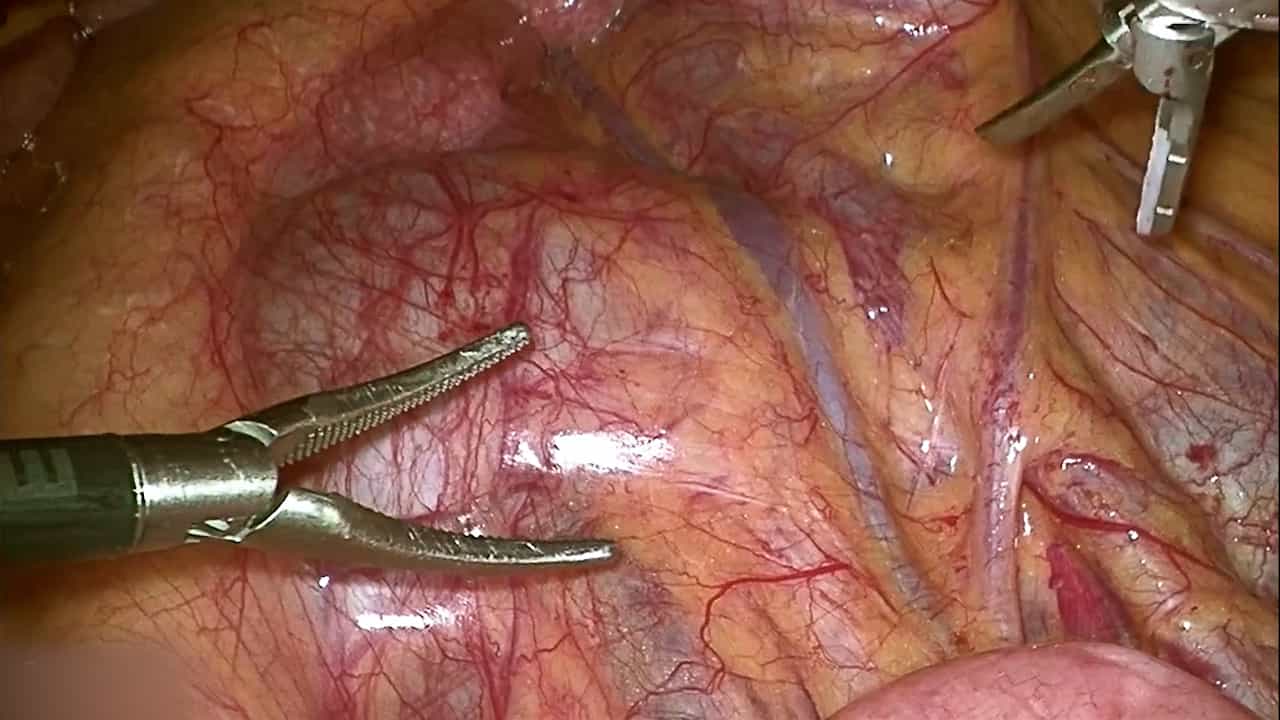
Transmesenteric Laparoscopic Pyeloplasty in Trendelenburg Position for Horseshoe Kidney with Hydronephrosis
Published on: July 8, 2025
Nasser Simforoosh1, Alireza Aminsharifi, Ali Tabibi
1Shaheed Labbafinejad Hospital, Urology Nephrology Research Center, Shaheed Beheshti University of Medical Sciences, Tehran, Iran. simforoosh@iurtc.org.ir

Objectives:
To evaluate the efficacy of a laparoscopic approach for managing large staghorn renal calculi.
Patients And Methods:
Laparoscopic transperitoneal anatrophic nephrolithotomy was used to duplicate open anatrophic nephrolithotomy in five patients (three men) with large staghorn renal stones unsuitable for percutaneous nephrolithotomy. Only the renal artery was clamped, using a bulldog clamp. The stone was removed through a nephrotomy incision on the Brodel line, which was closed using 3/0 polyglactin continuous sutures, and sutures were buttressed by haemostatic clips instead of knots. Intraoperative ultrasonography was used in the last two patients to evaluate residual stones.
Results:
The mean (range) stone size was 53 (45-65) mm, the patient age was 53 (45-58) years, and the warm ischaemia and operative duration were 32 (29-35) and 170 (120-225) min, respectively. No blood transfusion was needed during or after surgery. All of the procedures were uneventful and there was no urine leakage after surgery. Only an 8-mm and a 6-mm residual stone remained in the first and third patients, in the lower and middle calyces, respectively. Both of them were subsequently treated with shock wave lithotripsy. An intravenous pyelogram after surgery showed a functional corresponding renal unit, with a significant improvement in obstruction in all patients.
Conclusion:
Laparoscopic anatrophic nephrolithotomy is a promising alternative for patients who are candidates for open surgery, with an acceptable stone-free rate. While offering a minimally invasive approach, it can minimize the need for secondary invasive interventions. Further patients and a longer follow-up are needed before this is suggested as the preferred method in selected patients in the future.
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:30
Urinary Tract Calculi III: Medical Management
 01:28
Urinary Tract Calculi V: Nursing Management
 01:27
Urinary Tract Calculi IV: Nutrition Therapy and Prevention