Related Experiment Video
Updated: Jul 7, 2026
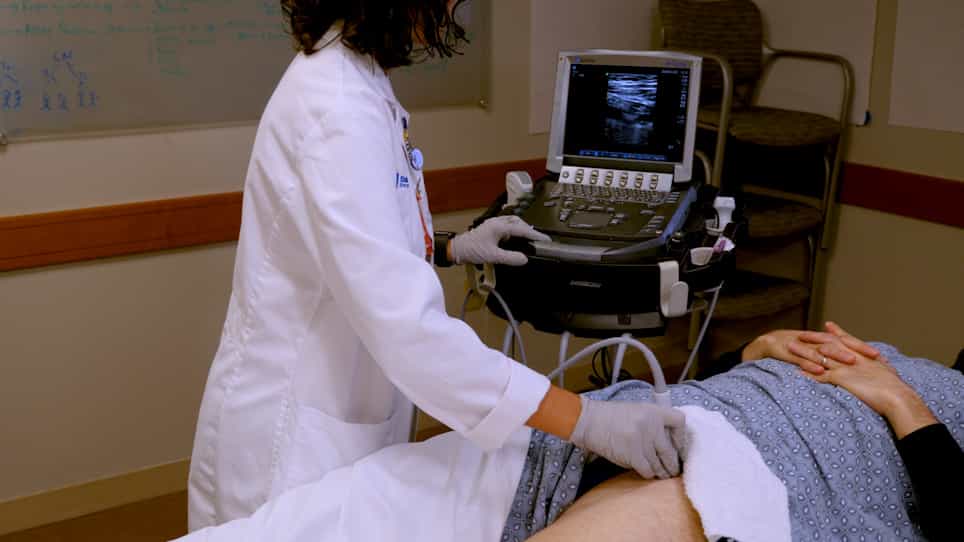
Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Incidence, risk factors, and treatment patterns for deep venous thrombosis in hospitalized children: an increasing
John A Sandoval1, Michael P Sheehan, Charles E Stonerock
1Department of Surgery, Indiana University School of Medicine and Riley Hospital for Children, Indianapolis, IN 46202, USA.

Insights
The incidence of deep venous thrombosis (DVT) in hospitalized children is rising. Children with severe conditions, central venous catheters, or prior DVT may benefit from prophylaxis.
Area of Science:
- Pediatric Medicine
- Hematology
- Thrombosis Research
Background:
- Deep venous thrombosis (DVT) management in hospitalized children lacks established guidelines.
- Pediatric DVT incidence, risk factors, and treatment patterns require further investigation.
Purpose of the Study:
- To assess the incidence, risk factors, and treatment strategies for DVT in hospitalized pediatric patients.
- To identify patient subgroups that may benefit from DVT prophylaxis.
Main Methods:
- Retrospective analysis of pediatric patients (<17 years) with DVT over 14 years.
- Evaluation of demographic data, clinical factors, Wells clinical probability scores, and treatment patterns.
- Comparison of treatment trends between 1992-2001 and 2002-2005.
Main Results:
- DVT incidence increased significantly from 0.3 to 28.8 per 10,000 admissions (1992-2005).
- Inpatient DVT risk factors included central venous catheters (45%), especially femoral (50%), severe respiratory/oncologic/infectious diseases, and prolonged ICU stays.
- Prehospital DVT was associated with prior DVT (38%) or thrombophilia (33%).
- Treatment shifted towards low-molecular-weight heparin.
Conclusions:
- Hospitalized children, particularly those with severe illnesses, central venous access (femoral), or prior DVT, are candidates for prophylaxis.
- Clinical probability scores alone are insufficient for risk stratification.
- Urgent need for childhood-specific trials to establish DVT prophylaxis guidelines.
Objective:
The optimal prophylactic strategy and treatment regimen for deep venous thrombosis (DVT) in hospitalized pediatric patients is not clearly established. This study assessed the incidence, risk factors, and treatment patterns for DVT among pediatric patients admitted to a hospital ward.
Methods:
Children (aged <17 years) admitted to a single tertiary-care hospital during a 14-year period who developed or presented with DVT were retrospectively identified. Patient demographic and clinical data were analyzed retrospectively. Patients who developed DVT in the hospital were stratified according to the Wells clinical probability scoring system from criteria noted before the diagnosis. Treatment patterns and outcomes were evaluated between the two time intervals of 1992 to 2001 (group I) and 2002 to 2005 (group II).
Results:
Between 1992 and 2005, 358 children were evaluated for DVT, and 99 (52 boys, 47 girls) were admitted to the hospital and were determined to have DVT by confirmatory imaging. A prior DVT (12 total) was present in eight of the 21 patients admitted for DVT treatment; of the remaining, only seven received DVT prophylaxis on admission. In those developing a DVT, the inpatient clinical probability score was 21% (low), 40% (moderate), and 39% (high). The most common risk factor in those with prehospital DVT was a prior DVT (38%) or thrombophilic condition (33%), whereas inpatients had a central catheter (45%), with nearly 50% in the femoral vein. Children acquiring an inpatient DVT had concomitant severe respiratory (17%), oncologic (14%), and/or infectious (15%) diseases and required a prolonged intensive care unit (12.7 days) stay. Prehospital DVT was lower extremity predominant (90%) and statistically different from inpatient-acquired DVT (62%, P = .01). Treatment patterns between periods I and II revealed a trend to more low-molecular-weight heparin and less unfractionated heparin use (P = .09). Three patients died (one fatal pulmonary embolism). The number of recognized cases per 10,000 admissions increased from 0.3 to 28.8 from 1992 to 2005.
Conclusion:
The incidence of DVT in hospitalized children is increasing. Those presenting with DVT typically have prior DVT, thrombophilia, or lower extremity disease. Our study suggests that children admitted with severe medical conditions who require a prolonged intensive care unit stay in addition to central venous access (especially via the femoral vein) should be considered candidates for DVT prophylaxis. A clinical probability scoring system alone cannot stratify patients sufficiently to forgo prophylaxis in hopes of a rapid clinical diagnosis. Childhood-specific level 1 trials aimed at determining guidelines for DVT prophylaxis are urgently required.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:30
Venous Thrombosis IV: Nursing Management
 01:19
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism I: Introduction