Related Experiment Video
Updated: Jul 7, 2026


Tissue Engineering of the Intestine in a Murine Model
Published on: December 1, 2012
Multiple atresia of the small intestine: a 20-year review

Background:
Multiple intestinal atresia (MIA) presents with a wide spectrum of bowel pathologies. Its treatment is a challenging task since restoration of anatomical continuity of the affected intestine must be balanced against preservation of the intestine's maximal length.
Material And Methods:
A retrospective analysis of the medical notes of 26 patients with MIA treated over a 20-year period between 1986 - 2006 was undertaken with a special emphasis on the clinical and surgical perspectives.
Results:
All 26 cases of MIA were sporadic with no familial history. The mean gestational age and birth weight were 36.1 weeks and 2781 g, respectively. Twenty-three of the infants underwent operative repair within the first days of life. Three patients with gastroschisis had a delayed diagnosis of bowel atresia. The number of atresias per patient ranged from 2 to 10. In 24 newborns atresias were confined to the small bowel, with 2 other patients having additional obstruction of the ascending colon. Various combinations of anatomical types of atresias were found, with type I and type III occurring in 19 patients each. Type II was diagnosed in 7 newborns. Surgical management of MIA consisted of one-stage restoration of bowel continuity with multiple anastomoses and/or enteroplasties in 22 patients. Four patients had an enterostomy performed at initial operation. Early and late postoperative complications requiring operative treatment occurred in 8 patients. The duration of parenteral nutrition ranged from 6 days to 20 months, exceeding 100 days in 6 children. The follow-up ranges from 3 months to 16 years. All the patients are alive and are on a full oral diet.
Conclusion:
Clinical observations of sporadic cases of MIA confined to the small bowel lend support to the hypothesis of a vascular incident etiology. One-stage restoration of intestinal continuity with preservation of maximal intestinal length should be the basic principle of any operative management of MIA. Despite a relatively high morbidity related to the primary damage of the fetal intestine, excellent results with 100 % survival rates can be obtained. After taking the differences in pathogenesis, anatomical and histological features, and the prognosis for sporadic and hereditary forms of MIA into account, these two entities should be classified separately in a modified classification of intestinal atresia.
Insights
Multiple intestinal atresia (MIA) is a rare condition. Surgical repair aims to restore bowel continuity while preserving length, achieving excellent survival rates in sporadic cases.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Neonatal Medicine
Background:
- Multiple intestinal atresia (MIA) presents a complex spectrum of bowel pathologies.
- Surgical treatment requires balancing anatomical restoration with maximal intestine length preservation.
Purpose of the Study:
- To analyze clinical and surgical perspectives of MIA treatment.
- To evaluate outcomes in a cohort of MIA patients.
Main Methods:
- Retrospective analysis of medical records from 26 MIA patients (1986-2006).
- Emphasis on clinical presentation, surgical management, and postoperative outcomes.
Main Results:
- All 26 MIA cases were sporadic; mean gestational age 36.1 weeks, birth weight 2781g.
- 22 patients underwent one-stage repair with anastomoses/enteroplasties; 4 had initial enterostomy.
- All patients survived, are on a full oral diet, with 8 experiencing early/late complications requiring surgery.
Conclusions:
- Sporadic MIA supports a vascular incident etiology.
- One-stage restoration prioritizing maximal intestinal length is the primary surgical principle.
- Separate classification for sporadic and hereditary MIA is recommended based on distinct features.


Related Concept Videos
 01:27
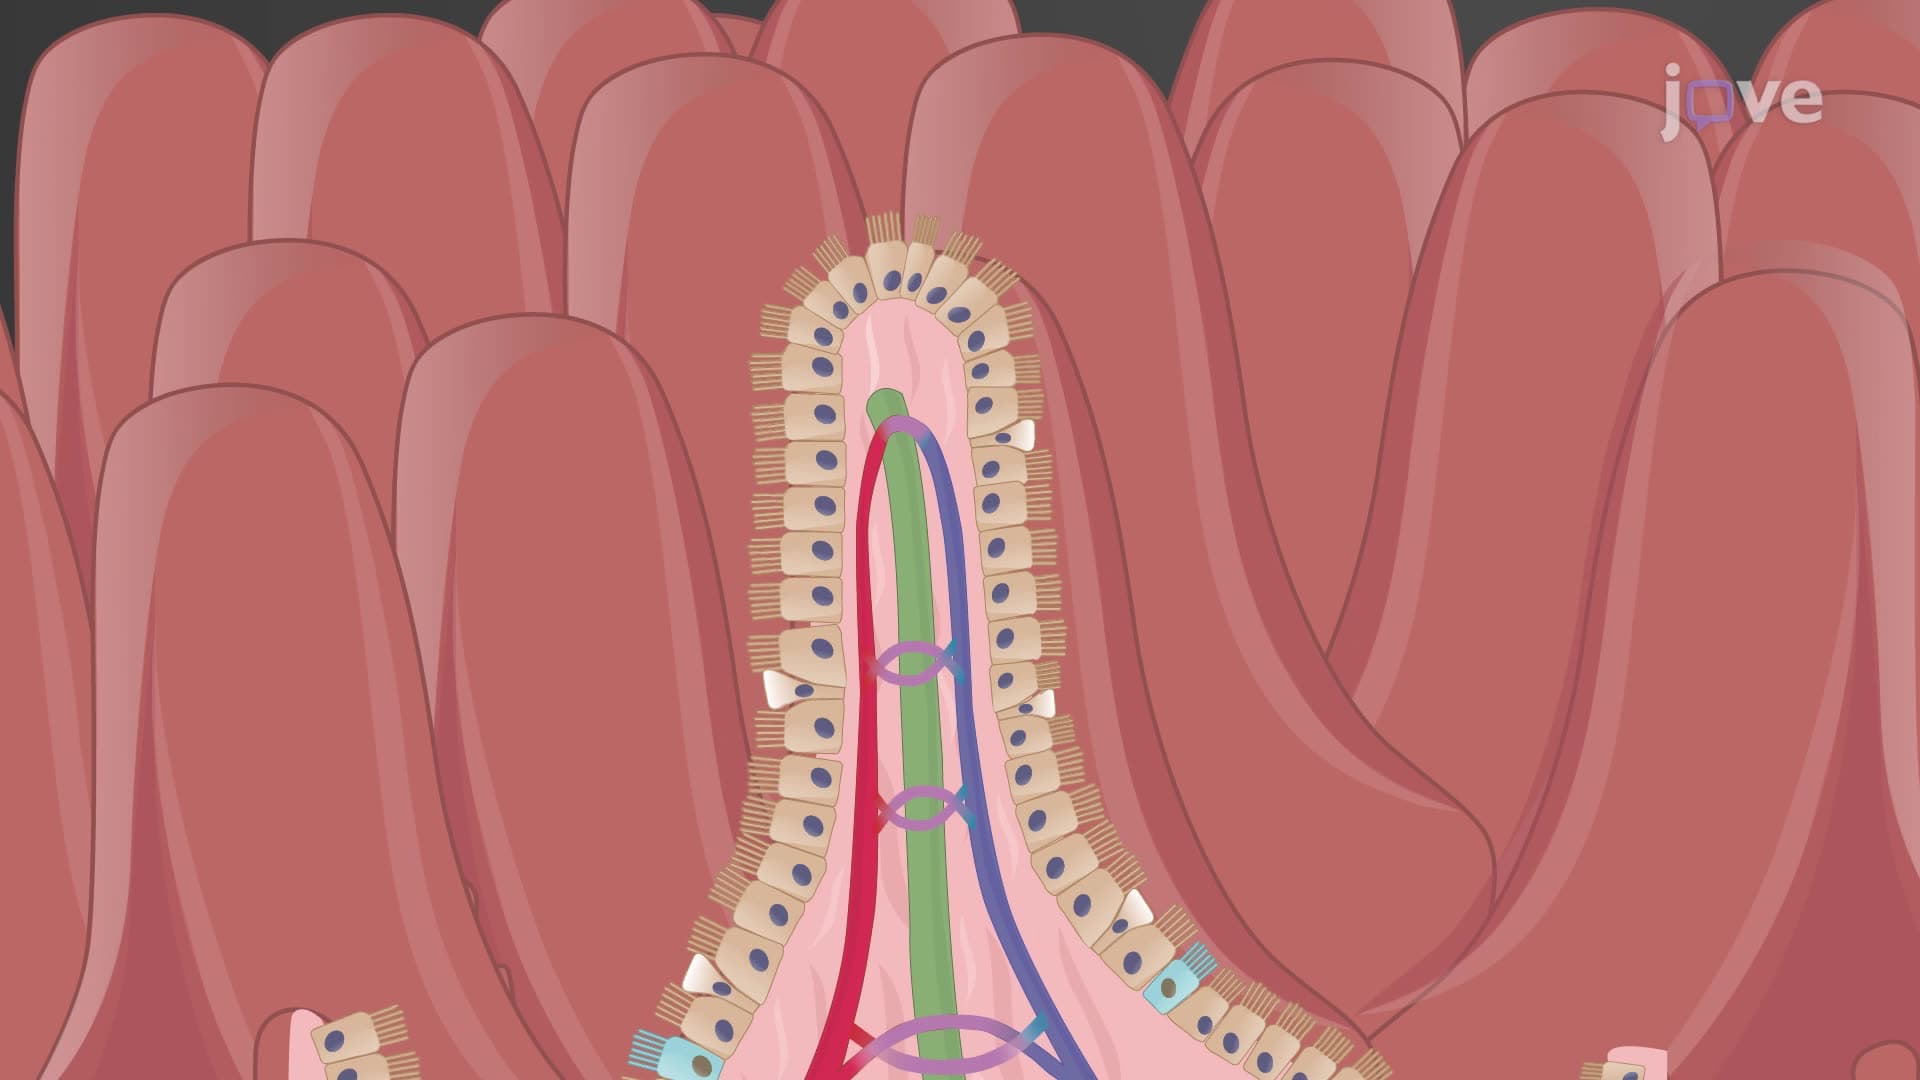
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:15
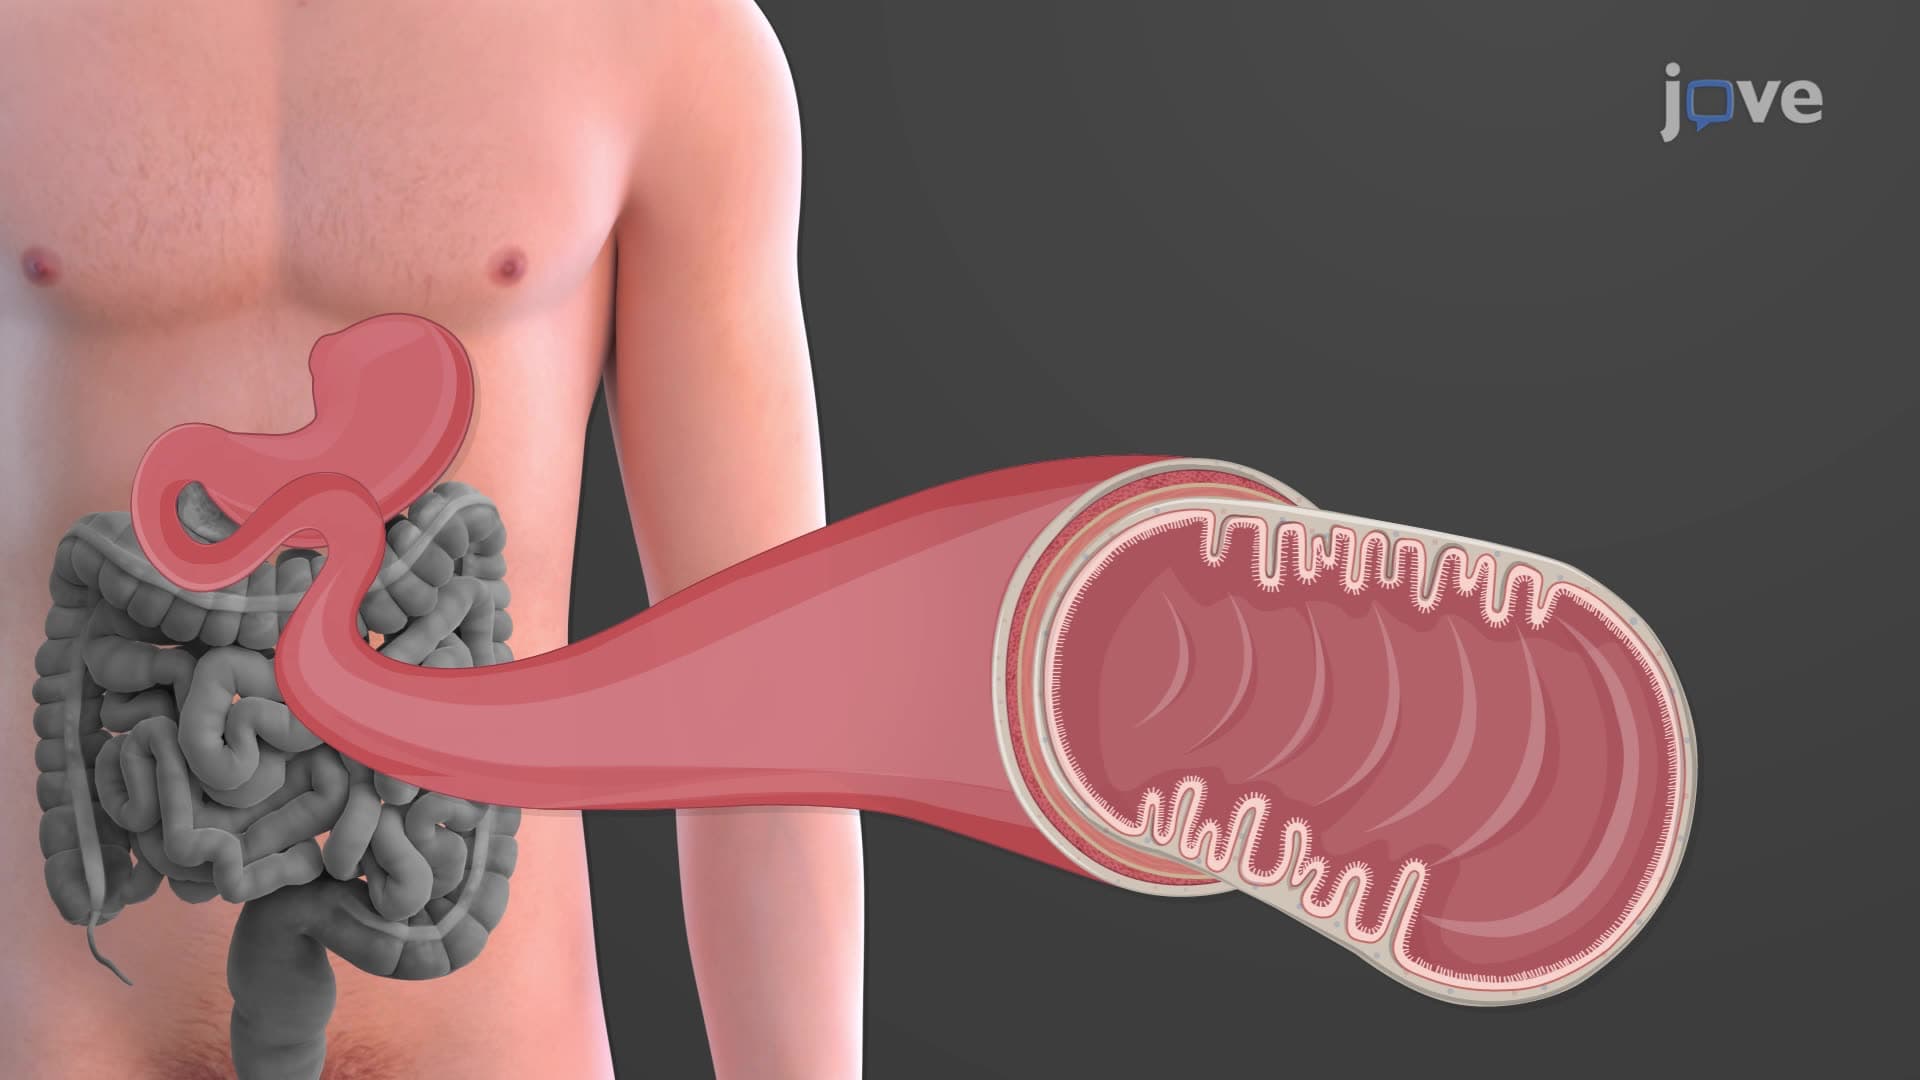
Small Intestine
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique C-shape wraps...
 01:23
Renewal of Intestinal Stem Cells
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
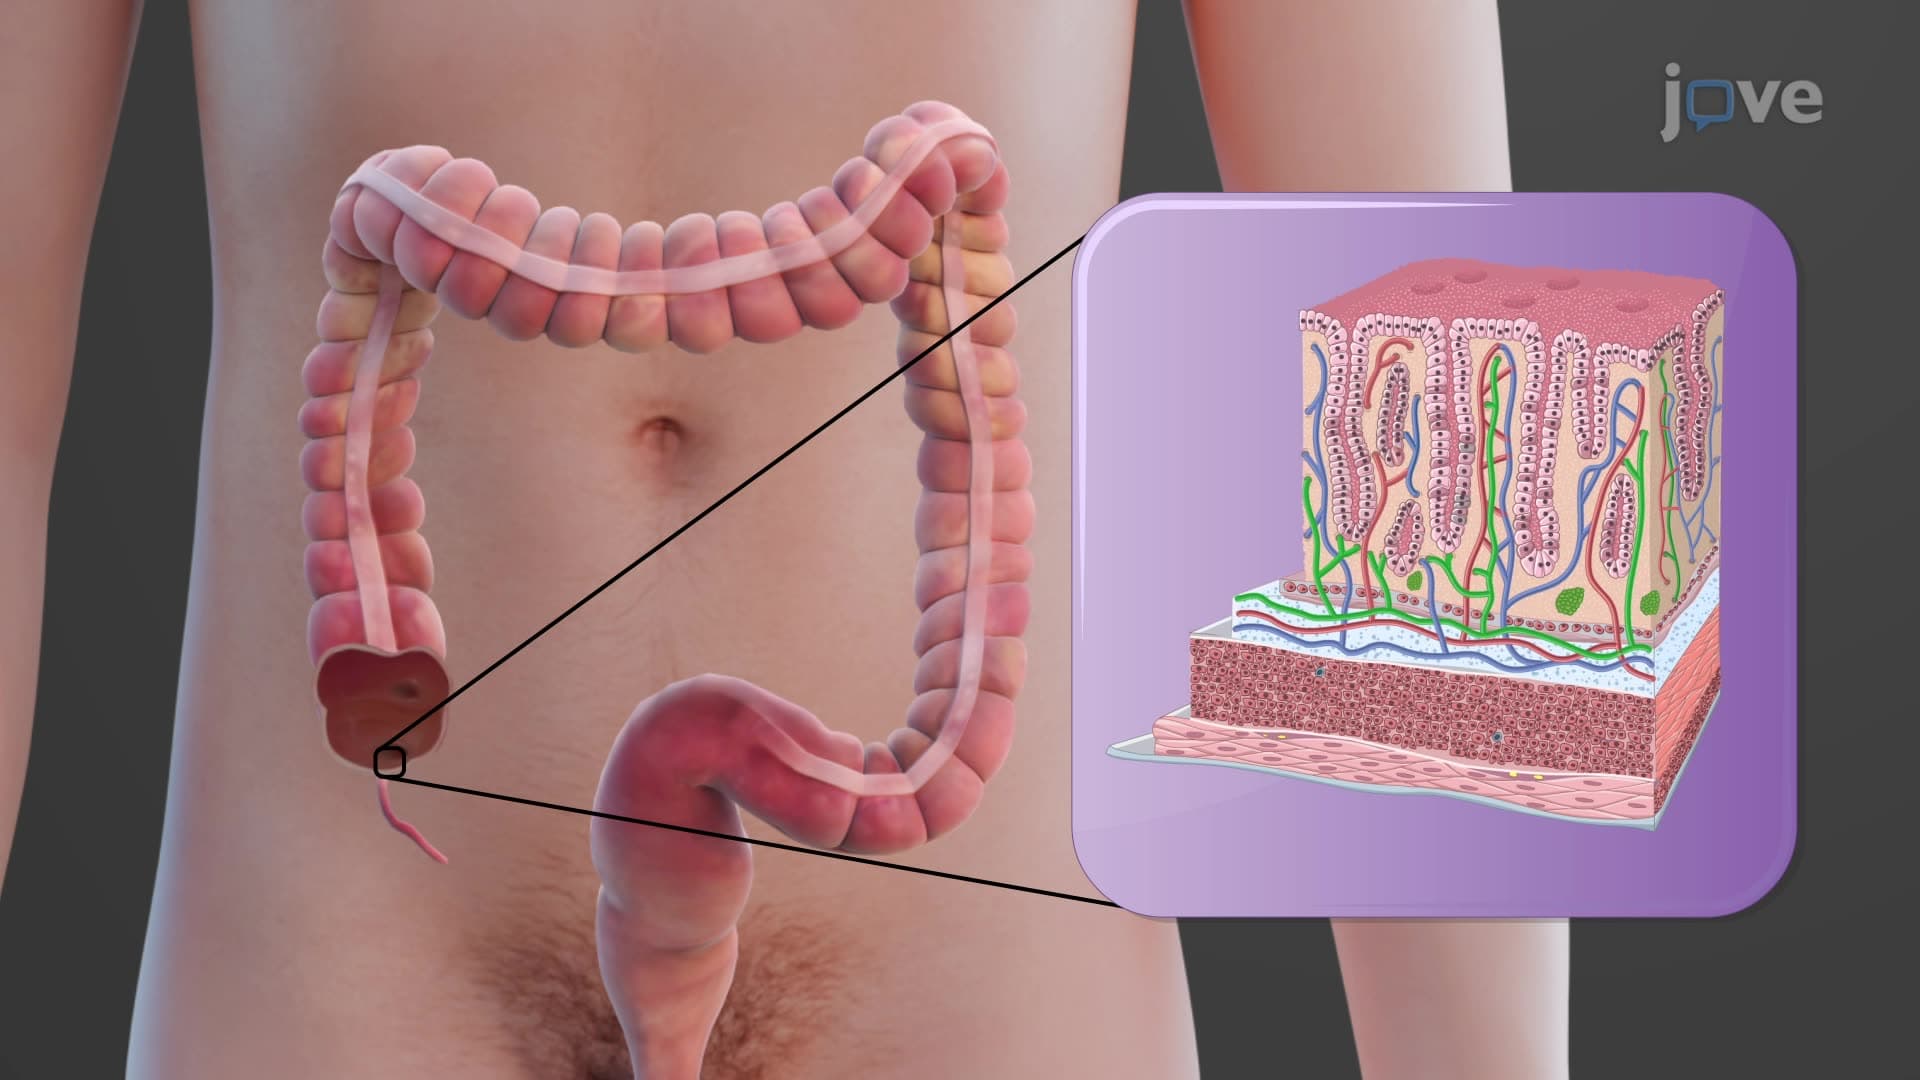
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:07
Intestinal Obstruction II: Pathophysiology