Related Experiment Video
Updated: Jul 7, 2026
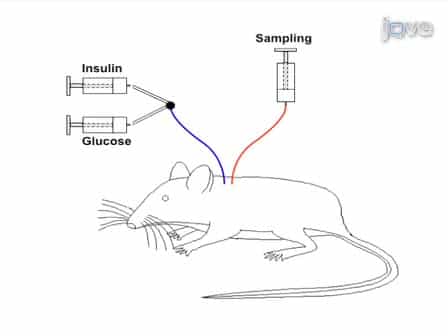

Hyperinsulinemic-Euglycemic Clamp in the Conscious Rat
Published on: February 7, 2011
Perioperative hyperinsulinaemic normoglycaemic clamp causes hypolipidaemia after coronary artery surgery
C J Zuurbier1, F J Hoek, J van Dijk
1Department of Anaesthesiology, Academic Medical Center, University of Amsterdam, Meibergdreef 9, 1105 AZ Amsterdam, The Netherlands. c.j.zuurbier@amc.uva.nl

Background:
Glucose-insulin-potassium (GIK) administration is advocated on the premise of preventing hyperglycaemia and hyperlipidaemia during reperfusion after cardiac interventions. Current research has focused on hyperglycaemia, largely ignoring lipids, or other substrates. The present study examines lipids and other substrates during and after on-pump coronary artery bypass grafting and how they are affected by a hyperinsulinaemic normoglycaemic clamp.
Methods:
Forty-four patients were randomized to a control group (n=21) or to a GIK group (n=23) receiving a hyperinsulinaemic normoglycaemic clamp during 26 h. Plasma levels of free fatty acid (FFA), total and lipoprotein (VLDL, HDL, and LDL)-triglycerides (TG), ketone bodies, and lactate were determined.
Results:
In the control group, mean FFA peaked at 0.76 (sem 0.05) mmol litre(-1) at early reperfusion and decreased to 0.3-0.5 mmol litre(-1) during the remaining part of the study. GIK decreased FFA levels to 0.38 (0.05) mmol litre(-1) at early reperfusion, and to low concentrations of 0.10 (0.01) mmol litre(-1) during the hyperinsulinaemic clamp. GIK reduced the area under the curve (AUC) for FFA by 75% and for TG by 53%. The reduction in total TG was reflected by a reduction in the VLDL (-54% AUC) and HDL (-42% AUC) fraction, but not in the LDL fraction. GIK prevented the increase in ketone bodies after reperfusion (-44 to -47% AUC), but was without effect on lactate levels.
Conclusions:
Mild hyperlipidaemia was only observed during early reperfusion (before heparin reversal) and the hyperinsulinaemic normoglycaemic clamp actually resulted in hypolipidaemia during the largest part of reperfusion after cardiac surgery.
Insights
Glucose-insulin-potassium (GIK) therapy during cardiac surgery reduces harmful fatty acids and triglycerides, leading to lower lipid levels. This intervention helps manage metabolic changes after reperfusion, improving patient outcomes.
Area of Science:
- Cardiovascular Surgery
- Metabolic Medicine
- Intensive Care Medicine
Background:
- Glucose-insulin-potassium (GIK) administration is proposed to prevent hyperglycemia and hyperlipidemia post-cardiac interventions.
- Existing research primarily addresses hyperglycemia, with limited focus on lipid profiles and other metabolic substrates.
- This study investigates lipid and substrate dynamics during and after on-pump coronary artery bypass grafting (CABG) under a hyperinsulinemic normoglycemic clamp.
Purpose of the Study:
- To evaluate the impact of a hyperinsulinemic normoglycemic clamp on lipid metabolism and other substrates during and after on-pump CABG.
- To determine if GIK administration mitigates adverse metabolic changes, particularly hyperlipidemia, in the perioperative period.
- To provide a comprehensive analysis of substrate alterations beyond glucose during cardiac surgery recovery.
Main Methods:
- A randomized controlled trial involving 44 patients undergoing on-pump CABG.
- Patients were assigned to either a control group (n=21) or a GIK group (n=23) receiving a 26-hour hyperinsulinemic normoglycemic clamp.
- Plasma levels of free fatty acids (FFA), total triglycerides (TG), VLDL, HDL, LDL, ketone bodies, and lactate were measured.
Main Results:
- GIK significantly reduced free fatty acid (FFA) levels during early reperfusion and throughout the clamp period (75% reduction in AUC).
- GIK decreased total triglycerides (TG) by 53% (AUC), primarily by reducing VLDL and HDL fractions, with no significant effect on LDL.
- GIK prevented post-reperfusion increases in ketone bodies (44-47% AUC reduction) but did not influence lactate levels.
Conclusions:
- Mild hyperlipidemia was transient, observed only during early reperfusion before heparin reversal.
- The hyperinsulinemic normoglycemic clamp effectively induced hypolipidemia during the majority of the reperfusion phase post-cardiac surgery.
- GIK administration demonstrates a significant role in modulating lipid and substrate metabolism, potentially improving outcomes in cardiac surgery patients.

Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:15
Hypoglycemia and Glucagon
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:26
Hypoglycemia
 01:06
Oral Hypoglycemic Agents: Glinides
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...